

Wegener’s granulomatosis is the former name for granulomatosis with polyangiitis, usually called GPA. It causes blood-vessel inflammation and can affect the nose, ears, sinuses, lungs and kidneys. The next step after a possible diagnosis is not simply learning a medicine’s name: it is understanding which organs need assessment, what the available evidence shows and how treatment will be checked. There is no single diagnostic test. A specialist combines the history, examination and investigations, then plans treatment according to the organs involved and the seriousness of the illness. [1]
General patient education, not a diagnosis or an individual treatment plan. Medication decisions belong with your treating clinicians. Drug-safety and regulatory information was checked on October 12, 2026; later advice may change.
First, decide whether a symptom can wait
Severe breathing difficulty is an emergency even without blood. Call your local emergency number if you are gasping, choking or unable to speak normally because of breathlessness. Do not wait for a callback from the usual clinic. [29]
Coughing blood needs prompt attention. Even a few flecks or streaks warrant urgent medical advice. Call your local emergency number or seek emergency care for more than a few spots or streaks, or blood with difficulty breathing, chest or upper-back pain, or a racing heartbeat. Do not drive yourself when seriously unwell. Infection and blood clots can also cause bleeding, so you do not need to establish that GPA is responsible before asking for help. [4]
Markedly reduced urine needs urgent assessment. Seek urgent medical help if you are passing much less urine than usual, particularly with new leg swelling, vomiting, unusual sleepiness, confusion or breathlessness. These can accompany acute kidney injury. Causes include infection, dehydration, obstruction and inflamed blood vessels; the response depends on the cause. Kidney injury can also occur without obvious symptoms. Do not wait for kidney pain, visible blood or the next routine appointment to seek advice about a significant change. [5]
Protect your sight. Sudden loss of vision or sudden severe eye pain requires emergency care. Other eye pain, a red painful eye, light sensitivity or a new change such as blurred vision needs urgent professional assessment. Tell the service that you have, or are being investigated for, GPA and describe when the problem began. An eye examination is needed to establish the cause; a photograph or resemblance to a previous episode cannot decide the treatment. Seek an urgent eye-care service or your local urgent medical pathway rather than waiting for a scheduled rheumatology visit. [6]
Prepare one useful account of what has changed
Start with a short timeline rather than a long list of suspected explanations. Write the first noticeable change, the changes that followed, any treatment already tried and what happened afterward. Use dates if you know them, or approximate periods if you do not. Separate your observation, such as “I started waking with a blocked nose,” from an interpretation such as “my vasculitis returned.” Include previous clinic letters or test results that another hospital may not have. You are helping the team reconstruct events, not expected to diagnose yourself.
Mention symptoms outside the area that prompted the referral. GPA can involve ears and hearing, nasal tissues, eyes, skin, joints and peripheral nerves as well as lungs and kidneys. Lung nodules sometimes produce no symptoms and can resemble infection or cancer on imaging. Narrowing below the vocal cords can interfere with breathing. New painful weakness in a hand, foot, arm or leg needs emergency medical assessment. Reporting these different changes together helps the clinician decide which specialists and investigations are needed; it does not mean every symptom necessarily comes from GPA. [2]
Sudden facial drooping, weakness affecting one arm, or slurred or unusual speech can signal a stroke. Call your local emergency number immediately rather than treating these as routine GPA symptoms. [3]
A useful opening question is: “Which findings make you suspect GPA, and what else are you considering?” Symptoms can build slowly or appear suddenly, and common problems such as tiredness, sinus discomfort or joint pain have many explanations. A symptom checklist cannot confirm the disease. If you already have a diagnosis, tell your specialist about new or returning symptoms rather than assuming the old label explains them. The team may need further blood tests, urine testing, imaging or a tissue sample. [1]
Bring a complete medicine list, including medicines from other specialists, nonprescription products and supplements. Mark allergies, previous reactions and medicines you no longer take. If the written list differs from what you actually use, explain that openly. Ask for an interpreter, accessible written information or a support person if these would make the discussion easier. Agree what you want a companion to do, such as taking notes or helping recall dates, while keeping decisions and privacy preferences with you.
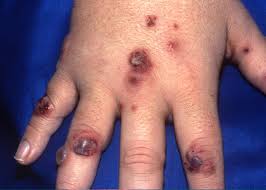
Skin changes deserve a description of location, onset and progression, rather than a diagnosis based on color alone. GPA can cause several different rashes, including raised red-purple spots, but skin appearance is only part of an assessment. Similarly, longstanding sinus symptoms or hearing changes may need a focused examination. Tell the clinician whether the problem is new, recurrent or continuously present and whether another service has already assessed it. [2]
Ask what each test can establish
Urine and blood tests answer different kidney questions. Damaged kidney filters can leak protein or blood into urine; the blood may be visible only under a microscope. Blood measurements such as creatinine help assess filtration. A person can have kidney disease with few noticeable symptoms, so normal-looking urine does not replace testing. Imaging can add information about kidney structure, while a biopsy may help identify the type of injury. Ask the clinician to explain the urine findings and filtration results together, including how they compare with earlier measurements. A single urine appearance or laboratory number is not a complete explanation of the kidney problem. [8]
Proteinuria and hematuria describe findings, not a particular disease: they mean protein and blood in urine. Several glomerular disorders can produce them, including conditions related to infection, diabetes and autoimmune disease. Finding a leak therefore leaves a second question: what is causing it? Ask which investigation is intended to clarify the cause and whether the new finding changes the urgency of assessment. [8]
ANCA: useful evidence, with important limits
ANCA means antineutrophil cytoplasmic antibodies. Testing looks for antibodies associated with certain forms of autoimmune vasculitis. The laboratory may report different antibody patterns or more specific antibody results. A positive test is evidence for the clinician to interpret, rather than a diagnosis printed on a laboratory form. ANCA testing is also used in other clinical settings, including some inflammatory bowel diseases. Its meaning depends on the symptoms and other investigations. Ask what was measured, why it was ordered and how it changes the assessment in your particular case. [7]
A negative ANCA result does not rule out GPA. EULAR recommends interpreting testing in the clinical context and using biopsy evidence where appropriate. Biopsy findings also depend on the tissue sampled: a nondiagnostic sample does not necessarily exclude disease elsewhere. Specialists balance the expected information against the procedure’s risks. In a presentation that strongly suggests organ-threatening vasculitis, necessary treatment should not be postponed solely to wait for tissue confirmation. Ask what remains uncertain and which additional evidence would resolve it. [10]
Biopsy: clarify both the purpose and the aftercare
A kidney biopsy provides small samples for a pathologist to examine. It can help distinguish inflammation, scarring and other abnormalities when blood and urine findings leave important questions unanswered. Before agreeing, ask what the result could change and how the team will reduce bleeding risk. Tell them about blood thinners, aspirin, other medicines, supplements and allergies; follow their instructions about preparation rather than stopping medicines yourself. Obtain the written recovery advice and emergency contact before leaving. Afterward, inability to urinate, dark or clot-containing urine, worsening biopsy-site pain, fever, faintness or significant wound changes require prompt medical help. A preliminary result may arrive before the complete report, so confirm who will explain both. [9]
Research scores do not replace a diagnostic consultation
The ACR/EULAR GPA classification criteria are designed to classify patients for research after small- or medium-vessel vasculitis has been diagnosed and competing explanations have been excluded. They are not a screening quiz for anyone with sinus symptoms or a positive antibody result. Adding up points without those prerequisites can be misleading. If a paper or online calculator gives a score, ask whether it was developed for diagnosis or research classification. A person’s investigation still needs the clinical assessment that comes before using the criteria. [11]
Close the loop on pending results
For each outstanding test, write down its purpose, the service responsible and the expected route for receiving the result. Ask when to contact that service if you have heard nothing. A result appearing in an online portal does not tell you whether someone has explained it or changed the plan. If a report includes an unfamiliar term, copy the term accurately and ask for its meaning. Keep a separate list of unresolved questions so that uncertainty remains visible at the next appointment instead of being mistaken for a confirmed conclusion.
Understand the decision before comparing medicines
Induction is treatment intended to bring active vasculitis into remission. Current practice considers which organs are at risk, rather than relying on how uncomfortable someone feels. The 2025 British Society for Rheumatology recommendations emphasize that active GPA can be potentially organ- or life-threatening. Rituximab or cyclophosphamide, generally with glucocorticoids, are established induction options. Methotrexate or mycophenolate may be considered for selected patients without organ- or life-threatening involvement. These are specialist choices, not interchangeable options to select from a list. Recommendations also depend on previous response and the patient’s circumstances. The guideline’s older avacopan advice must be read alongside the later regulatory changes described below. [12]
Ask the prescriber to complete three sentences in ordinary language: “We are treating…,” “We will judge improvement by…,” and “We will check treatment harm by….” Then discuss the practical tradeoffs: attending infusions, arranging blood tests, obtaining medicines, previous difficult side effects, fertility priorities and help at home. If cost or transport makes the proposed plan unrealistic, say so before leaving. Ask which parts are essential immediately and which decisions can be revisited. This turns a list of options into a plan you can actually follow.
If kidney function is worsening quickly
Kidney-threatening ANCA-associated vasculitis may require treatment while diagnostic work continues. KDIGO guidance advises against waiting for a biopsy result when the clinical presentation and antibody findings support the diagnosis and kidney function is rapidly deteriorating. Plasma exchange is an additional procedure considered only in selected circumstances, including particularly severe kidney disease, some lung bleeding with low oxygen, and overlap with anti-glomerular basement membrane disease. It is not required for everyone with GPA. Dialysis may be needed when kidneys cannot adequately support the body; the longer-term plan depends on recovery and ongoing assessment. Ask the kidney team what each proposed intervention is intended to achieve and what evidence would lead them to continue or change it. [14]
Give every medicine a purpose and a safety plan
Your medicine record should show what each item is for, the exact instructions you were given, who prescribes it and which service answers questions. Include medicines intended to prevent complications, not just those treating GPA. Record the latest change and the person who advised it, then remove obsolete versions of the schedule from everyday use. If two instructions conflict, ask the prescriber or pharmacist to reconcile them. Do not improvise a combined schedule. Ask for medicine-specific instructions for missed doses, illness and urgent adverse effects, because one rule will not fit every treatment.
Rituximab: prepare for infusion and later warning signs
Rituximab is given by infusion with professional monitoring. Serious infusion reactions can occur, so tell staff immediately about breathing difficulty, throat symptoms, chest discomfort, dizziness or a new rash during treatment. Screening for hepatitis B matters because the virus can reactivate, including in someone with a previous infection. The team also needs to know about current infections and past treatment reactions. Serious infections can develop after an infusion, and new neurological changes such as altered thinking, speech, vision or walking require immediate medical advice. Ask whom to contact after leaving the infusion unit and what to do if you become unwell before the next visit. Read the Medication Guide supplied with your particular product. [15]
Cyclophosphamide: discuss bladder, infection and fertility protection
Cyclophosphamide treatment requires blood and urine monitoring. It can increase infection risk, affect fertility and cause bladder problems; additional medicines may be prescribed for bladder protection or nausea. Blood in the urine needs immediate medical advice, even if kidney inflammation is already part of your diagnosis. Follow the urgent instructions supplied for your formulation rather than assuming this is an expected symptom. Discuss future fertility before treatment when circumstances allow, and tell the team promptly about a possible pregnancy. Ask how adverse effects and cumulative exposure will be reviewed. The medicine also carries longer-term cancer risks that belong in an individualized benefit-risk discussion, particularly when further courses are being considered. [16]
Glucocorticoids: make dose changes explicit
Prednisolone and related glucocorticoids can cause early sleep, appetite, stomach or mood changes, while longer exposure adds further risks. Report troublesome effects rather than simply enduring them or changing treatment independently. Increased thirst with frequent urination, signs of infection, new visual symptoms, unusual bleeding or severe abdominal symptoms need urgent medical advice. Severe dizziness, vomiting or marked weakness can also require urgent assessment. After sustained treatment, stopping suddenly can be dangerous; use the reduction plan provided by your clinician. If the tablet strength or written taper changes, ask the pharmacist to confirm exactly what you should take. A taper is a prescription, not something to reconstruct from another patient’s experience. [17]
Ask whether you should carry a steroid emergency card. Steroid treatment can reduce the body’s own cortisol production, and a clinician or pharmacist can assess your risk. Show the card when seeking medical or dental care, particularly before surgery or an invasive procedure. It alerts professionals that additional steroid support may be needed; it is not an instruction to increase the dose yourself. [30]
Methotrexate: check the weekly schedule carefully
For inflammatory conditions, methotrexate is usually prescribed once weekly. Mistaking a weekly instruction for a daily one can cause severe, sometimes fatal harm. Confirm the named day and prescribed amount with the pharmacist, and store weekly medicine separately from daily tablets. Taking more than prescribed or taking it daily by mistake needs urgent medical advice; do not wait for symptoms. Blood tests check blood cells, liver and kidney function during treatment, with the schedule set by your team. Folic acid may also be prescribed to reduce some adverse effects, using its own instructions. Ask how the two medicines fit together and whom to contact about a missed dose instead of doubling or rearranging doses yourself. [18]
Azathioprine: do not overlook monitoring or new symptoms
Azathioprine can affect blood-cell production and the liver or kidneys, so regular blood checks remain important even when you feel well. Fever or chills, unusual bruising or bleeding, severe abdominal or back pain and other significant new symptoms need urgent advice and the medicine-specific stopping instructions in your patient leaflet. Serious allergic symptoms, especially swelling around the mouth or throat or breathing difficulty, require emergency help. Long-term use can increase certain cancer risks, including skin cancer; discuss sun protection and any concerning skin change. Nausea can occur, but persistent or severe problems still deserve review. Do not let a general “keep taking your medicines” message override explicit urgent adverse-reaction instructions. [19]
Avacopan: check the date and the country
If avacopan, marketed as Tavneos, appears on your medicine list or in an older GPA guide, arrange a discussion with the prescriber about current advice. On March 31, 2026, the FDA warned about serious drug-induced liver injury, including fatal cases and vanishing bile duct syndrome. Contact a health professional immediately for possible liver-injury symptoms such as yellow eyes or skin, dark urine, pale stools, unusual itching, worsening tiredness, nausea, vomiting or right-upper abdominal pain. The alert calls for liver monitoring and clinician-directed evaluation or treatment changes. Do not wait for the next planned blood test when symptoms appear. Ask who will review your liver results and arrange any alternative treatment. [20]
United States, checked October 12, 2026: the FDA’s April 27 announcement describes a proposal to withdraw approval because of concerns about the reliability of the evidence supporting effectiveness, alongside safety concerns. The agency states that the product remains on the market until the applicant removes it or the FDA Commissioner mandates removal. A proposal is not a completed withdrawal. The FDA advises patients and clinicians to discuss whether treatment should be used or continued while the decision is pending. This guide does not present avacopan as an uncomplicated routine choice. [21]
European Union, checked October 12, 2026: the European Commission issued its final binding decision on August 4, 2026, revoking Tavneos authorization. EMA says new patients should not start treatment and existing patients should be switched to alternatives under medical supervision. Its advice also addresses continued liver monitoring during discontinuation. This is a completed EU regulatory action, distinct from the US proposal. Contact your specialist about the advice applying where you receive care, including a supervised transition if required. Do not replace treatment yourself or rely on an older webpage’s description of approval. [22]
Before the next treatment cycle, review prevention
Infections and exposure instructions
Infection prevention should be discussed before immune-suppressing treatment and revisited when treatment changes. Depending on the medicine and personal risks, assessment may include tuberculosis, hepatitis and other infection history. Prior residence, travel and exposure can matter. Some patients need preventive treatment against Pneumocystis jirovecii pneumonia, often called PJP; this is different from treating an infection that has already developed. The choice depends on treatment intensity, other risks, allergies and tolerability. Ask whether prevention is needed, what it covers and when it will be reassessed. Also obtain instructions for a relevant infectious exposure, such as chickenpox, rather than waiting to become ill before asking what to do. [23]
Vaccines and their timing
Give the team your vaccine record before treatment where possible. Immune suppression can change both vaccine safety and the strength of the immune response. Live vaccines may be unsuitable during significant immune suppression, whereas non-live vaccines generally raise different questions about effectiveness and timing. B-cell-depleting treatment such as rituximab can reduce responses, so the timing of vaccination may need coordination with treatment. Ask about the vaccines appropriate to your age, location, health conditions and planned travel. Do not independently postpone essential GPA treatment, stop medicines or assume that every vaccine must be avoided. The clinician can decide what to give now, what to defer and whether later doses are needed. Tell every vaccination provider about current immune-suppressing medicines. [24]
Household members should also ask about their own age- and exposure-appropriate vaccines. Your immune suppression does not mean that everyone living with you must avoid vaccination. Some situations need specific precautions, such as a rash after a household member’s chickenpox vaccine. Ask the vaccination service about these details rather than cancelling a family member’s vaccine based on rules intended for the person receiving immune-suppressing treatment. [24]
Bones, falls and long-term steroid exposure
If glucocorticoids are expected to continue, ask for a fracture-risk review. The ACR osteoporosis guideline considers factors such as previous fractures, age, falls and steroid exposure, with bone-density and vertebral assessment when appropriate. Prevention is not limited to taking a supplement: some people need prescribed bone-protective treatment based on their risk. Discuss calcium and vitamin D intake, suitable activity and any history of back pain or fractures. Kidney disease and pregnancy plans may influence which options are appropriate. Ask what the initial assessment showed and when it will be revisited. Do not add high-dose supplements or borrow an osteoporosis prescription without checking that it fits your health and medicines. [26]
Fertility, pregnancy and breastfeeding
Bring up reproductive plans early, including the possibility that you may want children later. Cyclophosphamide can affect fertility, making discussion of preservation options time-sensitive before treatment when feasible. Pregnancy planning usually aims for controlled disease and pregnancy-compatible medication, coordinated between the relevant specialists and maternity team. A medicine’s suitability can differ before conception, during pregnancy and while breastfeeding; advice for the person taking treatment and their partner is not always identical. Ask about contraception, any required waiting period and who will review the complete medicine list. If pregnancy occurs unexpectedly, contact the team promptly rather than stopping all treatment: uncontrolled inflammatory disease also carries risks. A plan should include care after birth, not only medication changes before conception. [25]
At follow-up, distinguish control from recovery
Remission means the absence of active disease attributable to vasculitis; it can occur while someone is still receiving treatment. Maintenance aims to prevent recurrence after induction. Rituximab, azathioprine and methotrexate are among the options used in appropriate circumstances. Duration is individualized using the disease course, treatment response, risks and preferences. The ACR/Vasculitis Foundation guideline advises against changing immune suppression solely because ANCA levels rise or remain positive. Ask what clinical evidence supports the team’s assessment and what will be reviewed before reducing maintenance. Relapse means active disease has returned after remission, not simply that an antibody test remains abnormal or that every symptom has disappeared more slowly than expected. [13]
Persistent symptoms may reflect active inflammation, established damage, infection or treatment effects. EULAR recommends structured assessment to distinguish these possibilities rather than automatically escalating immune suppression. Kidney tissue can sometimes help separate active injury from damage when the clinical picture is unclear. Immunoglobulin measurements before rituximab courses help identify reduced antibody defenses. Ask whether the symptom and the objective findings point in the same direction, and what further assessment is needed if they do not. [10]
When a change occurs, describe the function you have lost as well as the symptom. “I used to manage the stairs without stopping; now I stop halfway” is more informative than “my breathing is worse.” For fatigue, describe what you could manage last week, what you can manage now and whether the change was sudden or gradual. Record any recent medication change or infection exposure without deciding that it caused the problem. Your task is to report the pattern clearly; the clinical team’s task is to identify the cause and urgency.
Do not wait for proof that an illness is a flare
Sepsis is a life-threatening reaction to infection and can develop quickly. Call emergency services for a severely unwell person with signs such as new confusion, serious breathing difficulty, or blue, grey, pale or blotchy skin. Someone with sepsis may not have every listed symptom. Tell responders about immune-suppressing treatment and bring the medicine list if readily available, but do not delay seeking help to gather paperwork. A familiar GPA diagnosis should not distract from a rapidly worsening illness that needs immediate assessment. [28]
Write down the contact plan while you are well: the daytime specialist number, the out-of-hours service and the local emergency number. Ask which messages are read promptly and which are for routine questions. If you send a nonurgent message, include the onset, what changed, relevant recent treatment and a callback number. If symptoms need urgent care, use the urgent route instead of waiting for an unread portal message. Ask the team to explain their illness instructions in advance, including who decides whether a particular medicine needs to be withheld.
Make the plan workable between visits
Follow-up continues after symptoms improve. The NHLBI advises people with vasculitis to report new health changes and medication effects, and to attend monitoring selected for their disease and treatment. If treatment is eventually stopped under supervision, surveillance for recurrence still matters. New episodes can involve the same symptoms as before or different ones. Keep your actual experience visible in the review rather than assuming a previous pattern must repeat. Ask what ongoing checks are necessary and how to obtain advice if the next appointment is months away. Feeling better is welcome, but it does not tell you on its own that all monitoring or treatment can end. [3]
If GPA has left chronic kidney disease, ask for a kidney-protection plan alongside vasculitis care. This may include individualized blood-pressure management, review of filtration and urine protein, and advice from a renal dietitian. Nonprescription painkillers and cold medicines can contain NSAIDs such as ibuprofen or naproxen, which may be harmful to kidneys. Check new products and supplements with a pharmacist who knows your kidney history. Nutrition, fluid advice and activity should match your circumstances rather than a generic “detox” plan. Bring questions about what you can eat, drink or take for pain to the team; do not assume that a product described as natural is suitable. [27]
Practical barriers deserve a place on the agenda. Tell the service if laboratory opening hours conflict with work, prescriptions arrive late, transport is unreliable or instructions are difficult to read. Ask whether appointments or blood tests can be coordinated and who can help resolve a supply problem before you run out. If a family member helps, agree which tasks they will handle and what information you want shared. Keep the system simple enough to use on a difficult day: one current medicine list, one appointment record and a clear place for questions.
| Point in care | Useful questions to take with you |
|---|---|
| Diagnosis discussion | Which findings are established, which remain uncertain and which alternative explanation is still being checked? Who will explain the pending results? What should prompt contact before the next appointment? |
| Starting or changing treatment | What is the purpose of this change? How will benefit and harm be assessed? Who arranges monitoring, renews prescriptions and answers urgent medication questions? Can I repeat the instructions back to check that I understood them? |
| Reviewing the longer-term plan | Which problems need continuing treatment, rehabilitation or another specialist’s input? What matters most to me over the next few months? What information would help us revisit this decision, and when will we discuss it again? |
Finish a consultation by naming the next concrete step and who is responsible for it. That might be receiving a biopsy explanation, booking a blood test, obtaining a revised medicine list or arranging a specialist review. Ask for a written summary if the plan is complicated. For background vocabulary, Sly Academy’s guide to how inflammation affects the body can help with the general concepts. Keep questions about your own results, medicines and changing symptoms with the team that knows your case.
Video note: the original embedded video is retained separately for context. It has not been independently medically reviewed for this update and may not reflect current treatment or 2026 drug-safety advice.





