
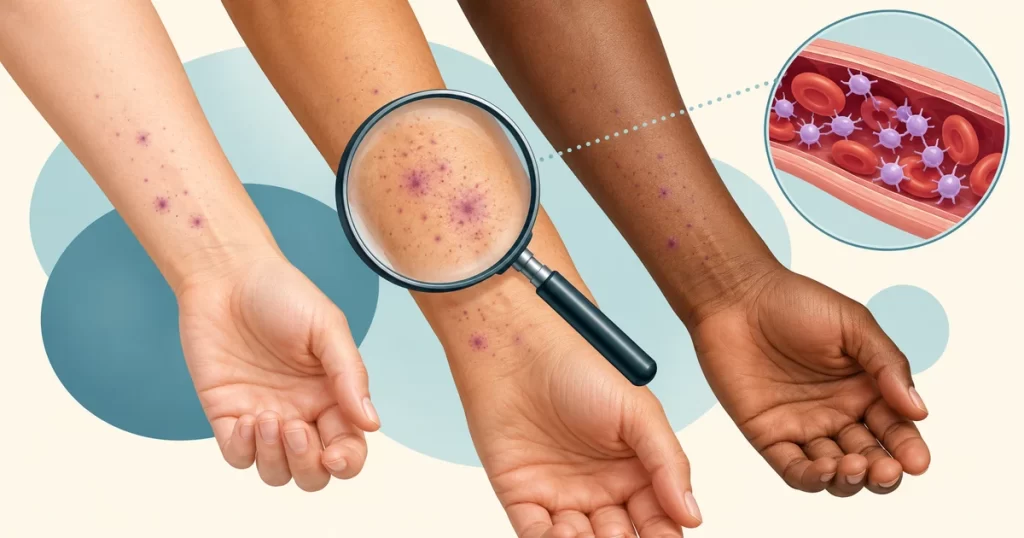
Purpura means bleeding into the skin or a surface lining, such as the inside of the mouth. It can appear as small spots, larger patches, or bruises. The word describes a finding, not one particular disease. A person with fragile skin, someone with a low platelet count, and a child with inflamed small blood vessels can all develop purpura, but they need different assessment and care.
The most useful questions are: Is the person unwell? Is there bleeding anywhere else? Are the marks new, spreading, or unexplained? Understanding those questions is more helpful than trying to identify a diagnosis from a photograph. This guide explains the main patterns, the tests clinicians may use, and what a sensible follow-up plan looks like.
Get emergency help for a non-fading rash with serious illness. Call your local emergency number if new purple or pinpoint spots occur with fever and marked illness, confusion, unusual sleepiness, breathing difficulty, collapse, a severe headache or stiff neck, or rapid deterioration. A rapidly spreading rash also needs immediate assessment. Do not wait for every symptom, a larger rash, or a positive glass test.
What purpura looks like
Purpura forms when blood escapes from vessels into nearby tissue. Because that blood is outside the vessels, the color usually does not disappear when pressure is applied. Clinicians call this non-blanching. By contrast, some redness caused by widened surface vessels temporarily becomes paler under pressure. This distinction can help describe a rash, but it cannot establish its cause or tell you that it is safe.
Appearance varies with skin tone, lighting, depth, and the age of the bleeding. Marks may look red, purple, brown, or unusually dark. They may be easier to feel than to see, or become more noticeable when compared with nearby unaffected skin. A camera can distort color, so describe changes in your own words as well as taking photographs.
Petechiae, purpura, and bruises
These terms overlap. Petechiae are the smallest pinpoint spots. Ecchymoses are larger areas of bleeding, commonly called bruises. Purpura is often used for intermediate-sized lesions or as an umbrella term for bleeding beneath the skin. Exact size cutoffs differ between references; measuring a spot at home does not distinguish a harmless cause from a serious one.
A flat patch is described differently from palpable purpura, which feels raised when a clinician examines it. Raised purpura can point toward inflammation of small blood vessels. It is a clue rather than proof: the whole examination, symptoms, and sometimes a skin biopsy are needed. Spots that itch, hurt, blister, ulcerate, or occur around swollen joints deserve a clear description rather than the assumption that all purple marks are ordinary bruises.
The glass test has important limits
Pressing a clear glass against a rash may show whether it fades. However, an early meningitis or sepsis rash can change over time, and serious infection can occur without any rash. On darker skin, color changes can be harder to recognize. If someone seems seriously ill, seek help based on their condition; repeated testing or searching for matching images can waste valuable time.
When to seek medical care
The following guide helps organize urgency. It cannot replace individual advice, especially for babies, pregnant people, people taking medicines that affect clotting, or anyone with an established bleeding disorder. If you are uncertain about a new unexplained non-blanching rash, contact an urgent medical service rather than waiting several days to see what happens.
| Situation | What to do |
|---|---|
| New spots with serious illness, rapid spread, confusion, collapse, or breathing problems | Seek emergency help now. Describe both the rash and the change in the person’s condition. |
| Bleeding that will not stop, vomiting blood, black tarry stools, or significant bleeding with faintness | Get emergency assessment. Tell the team about anticoagulants, antiplatelet drugs, and any known platelet disorder. |
| New unexplained purpura in an otherwise well person, increasing bruising, gum or nose bleeding, or blood in urine | Seek same-day medical advice for a new unexplained non-blanching rash, even if you feel well. Increasing bruising or other bleeding also needs prompt assessment. |
| A familiar pattern already diagnosed as skin fragility, without new symptoms | Follow the existing plan, but arrange review if the distribution, frequency, associated bleeding, or general health changes. |
A severe new headache, weakness on one side, trouble speaking, or a seizure needs emergency care whether or not purpura is present. After a significant head injury, a person taking an anticoagulant or living with a bleeding disorder should obtain urgent advice even if external bruising looks small. Visible skin marks do not reliably measure bleeding elsewhere.
Why purpura happens: platelets, vessels, and clotting
Stopping bleeding requires several systems to work together. Blood vessel walls provide a barrier. Platelets gather at an injury and help form an initial plug. Clotting proteins strengthen that plug. A problem affecting any of these systems can produce bruising or bleeding, and more than one problem may exist at the same time.
Too few platelets or platelets that do not work properly
Thrombocytopenia means a low platelet count. It can result from reduced production in the bone marrow, increased destruction or use of platelets, or platelets being held in an enlarged spleen. Infection, medicines, immune disorders, and other illnesses are possible contributors. The blood count helps narrow the possibilities, but it does not identify the reason by itself.
Platelets can also be present in a normal number yet function poorly. Certain medicines affect platelet activity, and inherited or acquired conditions can do the same. This is one reason a normal platelet count does not automatically explain away repeated nosebleeds, heavy menstrual bleeding, or unexplained bruising. Persistent symptoms deserve interpretation alongside the history and other tests.
Fragile or inflamed blood vessels
Purpura can occur with a normal platelet count when vessel support is fragile or the vessel wall is inflamed. Age-related skin thinning and accumulated sun damage can make minor bumps leave conspicuous bruises. Vasculitis is different: inflammation damages blood vessel walls, sometimes involving organs as well as skin. These mechanisms should not be treated as interchangeable. For a related systemic condition, read our guide to ANCA-associated vasculitis.
Location and texture can guide the examination. Recurrent patches on exposed forearms suggest a different set of possibilities from raised spots on both lower legs with abdominal pain. However, neither pattern provides a diagnosis by itself. Medication effects, pressure, injury, and overlapping illnesses can alter the usual appearance.
Clotting proteins and broader illness
Liver disease, some inherited bleeding disorders, and medicines that reduce clotting can cause excessive bruising or bleeding. Serious systemic illness can disrupt several parts of clotting at once. The term “non-thrombocytopenic purpura” simply means the platelet count is not low; it does not mean that every other component of blood clotting is normal or that further investigation is unnecessary. For more about severe liver dysfunction, see our guide to liver failure and specialist care.
Important causes and how their care differs
Immune thrombocytopenia, or ITP
In ITP, immune activity lowers the platelet count. The presentation ranges from no symptoms to skin spots, bruising, and bleeding from the nose, gums, or other sites. Diagnosis involves excluding other explanations. Some people need observation with planned blood tests, while others require treatment because of bleeding risk, symptoms, or their circumstances.
Treatment can include a short course of corticosteroids, intravenous immunoglobulin, or other therapies that reduce platelet destruction or increase production. These treatments have different benefits and risks; they are not a general prescription for purpura. Decisions also consider age, other medicines, procedures, occupation, and activities. A person should leave with a clear explanation of which symptoms require urgent help.
IgA vasculitis, previously called Henoch–Schönlein purpura
IgA vasculitis affects small blood vessels and is more common in children, although adults can develop it. Purpura often involves the legs and buttocks and may accompany joint pain, abdominal pain, or kidney involvement. The rash can improve while urine abnormalities remain, so skin appearance alone cannot confirm recovery.
Care may include symptom relief, assessment of abdominal symptoms, and scheduled blood pressure and urine checks. Kidney findings can change the need for specialist review and treatment. Severe abdominal pain, gastrointestinal bleeding, reduced urine, or other worsening symptoms need prompt reassessment rather than waiting for the next routine visit. Follow-up timing should come from the treating team.
Other cutaneous small-vessel vasculitis
Small-vessel vasculitis may remain limited to the skin or occur as part of a wider illness. Sometimes a medicine or infection is implicated; sometimes no trigger is found. A clinician may take a biopsy of a suitable lesion and order tests guided by the history. Different samples or timing may be needed for particular laboratory techniques.
Management can involve addressing a trigger, reducing discomfort, and treating persistent or organ-threatening inflammation. Systemic immunosuppressive treatment is not needed for every skin-limited episode. Conversely, calling a rash “just vasculitis” without checking for kidney, lung, nerve, or gastrointestinal symptoms can miss an important distinction.
Actinic purpura and age-related skin fragility
Actinic purpura, also called senile purpura, often produces bruiselike patches on older adults’ hands and forearms. Thin, sun-damaged skin offers less support to small vessels. A minor knock may be enough, and sometimes no injury is remembered. Corticosteroids and medicines that affect bleeding can make the bruising more noticeable.
Once the diagnosis is established, care focuses on protecting fragile skin and reviewing contributing factors. The patches can leave residual brown discoloration as they fade. This familiar pattern should not become an explanation for every future bruise: new bleeding from the mouth, widespread spots, or a major change in health still warrants assessment.
Capillaritis and pigmented purpuric eruptions
Capillaritis can cause small reddish-brown speckles and patches, often on the lower legs. Blood leaking from tiny surface vessels leaves pigment behind. Some forms are symptom-free; others itch. These conditions can look persistent because the color does not disappear immediately when active leakage settles.
A clinician may distinguish capillaritis from inflammatory vasculitis through its appearance and, when needed, investigation. Treatment may focus on symptoms or possible contributing factors, and a complete rapid clearance is not always realistic. Do not assume that a longstanding brown patch and a newly painful purple eruption have the same cause.
Pressure, minor injury, and mechanical causes
Small localized spots can follow pressure or strain, including bouts of coughing or vomiting. The timing and distribution help clinicians assess whether this is a plausible explanation. An obvious event is useful information, but it should not override fever, worsening illness, widespread lesions, or bleeding elsewhere. In a child, unexplained bruising should be assessed in the context of development, mobility, and the whole examination.
Rare but dangerous causes
Thrombotic thrombocytopenic purpura, or TTP, is a medical emergency involving small-vessel clots, low platelets, and injury to red blood cells. It can affect the brain, kidneys, and other organs. It is different from ITP despite the similar abbreviation. Urgent hospital treatment may include plasma exchange and targeted medicines; a rash is neither necessary nor sufficient for diagnosis.
Severe infections, including meningococcal infection, can also produce a rapidly changing non-blanching rash. Other critically ill patients develop widespread disruption of clotting. These conditions require urgent treatment of the underlying emergency. They should not be managed at home as a cosmetic skin problem.
Painful branching patches or skin breakdown
Some purpuric lesions have an irregular, branching or netlike shape, sometimes with a dusky center, blisters, or damaged skin. This pattern is called retiform purpura and can reflect impaired blood flow as well as inflammation. New painful lesions, blackening skin, or rapidly developing ulcers need urgent assessment. They should not be treated with a cosmetic bruising cream while waiting to see whether they fade.
How clinicians investigate purpura
The history and examination come first
The clinician will want to know when the marks began, whether new ones are appearing, where they occur, and whether there was an injury, illness, new medicine, or dose change. They may ask about bleeding after dental work or surgery, periods, pregnancy, diet, alcohol use, and family bleeding problems. These questions help distinguish a recent change from a longstanding tendency.
Examination can include the skin, mouth, joints, abdomen, and signs of systemic illness. Blood pressure matters when kidney involvement is possible. A single clear photograph is useful for documenting change, but it cannot replace checking whether lesions are raised, assessing hydration and circulation, or examining areas that are difficult to photograph.
Common initial tests
A complete blood count measures platelets and other blood cells. A blood film, or smear, allows their appearance to be examined. PT and aPTT are clotting tests that can help identify some clotting abnormalities. Kidney and liver blood tests may be appropriate. The exact selection depends on symptoms and clinical findings rather than an identical panel for everyone.
A urine test is particularly useful when vasculitis is suspected because blood or protein can be present without obvious urine changes. Additional investigations might look for infection, an immune condition, or a specific bleeding disorder. Skin biopsy, specialist platelet testing, or bone marrow examination is reserved for situations where the findings justify it; none is automatically required for every purple mark.
What a normal result can and cannot tell you
“Normal blood tests” is not a complete diagnosis. Ask which tests were done and what question they answered. A normal platelet count does not exclude vessel inflammation or every platelet function problem. Normal screening clotting tests do not rule out every bleeding disorder. Equally, an isolated unexpected result sometimes needs confirmation before a conclusion is drawn.
The practical issue is whether the results explain the symptoms and support a safe plan. If lesions continue appearing, bleeding increases, or new symptoms develop, follow the reassessment instructions. Returning for review is appropriate when the clinical picture changes, even if an earlier examination was reassuring.
Medication review: an essential part of assessment
Bring a complete list of prescriptions, nonprescription pain relievers, vitamins, herbal products, and recent short courses of medicine. Include what you actually take and when you started it. A photograph of the packaging can be more reliable than remembering a brand name. Tell the clinician about injections, creams, and medicines borrowed or bought without a prescription too.
Anticoagulants reduce the formation of clots; antiplatelet medicines reduce platelet activity. Both can increase bruising or bleeding, but their purposes and monitoring differ. Corticosteroids can contribute to skin fragility, while some medicines can trigger low platelets or vessel inflammation. An apparent connection in time is a reason to investigate, not proof that a drug caused the rash.
Do not stop an essential prescribed medicine on your own. Stopping an anticoagulant or antiplatelet drug can increase clot-related risks. Contact the prescriber promptly about new unexplained bleeding or bruising. For severe bleeding or serious illness, seek emergency care and bring the medication list.
Ask before adding aspirin, ibuprofen, naproxen, or supplements marketed for circulation or bruising. What is suitable depends on platelet function, kidney health, other medicines, and the reason for treatment. A pharmacist can help check interactions, but new purpura still needs clinical assessment when its cause is unclear.
Children, adults, and pregnancy: context changes the plan
Children
Many children with petechiae do not have a serious bacterial infection, but a sick child with a non-blanching rash needs urgent assessment. Parents should describe feeding, alertness, breathing, urine output, pain, and how quickly things changed. Do not delay because a child has only a few spots or because the rash does not resemble an online picture.
After a diagnosis, ask for practical instructions for nursery, school, sports, and overnight care. The plan should state whom to contact, which symptoms matter, and whether any activity restrictions apply. Avoid giving a child broad restrictions based on the word purpura alone; the underlying condition and current bleeding risk should guide advice.
Any newborn with petechiae needs prompt clinical review. In older children, a history of coughing or vomiting may help explain a localized pattern, but that explanation should be assessed rather than assumed. When seeking help, give the child’s age early in the conversation and say explicitly that the spots do not fade under pressure if you have observed this.
Adults and older people
Adults may have several contributing factors, such as sun-damaged skin, prescribed medicines, and another illness. Explain what has changed from your usual pattern. A new widespread eruption should not be dismissed merely because bruising has happened before. Likewise, a stable, diagnosed skin-fragility pattern does not necessarily require emergency care every time a small patch appears.
Pregnancy and the postpartum period
New unexplained bruising or petechiae during pregnancy or after delivery should be discussed promptly with the maternity team. A mildly reduced platelet count can occur in otherwise uncomplicated pregnancy, but pre-eclampsia and HELLP syndrome are among the serious alternatives that clinicians need to consider. Platelet changes have several possible causes, and the implications depend on blood pressure, other symptoms, blood results, and timing. Severe headache, visual disturbance, upper abdominal pain, breathlessness, collapse, or significant bleeding require urgent assessment. Do not infer the cause from the rash or from a previous pregnancy.
Living safely while the cause is being clarified
Record the date the marks appeared, the main affected areas, and any accompanying symptoms. If photographs are useful, use similar lighting and include an ordinary size reference without pressing or injuring the skin. A short daily note is usually easier to interpret than dozens of unlabelled images. Documentation supports care; it should never delay urgent treatment.
Avoid deliberately rubbing, scratching, or repeatedly pressing the lesions to test them. Protect fragile skin from bumps, and ask the treating team whether contact sports or other injury-prone activities need temporary modification. If you have an established bleeding disorder, follow its individual emergency instructions rather than substituting general internet advice.
For a small external cut, direct pressure is a basic first-aid measure. Persistent bleeding, recurrent bleeding, or bleeding with dizziness needs medical help. Report substantial menstrual bleeding, frequent nosebleeds, or mouth bleeding rather than treating them as unrelated inconveniences. These details can change both the investigation and the care plan.
If several clinicians are involved, keep one accessible summary of the diagnosis under consideration, recent test dates, medicine changes, and the named team responsible for follow-up. This is particularly helpful when urgent care, primary care, and a specialist have each seen only part of the story. Ask for clarification if two instructions seem to conflict rather than choosing between them yourself. If you have a dental appointment, operation, or other planned procedure, tell the team about unexplained bleeding and any investigation still in progress. Ask whether results or specialist advice are needed beforehand. Do not independently cancel essential care or change medication; give the teams enough information to coordinate a safe plan.
Try to leave each appointment with an explicit next step. “Watch it” is easier to follow when it includes what to watch, how long to wait, who will review the results, and what should trigger an earlier call. If language, transport, cost, disability, or caregiving responsibilities make follow-up difficult, raise that during the visit so the plan can be made workable.
Can purpura be prevented?
There is no single prevention strategy because purpura has many causes. Sun protection and reducing minor trauma may help protect fragile skin, but they do not prevent immune platelet disorders or all vasculitis. Medication review can reduce avoidable bleeding risks without assuming that necessary treatment should be withdrawn.
A balanced diet supports health, but taking extra vitamins is not a general treatment for purple spots. Severe vitamin C deficiency can cause bleeding-related findings, particularly in the context of a markedly restricted diet, but unexplained purpura should not be self-diagnosed as a deficiency. Supplements cannot substitute for investigating a low platelet count, infection, or organ involvement.
Keep recommended vaccinations and routine care up to date, and follow the infection-prevention advice attached to any immunosuppressive treatment or spleen-related care. No vaccine prevents every infection that can cause a rash. Prevention advice should target an established risk, not promise that purpura will never recur.
Questions worth taking to your appointment
- What is the working diagnosis, and what findings support it?
- Is the problem thought to involve platelet number, platelet function, blood vessels, or clotting proteins?
- Which tests are needed now, and who will contact me about the results?
- Do we need urine or blood pressure follow-up even if the rash improves?
- Which symptoms mean emergency care, and which should prompt a same-day call?
- Are any medicines or activities unsafe for me at present?
- When should the diagnosis be reconsidered if the marks keep returning?
Bring your own priorities too. For one person, the most urgent concern is whether they can work safely; for another, it is repeated nosebleeds, school attendance, an upcoming procedure, or understanding a blood result. Naming that concern helps turn a diagnostic label into a plan you can actually use.
Frequently asked questions
Does purpura always mean low platelets?
No. Vessel fragility, vasculitis, clotting problems, and local injury can cause purpura without a low platelet count. Platelet-related causes are important, but the term describes bleeding into tissue rather than its mechanism.
Can purpura go away without treatment?
Some lesions fade as the leaked blood is cleared, and some underlying conditions settle without specific treatment. That does not make an unexplained new rash safe to ignore. Whether observation is appropriate depends on assessment, accompanying symptoms, and a clear follow-up plan.
Is purpura contagious?
Purpura itself is a sign and cannot be passed from person to person. Some infections associated with a rash can spread, so infection-control advice depends on the actual diagnosis. Ask the clinician about school, work, or household precautions if an infection is suspected.
Can I tell how serious it is from the color or number of spots?
No. A few spots in a very unwell person can matter more urgently than a large familiar bruise in someone otherwise well. The rate of change, associated symptoms, medication history, examination, and appropriate tests provide the context that a photograph cannot.
What if the rash improves before my follow-up?
Keep planned follow-up unless the treating team advises otherwise. This is particularly important when urine tests, blood pressure, or repeat blood counts are part of the plan. Bring photographs showing the earlier appearance and explain whether any symptoms continued after the visible marks faded.
Key takeaway
Purpura is a visible sign of bleeding beneath a surface, with causes ranging from skin fragility to urgent systemic illness. Start with how the person feels and whether bleeding is occurring elsewhere. Seek urgent help for red flags, arrange assessment for unexplained new lesions, and use the eventual diagnosis to guide treatment, medicine decisions, and follow-up.
Sources
- MedlinePlus: Purpura
- DermNet: Purpura
- Merck Manual: Bruising and Bleeding
- NHS: Meningitis
- CDC: Meningococcal Disease Symptoms
- NICE: Meningitis and Meningococcal Disease Recommendations
- NHS: Anticoagulant Side Effects
- NHLBI: Platelet Disorders
- NHLBI: Thrombocytopenia
- NHS: Vasculitis
- NHLBI: Immune Thrombocytopenia
- NIDDK: IgA Vasculitis
- DermNet: Cutaneous Small-Vessel Vasculitis
- DermNet: Senile Purpura
- DermNet: Capillaritis
- Royal Children’s Hospital: Petechiae and Purpura
- NHLBI: Thrombotic Thrombocytopenic Purpura
- DermNet: Retiform Purpura
- DermNet: Bleeding and Bruising
- NHLBI: Diagnosing Platelet Disorders
- NHLBI: Living with Platelet Disorders
- NHLBI: Platelet Disorders and Pregnancy
- NHS: Pre-eclampsia
- NHS: Henoch–Schönlein Purpura
- NIH Office of Dietary Supplements: Vitamin C





