

General health information, not an individualized vaccination or treatment plan. Official sources checked editorially on 14 October 2026; this does not imply review by a licensed clinician. Follow your healthcare team and local public-health guidance.
Hep A vaccine: what it prevents and where to start
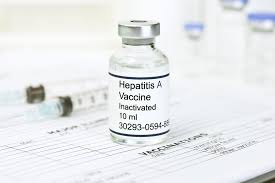
The Hep A vaccine helps prevent hepatitis A, a contagious infection that inflames the liver. Infection can follow close contact with an infected person or contaminated food or drink. Many people recover completely, but illness can disrupt everyday life for weeks or months. Older adults and people with existing liver disease are more vulnerable to serious complications. Vaccination is therefore worth discussing before a trip, after a relevant exposure, or when reviewing an incomplete immunization record. [1]
Feeling well does not reliably rule out infection. Young children may have few noticeable symptoms, and someone can transmit the virus before becoming visibly unwell. A vaccination decision should consider age, previous doses, health conditions and exposure, rather than whether a person looks healthy. This guide separates United States recommendations from examples of guidance elsewhere. [1]
Why protection involves more than careful eating
Hepatitis A spreads when the virus reaches the mouth, often through traces of stool that are too small to see. Close personal contact, caring for an infected person and certain sexual contact can create opportunities for spread. Food may become contaminated at several points, from production to preparation. A meal does not have to look spoiled for contamination to be possible. Domestic foodborne outbreaks can happen as well as travel-related infections. [2]
Handwashing and food precautions are useful, but they do not replace vaccination when it is recommended. The aim is to reduce several routes of exposure together. This is especially important when someone shares a home with an infected person or receives a public-health exposure notice. A promise to be more careful with food is not a substitute for timely advice about preventive treatment. [2]
Who is offered hepatitis A vaccination in the United States?
CDC recommends routine hepatitis A vaccination in early childhood and catch-up for unvaccinated children and teenagers. Adults are recommended vaccination when their circumstances increase infection risk or the chance of serious illness. An adult can also request protection without identifying a particular risk factor. The discussion should be practical and respectful; a person does not need to disclose a stigmatized circumstance simply to ask for this vaccine. [3]
- Risk groups include people using injected or noninjected drugs, men who have sex with men, travelers to relevant destinations, people experiencing homelessness, certain laboratory workers, and close contacts of some international adoptees. [3]
United States recommendations do not automatically require vaccination solely because someone works in food service, healthcare, childcare or sewage work. Other personal risks or outbreak instructions may still make vaccination appropriate. Occupational advice differs between countries. [3]
Chronic liver disease includes more than advanced cirrhosis. The adult schedule also identifies chronic hepatitis B or C, fatty liver disease, alcohol-related liver disease and autoimmune hepatitis among relevant conditions. HIV infection is another indication. If a liver diagnosis is new, add vaccine review to the discussion rather than assuming vaccination is only for travelers. Your clinician can interpret the diagnosis and your existing vaccination history together. [5]
People expecting close contact with a child adopted internationally from a country where hepatitis A is more common should ask about vaccination while the adoption is being planned. This can include household members and regular babysitters during the first 60 days after arrival. Planning early creates time to review records and begin protection before close contact starts. [5]
Routine and catch-up schedules for children
The United States routine single-antigen course contains two doses, beginning at age 12–23 months. There must be at least six months between those doses. Children and adolescents through age 18 who missed vaccination should complete catch-up vaccination. If one valid dose was given after the first birthday, the next step is usually to complete the course at the appropriate interval. The clinic checks the actual dates, not simply the number of entries on a card. [4]
A school-age child who never received hepatitis A vaccine can still benefit from catch-up. Bring records from earlier practices or another country, including the product name if available. A dose given before age 12 months for travel has special rules and does not count as one of the routine two doses. Ask the clinic to explain which doses count and write down the remaining plan. [4]
Single-antigen and combined vaccines: United States schedules
Single-antigen means the product targets hepatitis A alone. A combined vaccine covers hepatitis A together with hepatitis B. These are different viruses, so a record showing only hepatitis B vaccination does not establish hepatitis A protection. Neither option prevents hepatitis C, for which there is no vaccine. Product choice depends on which protection is needed, age, previous vaccines and available time. [11]
| Product | Protection and licensed age | Usual course |
|---|---|---|
| Havrix | Hepatitis A only; licensed from 12 months | Two doses, with the second usually 6–12 months after the first. [6] |
| Vaqta | Hepatitis A only; licensed from 12 months | Two doses, with the second usually 6–18 months after the first. [7] |
| Twinrix | Hepatitis A and B; United States use from age 18 | Standard course at the first visit, one month and six months. An accelerated four-dose course is available for appropriate adults. [8] |
Havrix has age-specific formulations, so an adult appointment and a toddler appointment are not interchangeable product orders. The clinician selects the formulation and injection technique; this table is a planning overview, not an instruction for self-administration. The product information also explains that protection is not guaranteed for every recipient and that an unrecognized infection already incubating at vaccination may still develop. [6]
Vaqta also has separate pediatric/adolescent and adult formulations. Its permitted interval for the second dose is not identical to the usual Havrix window. A reminder saying “hepatitis A booster due” therefore needs to be read with the original product and vaccination dates. Ask the clinic to put the next recommended appointment in your record before leaving. Ask which formulation applies to your age rather than choosing a product from a photograph of someone else’s vaccine. [7]
The United States accelerated Twinrix course uses doses on days zero and seven, then between days 21 and 30, followed by another dose at 12 months. Those early appointments do not replace the final one. It is useful only when clinically appropriate and logistically achievable. Tell the travel clinician if you have already received separate hepatitis A or B doses; combining old and new products requires a deliberate completion plan. [8]
Late doses, missing records and future boosters
A delayed hepatitis A series generally does not need to begin again. Arrange a record review and completion rather than repeating the first dose yourself. Doses given too close together are different: the clinic must check whether they meet the minimum interval. [9]
Another single-antigen brand can generally complete a course when the original is unavailable or unknown. Combined vaccines need separate assessment. Routine boosters after completion are not recommended for healthy people under United States guidance; impaired immunity can change the follow-up plan. [9]
Protection develops over time and is designed to last well beyond a single journey. CDC describes persistent antibodies at least 20 years after a completed two-dose adult course, while the exact duration of protection remains uncertain. This supports completing the course without promising that every individual has lifelong protection. A vaccination date and a finished series are more useful records than an assumption based on having traveled safely before. [18]
Travel: arrange protection as soon as a trip is planned
Discuss hepatitis A before travel to countries with substantial transmission, even for a short visit. If departure is less than two weeks away, still contact a travel service. Travelers older than 40, people with weakened immunity and those with chronic liver disease may need immune globulin alongside vaccination after a risk assessment. Give the clinician the full itinerary and departure date. A last-minute appointment can still be useful, but it cannot guarantee immediate protection. [10]
Immune globulin contains antibodies obtained from human plasma. It offers temporary protection rather than training the immune system in the same way as a vaccine. It may be considered when vaccination is unsuitable or when extra short-term protection is needed. It is not simply another brand of hepatitis A vaccine. Let the clinician decide whether the situation calls for vaccine, immune globulin, both or neither. [11]
Infants traveling internationally need a separate plan
United States guidance recommends an additional travel dose at ages 6–11 months when hepatitis A protection is indicated. This travel dose does not count toward the regular childhood course. The child still needs the routine two-dose series beginning from age 12 months, with the required spacing. Mark the early dose clearly in the record so a later clinician does not mistakenly treat the course as complete. [13]
For a baby younger than six months, a clinician may recommend immune globulin before relevant travel. Planning must also account for other childhood and travel vaccines. In particular, immune globulin can interfere with the response to certain live vaccines, including measles-containing vaccination. Do not rearrange those appointments independently. Ask the pediatric or travel team to produce one coordinated schedule covering the trip and the months afterward. [13]
United Kingdom and other local guidance
In the United Kingdom, hepatitis A vaccination is risk-based rather than routinely offered to everyone in childhood. NHS guidance identifies relevant travel, close contact with an infected person, long-term liver disease and certain other risks as reasons to discuss vaccination. A GP or travel service can assess whether it is indicated. Where work creates a relevant exposure risk, the employer should arrange occupational advice. [19]
UK products and age approvals differ from those in the United States. The Green Book describes single-antigen vaccines and combinations with hepatitis B or typhoid. Do not copy a United States Twinrix age limit into a UK booking decision or assume the American early-infant travel recommendation applies locally. Seek specialist advice for an infant traveling abroad. [20]
UK travel assessment considers the itinerary, trip length and activities. Vaccination is preferably arranged at least two weeks before departure, although late consultation can still help. Bring names of vaccines received overseas so the clinician can recognize combination products and apply the local schedule. [20]
Australia also uses its own recommendations, funding arrangements and product approvals. Its handbook includes hepatitis A advice for relevant travelers, people with chronic liver disease and particular occupational or community settings. For example, its occupational recommendations include early-childhood educators and sewage workers. That illustrates why a job-based recommendation from one country should not automatically be treated as a worldwide rule. [21]
If you are moving between countries during a vaccine course, ask the receiving clinic to review the written history before booking. The same brand name can have different locally approved age ranges or presentations. The practical goal is a documented, valid course under the guidance applying where care is provided, rather than trying to assemble a schedule from unrelated websites. [21]
National vaccination policies reflect local transmission, population immunity and assessments of cost-effectiveness. WHO describes vaccination, sanitation, safe water and food safety as complementary prevention measures. A country choosing targeted vaccination does not mean the vaccine is unnecessary everywhere, and a routine childhood program does not mean every adult is already protected. When reading an international guide, identify its country and intended population before applying its schedule to your own family. [22]
Pregnancy, breastfeeding and immune-system conditions
Pregnancy is not an automatic reason to avoid hepatitis A vaccination. CDC recommends it during pregnancy when there is increased risk of infection or serious consequences, such as relevant travel or chronic liver disease. The vaccine uses inactivated virus. Pregnancy safety data are limited, so the discussion should weigh exposure risk and expected benefit rather than describe the decision as either universally necessary or completely risk-free. [14]
Tell the clinician if you are pregnant, might be pregnant or are breastfeeding. Breastfeeding generally does not prevent receiving an indicated hepatitis A vaccine. If a trip or a recent exposure is involved, explain that timing immediately rather than postponing the conversation until after pregnancy. Your maternity clinician and vaccination service can coordinate the decision with the rest of your care. [14]
People taking medicines that suppress immunity may produce a weaker response to Havrix. Share the medication list and treatment schedule with the vaccination team. Do not stop prescribed treatment to improve a vaccine response without advice from the clinician managing it. [6]
When a vaccination needs extra review
A severe allergic reaction to a previous dose or a vaccine component is a contraindication that needs professional assessment. A sore arm or brief tiredness after an earlier injection is not the same history as anaphylaxis. Describe what happened, how quickly it started and what treatment was needed. The clinician can check the exact product ingredients rather than relying on a general label such as “vaccine allergy.” [15]
A mild cold usually does not require postponing vaccination. Moderate or severe acute illness can justify waiting until recovery, whether or not fever is present. If you are currently unwell, contact the service rather than cancelling automatically or hiding symptoms. The purpose is to make a safe decision and avoid confusing an existing illness with a reaction after vaccination. [15]
Other vaccines and the timing of immune globulin
Hepatitis A vaccine can be fitted into a broader vaccination plan, but immune globulin has separate timing considerations. It can affect measles-containing and varicella vaccines for months. Tell every vaccinating service about recent immune globulin or blood-product treatment, including the date and product. This matters particularly for infant travel plans and catch-up appointments. A clinician should decide whether a vaccine needs rescheduling or repeating; a general internet interval cannot safely replace that review. [18]
Expected reactions and symptoms that need help
After hepatitis A vaccination, soreness or redness around the injection, a temperature, headache, tiredness or reduced appetite can occur. Some people faint around injections, so tell staff if you have fainted before or start feeling light-headed. Stay seated or follow the team’s observation advice instead of trying to walk out while dizzy. [16]
A severe allergic reaction is rare but needs emergency care. Call your local emergency number for breathing difficulty, swelling involving the face or throat, or widespread hives accompanied by weakness, dizziness or a rapid heartbeat after vaccination. In the United States, call 911. Do not wait for an online response or complete a reporting form before getting help. [16]
Most common hepatitis A vaccine reactions are mild and settle within a day or two. A tender injection site can feel warm or have a small firm area. CDC’s safety review describes a favorable safety profile based on clinical studies and monitoring after vaccination. That is reassuring evidence, while still allowing an individual’s unusual or worsening symptoms to be taken seriously. [17]
Ask the clinic what to expect for your age and product, and whom to contact if symptoms persist or concern you. Do not assume that every new symptom is caused by vaccination, but do not dismiss it solely because a vaccine was recently given. Assessment depends on the symptoms, their timing and the person’s health. If you feel significantly unwell, seek medical advice rather than relying on the usual short duration of mild reactions. [17]
In the United States, patients and caregivers can report possible problems after vaccination to VAERS, alongside reports from clinicians and manufacturers. You do not have to prove that the vaccine caused an event before reporting it. The system is designed to detect patterns that may deserve closer investigation. Include accurate timing and available vaccine details, and seek clinical care separately when needed. [30]
A report in VAERS is not, by itself, a confirmed vaccine injury or a measure of how often a vaccine causes a condition. Reports can describe events that happened afterward for unrelated reasons. Interpreting safety requires further investigation and other evidence. This distinction helps you take a personal concern seriously without treating an unverified online tally as an individual risk prediction. [30]
Find your vaccination history before the appointment
Start with previous medical practices, travel clinics, pharmacies and your personal health records. Childhood records may be held by a parent or caregiver; school, university, military or employer records can sometimes help. In the United States, state immunization registries may contain useful entries. CDC itself does not hold a national personal vaccination record. Keep copies of what you find rather than relying on a single clinic portal. [24]
Bring the record to the appointment and ask the provider to add the new vaccination accurately. Keep dates, product information and the next planned visit together. If records cannot be found, tell the clinician honestly; do not invent dates or assume that a remembered travel injection was hepatitis A. A healthcare professional can decide how to establish protection when the history is uncertain. [24]
Do you need a blood test before or after vaccination?
Routine testing before hepatitis A vaccination is usually unnecessary. In selected situations, checking immunity may avoid an unnecessary course, for example when prior infection is plausible and cost is a concern. A blood test used to investigate current illness serves a different purpose from a test used to assess past immunity. Ask what question the test is intended to answer before interpreting a result yourself. [23]
IgG antibodies can reflect immunity from past infection or vaccination. IgM testing is used when a clinician suspects recent hepatitis A, particularly with symptoms; results still need interpretation in context. Symptoms alone cannot reliably distinguish hepatitis A from other causes of hepatitis. Do not arrange a broad antibody test as a substitute for urgent exposure advice or use a positive result to diagnose yourself. [23]
Make the visit easier for a child
Read the vaccine information sheet beforehand and write down your questions. Bring the immunization record and a familiar toy, book or blanket. Explain the appointment honestly in age-appropriate language without using injections as a threat. A calm caregiver, comfortable positioning and distraction can help. Ask staff how you can support the child during the injection instead of holding them in a way that interferes with safe administration. [25]
Afterward, follow the clinic’s comfort advice. A cool damp cloth may ease local soreness, and offering fluids can help when a child is a little unsettled. Ask a clinician about suitable pain relief rather than giving an adult medicine or guessing a dose. Keep the information sheet and contact details somewhere accessible. Before leaving, confirm what reactions are expected and when the next appointment is due. [25]
Cost and access: check the whole appointment
In the United States, the Vaccines for Children program can supply vaccines without a vaccine charge for eligible children through enrolled providers. Eligibility includes children aged 18 or younger who are uninsured, Medicaid-eligible, American Indian or Alaska Native, or underinsured. Underinsured children generally need an eligible health-center or rural-clinic route. Ask the practice whether it participates and explain your current insurance situation. [26]
There may still be administration or other visit-related fees. A participating provider cannot refuse the child’s vaccination because the family cannot pay the administration charge. Ask which charges apply before attending, especially if the visit includes unrelated tests or care. A local health department can help identify an enrolled provider. [26]
Many United States health plans cover recommended preventive immunizations, including hepatitis A, without cost sharing when the service meets the plan’s requirements. HealthCare.gov specifically cautions that coverage varies and a zero-cost visit is not guaranteed in every circumstance. Check that the clinic or pharmacy is in network and that the proposed vaccination is covered for you. [27]
When asking about price, distinguish the vaccine, the injection service and any consultation fee. Request the expected cost of the full course, not just the first visit. Keep the insurer’s answer and appointment information together. If you are paying privately or receiving travel care outside your usual network, ask for the total before the appointment so an unexpected bill does not interrupt completion. [27]
Everyday prevention still matters after vaccination
Wash with soap under running water after using the toilet and following diaper changes. Also wash before meals and food preparation. Work up a lather across the backs of the hands, between fingers and around the nails. Scrub for at least 20 seconds, rinse, then use an air dryer or a clean towel. A quick splash of water misses much of the point. [29]
Build handwashing into the places where it is easiest to forget: preparing a child’s snack, returning from a public bathroom or moving from caregiving to cooking. Keep soap available and help younger children reach the sink safely. See our guide to hand hygiene and everyday infection-control precautions. These habits complement vaccination and remain useful for reducing many everyday infections. [29]
When traveling where food or water safety is uncertain, choose food that has been thoroughly cooked and served hot. Avoid raw seafood and food sitting lukewarm for long periods. Fruit you peel yourself is generally a safer choice than a prepared salad or cut fruit handled by someone else. A well-presented buffet does not tell you how ingredients were washed or stored. [28]
Use reliably safe water for drinking and brushing teeth when local tap water may be contaminated. Check seals on bottled drinks and avoid ice of uncertain origin. Consider the water used in drinks, sauces and infant feeding, not only the water served in a glass. Vaccination cannot prevent every illness carried by contaminated food or water, so these precautions remain relevant throughout the trip. [28]
Symptoms after travel or exposure deserve assessment
Possible hepatitis A symptoms include unusual tiredness, poor appetite, nausea, vomiting, abdominal discomfort, diarrhea, dark urine and pale stools. Some people develop yellowing of the eyes or skin. Symptoms can appear roughly two to seven weeks after infection, so mention travel or contact from earlier weeks when seeking care. An apparently unrelated trip may still help the clinician understand the illness. [31]
Do not wait for jaundice to report a known exposure. Preventive treatment has a shorter window than the time it can take symptoms to appear. If illness develops, explain the vaccination dates as well as the exposure. A recent vaccine appointment does not establish the cause of symptoms or remove the need for clinical assessment. [31]
New yellowing of the eyes or skin needs urgent medical assessment because jaundice can have serious causes. It is not specific to hepatitis A. Yellow skin may be harder to notice on darker skin tones, while yellowing of the whites of the eyes can be more apparent. In the United Kingdom, seek an urgent GP appointment or NHS 111 advice; elsewhere, use the corresponding local urgent-care service. [32]
Public-health notices and household planning
Hepatitis A outbreaks can develop through personal contact or a common contaminated food source. A notice about a restaurant or recalled product does not automatically mean everyone nearby was exposed. Read the named product, location and relevant dates carefully, and follow the public-health instructions applying to that event. If you are unsure whether you fit the exposure criteria, contact the listed service promptly rather than waiting for a general news update. [33]
Keep any relevant receipt, product details and vaccination history available for that conversation. Public-health teams may organize vaccination for people at risk during an outbreak. The priority is to identify the people who need timely protection, while following the specific investigation rather than circulating assumptions about a business or individual. Local advice can change as investigators establish which exposures matter. [33]
Frequently asked questions
Can hepatitis A vaccination give me hepatitis A?
The inactivated hepatitis A vaccines described in UK guidance do not contain live organisms capable of causing hepatitis A. Having symptoms after vaccination still deserves an assessment when they are concerning; the timing alone does not identify the cause. [20]
Must I restart if my second injection is years late?
Usually not. An interrupted hepatitis A course can generally be completed without restarting. Have a clinician verify the earlier product, date and validity, then arrange the remaining dose or doses. [9]
Do healthy people need an antibody test after a routine course?
Not routinely. Testing may matter when later care depends on the result, particularly for some people with impaired immunity. Ask your clinician whether that exception applies. [9]
Can I wait for symptoms after a known exposure?
No. Contact a clinician promptly because preventive treatment is considered within two weeks of exposure, while symptoms may take much longer to appear. [31]
What should I do if I actually have hepatitis A?
Follow medical and local public-health advice. NHS guidance recommends rest, fluids, avoiding alcohol and not preparing food for others while infected. Ask about safe medicines and when work, school or close contact can resume. A vaccine is not a treatment for the illness. [19]
Why do countries recommend different vaccination programs?
Disease patterns and existing immunity differ. WHO advises countries to consider local hepatitis A epidemiology and cost-effectiveness. Use the schedule for the country providing your care, with travel-specific advice where relevant. [22]
The preserved video below has not been reviewed for current vaccination schedules. Use the official references that follow for current guidance.





