

General education, not a personal diagnosis or treatment plan. Information checked on 12 October 2026. Work with a clinician who knows your kidney function, medicines and other health conditions.
Understanding autosomal dominant polycystic kidney disease
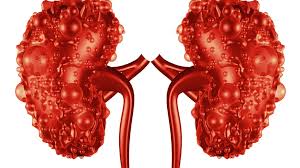
Autosomal Dominant Polycystic Kidney Disease (ADPKD) is a genetic condition in which many fluid-filled sacs, called cysts, develop in the kidneys. Over time, these cysts can enlarge the kidneys and interfere with their work. ADPKD is one cause of chronic kidney disease, but its effects extend beyond a scan showing cysts. Blood pressure, kidney function and problems in other organs can all matter. A few simple kidney cysts, which become more common with age, are a different finding and do not automatically mean someone has ADPKD. [1]
A useful way to approach a new diagnosis is to separate three questions: What confirms the diagnosis? What does it mean for your health now? What should be monitored or treated next? Write down the answers in your own words. You do not need to settle every long-term decision at the first appointment. Start with a clear explanation of your results, a named clinician to contact and a date for follow-up.
What inheritance means for you and your family
ADPKD most often involves a disease-causing change in PKD1 or PKD2, genes involved in proteins important to kidney cells. Signs often become noticeable in adulthood, but cysts can be present in childhood. The label “adult polycystic kidney disease” therefore does not mean children cannot be affected. PKD2-related disease tends to progress later than PKD1-related disease, but there is considerable variation. A gene name gives useful context; it cannot, by itself, tell a person exactly how they will feel or when their kidneys might need extra support. [2]
When one parent has the usual autosomal dominant form, each child has a 50% chance of inheriting the disease-causing variant. That probability applies separately to each pregnancy. It does not mean exactly half the children in a family will inherit it, and it does not predict the severity of an affected child’s illness. ADPKD can also appear without a known family history. A relative may never have been diagnosed, or a new, or de novo, genetic change may have arisen. A person with a new disease-causing variant can still pass it to their children. [3]
What a genetic counselor can help you decide
Genetic counseling is a conversation about information and choices. A genetics professional can review your family history, explain what testing could answer, discuss possible results and help you consider implications for relatives or future children. Bring any available relatives’ diagnostic letters or genetic reports rather than relying only on a remembered diagnosis. You can ask what a test would change in your care, who would receive the result and whether testing another affected relative first would be informative. Counseling should support your decision rather than pressure you toward one particular choice. [4]
For a family discussion, consider separating practical information from predictions. You might share the confirmed diagnosis, where your relative can seek advice and whether a genetic report is available. Avoid telling someone they definitely have the condition simply because they are related to you. Ask the clinic whether it can provide a family letter that explains the next steps in plain language. Relatives may want different amounts of information or different timing for these conversations.
How ADPKD is diagnosed
Diagnosis brings together imaging, age, symptoms and family history. An ultrasound is commonly used to look for cysts; MRI or CT may be needed for a more detailed assessment. Blood and urine tests help evaluate how the kidneys are functioning and look for related problems. In selected circumstances, genetic testing can clarify the diagnosis. There is no single cyst count that readers should use to diagnose themselves: a specialist must interpret what the scan shows in the context of the person being tested. [5,6]
A normal scan in a young person does not always exclude ADPKD because small cysts may not yet be visible. Genetic testing also has limitations and can sometimes be negative even when the clinical picture suggests the condition. Ask what a negative or uncertain result means at your age, whether later reassessment is needed and what would trigger another test. Screening an at-risk child deserves a discussion with the child’s clinician about benefits, limitations and the family’s preferences rather than an automatic adult testing plan. [5]
What scans can and cannot tell you
MRI can measure total kidney volume, which describes the combined size of the kidneys and helps characterize the disease. Imaging is useful alongside kidney-function tests because it describes structure rather than simply blood filtration. Your clinician may use it when considering how quickly the disease is progressing and whether treatment is appropriate. Ask why a scan is being ordered and how its result will change the plan. More imaging is not automatically more helpful if it will not answer a clinical question. [7]
Keep the radiology report and, if practical, ask how to obtain the actual images when changing clinics. Record the date and type of scan and which hospital performed it. If a new clinician recommends repeating a recent study, ask whether the earlier images can be reviewed first. This is a practical way to make appointments more useful without trying to interpret the pictures yourself or assuming that a comparison between two reports tells the whole story.
Symptoms, infections and blood in the urine
Some people have no obvious symptoms when ADPKD is found. Others experience aching in the back or sides, abdominal discomfort, headaches or blood in the urine. Pain can arise from growing cysts, bleeding into a cyst, infection or kidney stones. Its cause matters because treatments differ. New pain should not simply be written off as part of a familiar diagnosis. Tell your clinician where it hurts, when it started and whether it comes with fever, urinary symptoms or visible bleeding. [6]
When an infection needs prompt care
Fever or chills with pain in the back, side or groin, painful or frequent urination, nausea or vomiting may indicate a kidney infection. Seek medical care right away rather than waiting for your next planned review. Cloudy, bloody or foul-smelling urine can also occur, although appearance alone does not establish the cause. An infection can become serious even when the first symptoms resemble a bladder infection. Confusion, rapid breathing, severe illness or shortness of breath can be signs of sepsis and require emergency assessment. [16]
When calling for help, say that you have ADPKD and describe any previous kidney or cyst infections. Have your medicine list and allergy information available if you can. State whether you can keep fluids down and whether symptoms are getting worse. If you were already given treatment, report persistent fever or worsening pain rather than assuming that completing the original plan is the only next step. The person assessing you needs that change in the story.
Why visible bleeding should be checked
Blood can make urine look pink, red or brown; sometimes it is detectable only through a urine test. A small amount can noticeably change the color, so appearance does not reliably measure the amount of bleeding. Clots may cause pain or block urine flow. Although cyst bleeding is a familiar concern in ADPKD, hematuria has other causes, including infection, stones and unrelated urinary-tract conditions. Evaluation may involve urine tests, blood tests or imaging. Do not assume every episode has the same explanation as the last one. [17]
Get prompt advice for new visible blood in the urine, and seek urgent assessment for inability to pass urine, significant clots or severe pain. Tell the clinician about blood thinners, recent injuries and urinary procedures. The purpose of assessment is to identify the cause and decide what care is needed, not just to wait for the color to clear. Avoid treating visible bleeding with an unsupervised high-fluid regimen when you already have a prescribed fluid limit. [17]
Following kidney health over time
A blood test measuring creatinine is commonly used to estimate glomerular filtration rate, or eGFR. This estimates how well the kidneys filter blood. Urine testing can measure albumin, a protein that may leak into urine when kidneys are damaged. The urine albumin-to-creatinine ratio, often shortened to UACR, is one way to quantify it. These tests answer different questions, so one result does not replace the other. Ask your team to explain the units on your laboratory report and which results it is following in your case. [8]
Follow-up is more informative when results can be compared over time. Ask whether your eGFR and urine albumin have changed, what the team thinks the trend means and whether the monitoring schedule should change. A record with dates and results is useful when several clinicians are involved. Include medication changes and significant illnesses so they can interpret the results with the surrounding history. Do not make treatment changes from a single number without discussing what it means in context. [9]
The course of PKD varies even among relatives. Some people develop advanced kidney disease, while others have much milder disease. A clinician can explain what your imaging, current kidney function and pattern of change suggest, but an estimate is not a precise countdown. Ask for the uncertainty to be explained as well as the risk. Learning whether your situation appears stable or faster-moving is more useful than comparing your future with the age at which one relative started dialysis. [7]
| Record | Useful details to write down |
|---|---|
| Test results | Keep the date, test name, result and the clinician’s explanation together. If you do not know what a result means, leave space for the answer rather than assigning it a meaning from an online chart. |
| Symptoms | Describe the start date, location, duration and effect on daily activities. Note which symptoms are new and which were discussed at a previous visit. |
| Follow-up plan | Write down who orders the next tests, when they are due, how results will reach you and whom to contact if you have not received them. |
Blood pressure is a central part of kidney protection
High blood pressure can worsen kidney damage, and kidney disease can make blood pressure harder to control. Treatment commonly combines lifestyle measures with medicines. ACE inhibitors and angiotensin receptor blockers, or ARBs, are often used in kidney care. The right medicine and blood-pressure goal depend on your circumstances. Ask for a written target and an explanation of whether it applies to carefully measured clinic readings or readings at home. Do not adopt another person’s target or adjust tablets because one measurement looks better. [10]
Reducing sodium, staying active, avoiding smoking and taking prescribed treatment can support blood-pressure control. If a medicine causes symptoms or is difficult to afford, tell the team so the plan can be reviewed. For additional background, see our guide to blood pressure treatment and follow-up. Your kidney clinician should still set the target appropriate to your ADPKD and review whether your current treatment is achieving it safely. General hypertension information is a starting point for that conversation. [10]
Make home readings useful
The American Heart Association recommends a validated automatic upper-arm monitor with the correct cuff size. Rest quietly for at least five minutes before measuring, and avoid smoking, caffeine and exercise during the preceding 30 minutes. Empty your bladder, place the cuff on bare skin and support your arm at heart level. Do not talk during the measurement. Take two readings one minute apart and record them. Ask your clinician when and how often to measure, and bring the device to an appointment to check your technique. [11]
Keep your log straightforward: date, time, the two readings and any symptoms you want the clinician to know about. If checking repeatedly makes you anxious, discuss a manageable schedule rather than measuring every few minutes. Ask in advance which readings should prompt a call and what to do outside office hours. A home monitor is most helpful when it connects to a clear plan for interpretation and follow-up. [11]
Food and fluids: personalize the plan
A kidney dietitian can help you choose meals that fit your blood pressure, kidney function, laboratory results and food preferences. Reducing sodium is commonly part of the plan. Protein needs also deserve individual advice rather than a high-protein or severely restricted diet copied from the internet. Potassium and phosphorus restrictions are not automatically needed by everyone with ADPKD; they may become relevant as kidney disease advances or blood levels change. Ask which changes matter now and which do not apply to your current results. [12]
Make dietary advice concrete. Bring examples of usual breakfasts, lunches, snacks and restaurant meals, and ask for realistic substitutions. If you cook for a household, discuss a shared meal with any individual adjustments rather than assuming you need a completely separate menu. Tell the dietitian about appetite problems, food costs and cultural or religious preferences. A plan that accounts for ordinary life is easier to understand and discuss than a long list of foods labeled simply good or bad. [12]
To clarify your instructions, ask whether the target covers water alone or all drinks, whether foods with substantial liquid count, and what should change during hot weather, travel or illness. Write the answers beside your medication plan. If advice from two clinicians seems inconsistent, ask them to reconcile it before deciding that the larger or smaller number must be correct. These are useful questions to resolve before buying large bottles or setting automatic drinking reminders.
Pain care and safer medicine use
Managing pain begins with finding its cause. An infection, a stone and pressure from a large cyst may need different treatment. Persistent cyst-related pain sometimes leads to specialist procedures, but draining a cyst is not a cure for the underlying genetic disease. Your clinician may discuss paracetamol, also called acetaminophen, or other options depending on the cause and your health. Ask which product, dose and duration are appropriate rather than assuming an over-the-counter medicine is harmless or suitable for long-term use. [15]
Kidney or cyst infections may need a different approach from a straightforward bladder infection because antibiotics do not all reach cyst fluid equally well. Persistent symptoms can require further assessment, different treatment or, occasionally, drainage. Stones that do not pass may also require a procedure. Keep follow-up arrangements clear after an acute episode: ask who checks that the problem has resolved and what symptoms should bring you back sooner. Do not use leftover antibiotics or someone else’s prescription to manage a recurrence. [15]
Nonsteroidal anti-inflammatory drugs, or NSAIDs, include ibuprofen and naproxen and may be present in combination cold or pain products. They can harm kidney function, particularly during dehydration or in people with kidney disease. Check with your clinician or pharmacist before using them. Bring prescription medicines, nonprescription products, vitamins and supplements into the same medication review so interactions and kidney-related precautions can be considered together. A product described as natural does not remove the need for that review. [14]
Ask for a written sick-day plan covering vomiting, diarrhea, fever or difficulty drinking. It should say which medicines require a temporary change, whom to call and when to restart any paused medicine. Do not create your own list of medicines to stop during every illness. Different drugs have different instructions, and the specific tolvaptan safety actions below are particularly important. Keep the plan somewhere accessible when you are unwell, and review it when prescriptions change. [14]
Tolvaptan: an option for selected people
Tolvaptan blocks the action of vasopressin at a receptor in the kidneys. It can slow cyst-related kidney enlargement and kidney-function decline in suitable adults with rapidly progressing ADPKD. It does not remove the inherited condition or promise that kidney failure will never occur. The European Medicines Agency’s assessment of Jinarc describes benefit together with important restrictions and monitoring. Deciding whether to use it means weighing the likely benefit against the treatment burden and risks with a clinician experienced in ADPKD. [21]
KDIGO recommends considering initiation in adults at risk of rapid progression with eGFR at least 25 mL/min/1.73 m². Eligibility requires specialist assessment, including whether decline has another cause; having cysts alone is insufficient. [13]
The medicine commonly causes thirst, more urine and waking at night to urinate. Discuss how reliable access to water and toilets would fit your work, sleep, travel and caring responsibilities. Treatment is prescribed and supervised, with the dose adjusted to what is appropriate and tolerable. Regulatory approval, clinical guidance and local access arrangements are separate issues. The brand name and prescribing pathway in one country should not be assumed to apply everywhere. Ask your local team which product and requirements apply to you. [21]
Liver monitoring and stopping rules matter
The September 2026 U.S. Jynarque label warns of serious, potentially fatal liver injury. It requires blood tests for ALT, AST and bilirubin before treatment, at two and four weeks, monthly for the first 18 months and every three months afterward. In the United States, access is through the Tolvaptan for ADPKD Shared System REMS. Monitoring reduces risk but does not eliminate it. [20]
While taking Jynarque, stop the medicine and contact your healthcare provider right away if you develop possible liver-injury symptoms such as unusual fatigue, poor appetite, right-upper abdominal pain, dark urine or yellow skin or eyes. Also stop and call if you cannot drink enough water, cannot access water or develop dehydration symptoms, including marked dizziness or faintness. Follow the current Medication Guide and your prescriber’s instructions. Do not wait for the next scheduled blood test. [20]
Before starting, have the prescriber check liver disease, sodium abnormalities, hydration, urine-flow problems and interacting medicines. Uncomplicated liver cysts are different from significant liver impairment. The U.S. label warns of possible fetal harm and advises against breastfeeding during treatment. Discuss pregnancy plans with the prescriber before starting or continuing treatment. [20]
Ask the pharmacist to explain exactly how your prescribed doses fit into the day and what to do if you miss one. Do not double a dose to catch up. Grapefruit and grapefruit juice should be avoided with the ADPKD product described in U.S. patient information. Tell the prescriber about every other medicine and supplement. Tolvaptan is also used for a different condition, low blood sodium; instructions for that use are not interchangeable with an ADPKD treatment plan. [22]
Before a refill, review whether you can complete the required tests and whether any new medicine has been prescribed elsewhere. Contact the team early if cost, travel or working hours are making treatment difficult. Ask whom to contact after hours and which symptoms require immediate help. Keep the manufacturer’s patient information with your treatment records so you can check the specific instructions for your product rather than relying on an old video or a discussion about somebody else’s prescription. [22]
Liver cysts and brain aneurysm screening
Liver cysts are common in ADPKD and usually do not prevent the liver from doing its usual work. However, some people develop abdominal swelling, discomfort or other symptoms, and a cyst can become infected. Persistent or severe problems deserve specialist assessment; procedures may be appropriate for selected people. A finding of liver cysts should therefore prompt a discussion of symptoms and function rather than an assumption that liver failure is inevitable. New jaundice or significant illness needs medical evaluation, especially if you take a medicine with liver-related risks. [18]
ADPKD is associated with a higher chance of an intracranial aneurysm, a bulge in a blood vessel in the brain. An aneurysm is not the same as a rupture: many cause no symptoms. Cardiovascular risk also deserves attention because high blood pressure contributes to problems affecting the heart and circulation. These associations help explain why ADPKD appointments may include questions that extend beyond the kidneys themselves. [18]
Screening is a shared, risk-based decision
KDIGO recommends aneurysm screening for treatment-eligible people with reasonable life expectancy who have previous subarachnoid hemorrhage or a family history of brain aneurysm, that bleeding or unexplained sudden death. Discuss screening with unknown family history or de novo ADPKD, and around selected major surgery or pregnancy planning. Informed preference can also justify screening. Ask about benefits, incidental findings, possible follow-up and how a result would change care. [13]
Finding an aneurysm does not automatically mean an operation. Small aneurysms may be followed with scans, while others need specialist discussion about a procedure. The team considers the features of the aneurysm and the person’s overall circumstances. Ask who is responsible for follow-up and what the next scan is intended to establish. Screening is a planned assessment for someone without an emergency; it does not replace immediate care for the sudden severe headache or neurologic symptoms described earlier. [19]
Pregnancy, family planning and genetic information
Many people with mild kidney disease can have a healthy pregnancy, but risk depends on kidney function, blood pressure, urine protein and other health conditions. Moderate or advanced kidney disease can make pregnancy more complicated. Arrange a pre-pregnancy review with your kidney team and an obstetric clinician who can assess your situation. Ask about monitoring, which medicines need review and when any changes should be made. Do not assume a relative’s pregnancy experience establishes your own level of risk. [23]
If you are already pregnant, contact your healthcare team promptly to review the plan. Include all medicines, including treatment from a transplant team or another specialist. Some medicines used in kidney care are unsuitable in pregnancy, and replacing them safely requires coordination. Family planning also includes contraception and fertility questions, not only planning a pregnancy. Ask for advice that takes account of your blood pressure and other conditions rather than choosing a method solely from general information online. [23]
For people who want to reduce the chance of passing on a known inherited condition, one option to discuss is IVF with pre-implantation genetic testing for monogenic disorders, or PGT-M. Embryos are tested for a specific genetic condition before an embryo is selected for transfer. This requires IVF even if there is no fertility problem. Testing is not perfectly accurate, and a treatment cycle may produce no suitable embryo or may not lead to a baby. [24]
PGT-M is a choice, not an obligation. Ask a genetics and fertility team about the relevant variant, available alternatives, cost, time and uncertainty. The UK HFEA regulates which conditions can be tested in licensed treatment; access and rules elsewhere differ. People may make different decisions about testing, pregnancy or becoming parents. The purpose of counseling is to explain the options clearly enough for a decision that fits the person’s values and circumstances. [24]
Privacy and insurance questions depend on where you live
A genetic result can matter to relatives as well as to the person tested. Before testing, ask how information is stored, who receives it and what consent choices exist. Legal protections vary by country and type of insurance. For example, the U.S. Genetic Information Nondiscrimination Act provides certain health-insurance and employment protections, but it does not cover life, disability or long-term-care insurance. That example is not a universal legal guarantee. A genetics service can help identify questions to take to a qualified local adviser before you decide. [25]
Activity, emotional health and everyday life
Regular activity can help people with kidney disease maintain strength, endurance and independence. It can also support blood-pressure control, sleep and well-being. The right starting point depends on current fitness, symptoms and other health problems. Ask which forms of aerobic, strengthening and flexibility exercise are appropriate, then build up gradually. A manageable routine can be more practical than a sudden demanding program. Stop exercising and seek medical advice for exercise-related dizziness, unusual breathlessness, chest discomfort or other concerning symptoms rather than pushing through them. [31]
In ADPKD, a blow to the back or sides can injure cystic kidneys and cause bleeding. Discuss collision sports and activities with a substantial risk of abdominal impact with your kidney clinician. The goal is an individualized activity plan that considers your kidneys and the activity itself, rather than assuming every form of exercise has the same risk. [1]
Living with a long-term condition can bring anxiety, sadness and uncertainty. Persistent low mood, loss of interest, sleep changes or difficulty functioning deserve attention, just as physical symptoms do. Depression is treatable, including in people with chronic illness. A primary-care clinician can help assess what is happening and arrange mental-health support. Counseling, medication or both may be appropriate; any medication should be reviewed alongside your existing treatment. You do not need to wait until distress becomes overwhelming before mentioning it. [30]
It may help to name the specific difficulty at your next visit: fear about a relative’s experience, disruption from symptoms, concerns about children or the burden of repeated appointments. Ask for the kind of support you need, whether that is a fuller explanation, a social-work discussion or mental-health care. If you bring someone to an appointment, tell them beforehand whether you want note-taking, help remembering questions or simply company. You remain the person whose priorities guide the conversation.
If kidney disease becomes advanced
Planning for possible kidney failure does not mean treatment must start immediately. Early discussion gives you time to understand choices, ask questions and prepare. Starting dialysis is a clinical decision that considers symptoms and the overall situation, not simply a date on the calendar. Options include dialysis, transplantation and, for some people, comprehensive conservative care. Ask your team which options are medically suitable and what each would involve for your daily life, support needs and goals. [26]
Hemodialysis and peritoneal dialysis
Hemodialysis circulates blood through a filter outside the body to remove waste and excess fluid. Treatment may take place in a dialysis center or at home, depending on the service and the person’s circumstances. A reliable connection to the bloodstream, called vascular access, is needed. Creating and preparing that access can take time, which is one reason the team may discuss it while you still feel relatively well. Ask how the proposed access and treatment schedule fit your situation. [27]
Home hemodialysis involves training, equipment and a plan for safety and support. Center-based treatment has its own travel and scheduling demands. Compare the practical details before deciding that one setting must be easier: ask about training time, storage, help from another person, work arrangements and contact outside normal hours. Availability differs between services. The dialysis team can explain which choices are realistic locally and how a plan could be reviewed if your needs change. [27]
Peritoneal dialysis uses the lining of the abdomen to help filter waste and excess fluid. Dialysis solution enters through a catheter, remains for a prescribed period and is then drained and replaced. Exchanges may be performed during the day or with a machine overnight. Training covers handling the catheter and supplies and reducing infection risk. This treatment has different practical requirements from hemodialysis, so ask for a direct discussion of whether it is suitable for you. [28]
People using peritoneal dialysis need clear instructions for possible infection. Abdominal pain, fever or cloudy used dialysis fluid can be warning signs requiring immediate contact with the dialysis service. Storage space, a clean place for exchanges and the ability to follow the prescribed schedule are also part of planning. Ask the team to explain the daily routine, backup arrangements and what happens when you travel or become unwell. These details can strongly influence how a treatment fits ordinary life. [28]
Transplantation and conservative care
A kidney transplant places a donor kidney into the body to take over filtration. It may offer important benefits for a suitable person, but requires an assessment, surgery and continuing care. A donor may be living or deceased, and both the recipient and any potential living donor need careful evaluation. After transplantation, anti-rejection medicines and regular monitoring remain necessary. Ask when referral is appropriate, what the assessment involves and how the team handles potential donors who are relatives. [29]
A related potential donor needs careful evaluation to exclude ADPKD. Feeling well or having reassuring kidney-function blood tests alone does not establish that donation is safe. [13]
Transplantation is not the end of all medical treatment. Anti-rejection medicines can increase infection risk and have other side effects, so follow-up includes medicine review and testing. Do not skip or change them without instructions from the transplant team. If you are considering a transplant, discuss the balance of benefits and risks, support after surgery, medication access and ongoing appointments. A clear picture of continuing care helps you compare the option realistically rather than imagining either a guaranteed cure or an unmanageable burden. [29]
Comprehensive conservative management is active care without dialysis or transplantation. It focuses on symptoms, comfort and quality of life while addressing the person’s remaining kidney function and other health problems. It may be an appropriate option for some people after a careful discussion of likely benefits and burdens of treatment. Choosing it should include a clear support plan and opportunities to revisit decisions. It should never be presented as simply abandoning someone because their kidneys have become very unwell. [26]
Leave your next appointment with a workable plan
Your care may involve a kidney specialist, primary-care clinician, nurse, pharmacist and dietitian, with other professionals when needed. Clarify which person handles each part of the plan. Prepare questions about test trends, medicines, diet and symptoms, and bring an updated medicine list. A trusted person can help take notes if you want that support. The useful outcome is a plan you understand well enough to follow and a clear route to help if something changes. [9]
Before leaving, try summarizing the plan aloud: “My next tests are due on this date, this person will contact me about the results, and these symptoms mean I should seek help sooner.” Ask the team to correct anything you have misunderstood. Put the next appointment and any required laboratory visits in a calendar. If a recommendation is difficult to follow, say why while there is still time to adapt it. Practical barriers are part of the care discussion.
Choose a small number of unanswered questions for the next visit. You might ask what confirms your diagnosis, whether your results suggest faster progression, which blood-pressure goal applies, whether tolvaptan merits discussion, and whether your personal or family history warrants aneurysm screening. Ask about genetic counseling or pregnancy planning when those topics are relevant. Keep the answers with your records so future appointments build on earlier decisions rather than starting again from memory.
Video note: The older embedded video is retained from the original article. It has not been independently medically reviewed. Recommendations may have changed; use the current cited guidance and your clinician’s advice for treatment decisions.





