
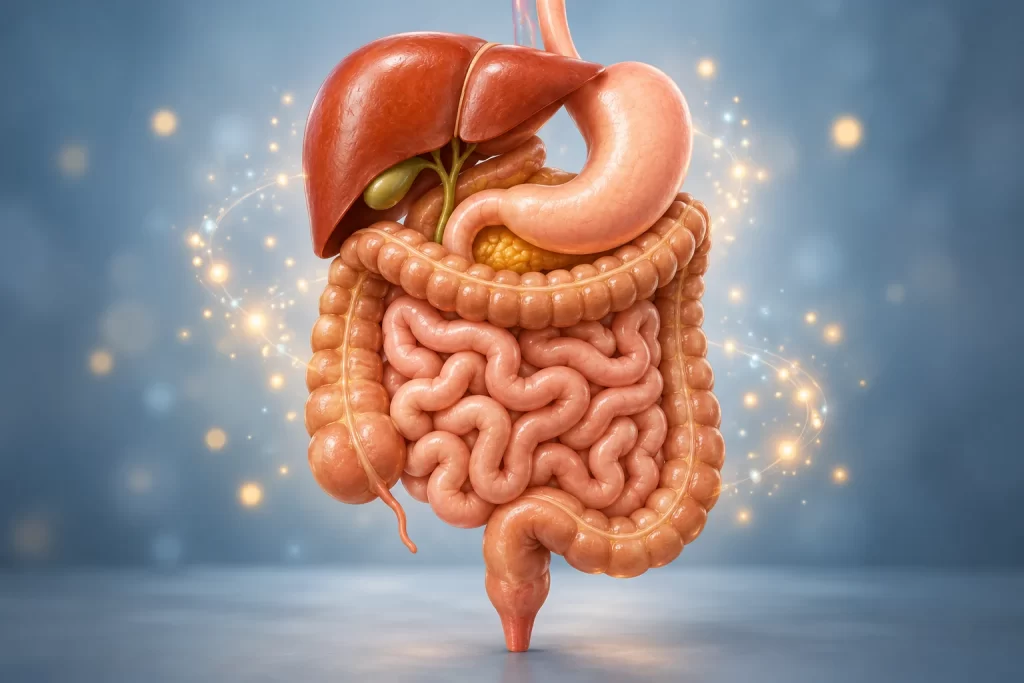
What is carcinoid syndrome?
Carcinoid syndrome is a collection of symptoms caused by substances released by certain neuroendocrine tumors, or NETs. The tumor is the underlying disease; the syndrome is the effect its secretions have elsewhere in the body. A person can have a NET without having carcinoid syndrome. Conversely, symptoms such as flushing and diarrhea need investigation before they can be attributed to a tumor.
Care has two related goals: controlling hormone-related symptoms and treating the tumor itself. A treatment may help one goal more than the other, so improvement in diarrhea does not prove that a tumor has disappeared. Surgery can be potentially curative when all relevant disease can be removed, but that is not possible for every patient. For more extensive disease, treatment may focus on slowing growth and improving daily life. The best plan depends on the tumor’s location, spread, biological features, and the person’s overall health. This guide explains the syndrome, its important complications, and the decisions commonly discussed with a specialist team.
Evidence: [1]
Why a neuroendocrine tumor can cause body-wide symptoms
NET cells can release serotonin and other biologically active substances. Normally, the liver breaks down much of what arrives from the digestive tract before it reaches the wider circulation. This helps explain why a small intestinal NET may be present without the characteristic syndrome. When tumor deposits in the liver release their products directly into the circulation, that protective processing can be bypassed.
Carcinoid syndrome therefore often accompanies a small intestinal NET that has spread to the liver. However, liver metastases are not an absolute requirement. Tumors in other locations can release substances into blood that does not first pass through the liver. The relationship between tumor site, blood drainage, and secretion matters more than a simple rule that the syndrome always means a particular stage.
Evaluation should establish both the biochemical evidence of abnormal secretion and the underlying tumor diagnosis. Hormone activity can also change over time. Someone whose NET was previously described as nonfunctioning may need reassessment if a new pattern of flushing or persistent watery diarrhea develops.
Evidence: [2]
Recognizing the symptom pattern
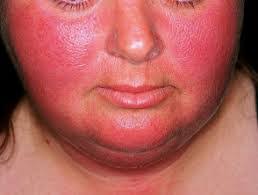
Flushing commonly affects the face, neck, and upper chest, with episodes of warmth and visible color change. Diarrhea may be frequent, watery, and disruptive. Some people also experience abdominal discomfort, wheezing, palpitations, or a rapid heartbeat. Longstanding flushing can leave small visible blood vessels in the skin. Symptoms do not have to occur together, and the intensity can vary between episodes.
Alcohol, particular foods, exertion, or emotional stress may provoke symptoms in some people, but episodes can also appear without an obvious trigger. A trigger diary is more useful than assuming every person has the same restrictions. The purpose is to identify a repeatable pattern that can be discussed with the care team.
Persistent diarrhea or recurrent unexplained flushing deserves a medical assessment, especially when accompanied by weight loss or breathing symptoms. These findings are clues, not a diagnosis. Many more common conditions can cause individual symptoms, and trying to identify carcinoid syndrome from appearance alone can lead to unnecessary alarm or missed alternative explanations.
Evidence: [3]
Diarrhea and abdominal pain need separate attention
Carcinoid-related diarrhea can continue overnight or when a person has not eaten. That pattern reflects hormone-driven changes in intestinal secretion and movement, rather than simply a reaction to the last meal. Fluid and electrolyte losses can become clinically important. Repeated bathroom trips may also make it difficult to eat, sleep, travel, or maintain normal activities.
Abdominal pain has several possible explanations in someone with a NET. It may accompany diarrhea, but it can also reflect the tumor itself, surrounding fibrous tissue, or bowel obstruction. Treating every episode of pain as another hormone symptom risks overlooking a mechanical problem. The timing, severity, location, and associated vomiting or change in bowel function help the team decide what to investigate.
New severe abdominal pain, persistent vomiting, or a swollen abdomen with inability to pass stool or gas needs urgent assessment. Those symptoms should not be managed merely by increasing an antidiarrheal medicine. Even a person who has lived with stable carcinoid syndrome for years can develop a separate acute abdominal condition.
Evidence: [4]
What else can cause flushing?
Flushing is a physical sign shared by many conditions. Menopausal hot flashes, medication effects, alcohol-related reactions, and ordinary emotional flushing are among the possibilities. Other endocrine or mast-cell disorders can also produce episodic redness, palpitations, or gastrointestinal symptoms. The presence or absence of sweating can help describe an episode, but it is not a reliable home diagnostic test.
A clinician asks whether the redness is episodic or persistent, which areas are involved, how long it lasts, and what happens at the same time. Itching, hives, headache, marked blood-pressure changes, or faintness can point toward a different investigation. A medication and supplement list matters because prescribed and nonprescribed products can alter vascular responses.
A photograph taken during a typical episode may help communicate a change that has disappeared by the appointment. It cannot establish the cause on its own. The useful clinical question is not whether a flush resembles an online image, but whether its full pattern and associated findings justify targeted testing.
Evidence: [5]
Testing serotonin activity: understanding 5-HIAA
One commonly used test measures 5-hydroxyindoleacetic acid, abbreviated 5-HIAA, a breakdown product of serotonin. A timed urine collection can estimate how much is excreted across the collection period. The result is interpreted alongside symptoms and other findings rather than used as a stand-alone cancer verdict. Small tumors and some tumor types may not produce a clearly abnormal result.
Preparation is important. Serotonin-rich foods and certain medicines can interfere with relevant biochemical measurements. The laboratory should provide instructions specific to the assay being ordered; a list copied from a different test may not be appropriate. The clinician also needs to know about supplements and medicines that affect serotonin pathways.
Do not independently stop an antidepressant or another prescribed medicine to prepare for testing. Ask the ordering team which changes, if any, are necessary and safe. An unexpected result may require review of diet, medicines, collection completeness, and the overall clinical picture before it leads to further scans or treatment decisions.
Evidence: [6]
Preparing for a urine collection
A urine test is only useful if the specimen represents the collection requested. Obtain the container and written instructions before starting, and clarify the start and finish times, storage conditions, and return arrangements. Ask what to do if a sample is missed. Reporting a collection problem is better than silently submitting a specimen that may be misleading.
Food restrictions for 5-HIAA are temporary testing requirements, not evidence that those foods caused a tumor. Different laboratories can specify different preparation periods and lists of interfering foods or drugs. Follow the instructions from the laboratory that will actually perform the analysis. If a required restriction is difficult because of poor appetite or a limited diet, discuss that before collection.
Keep a record of the collection dates and any relevant deviations. When reviewing a borderline result, the team may decide that repeating a properly prepared collection is more informative than immediately escalating to an invasive investigation. The choice depends on the result’s size, the symptoms, and other evidence, not merely whether a number is outside the printed range.
Evidence: [7]
Why chromogranin A is not a simple yes-or-no test
Chromogranin A is another marker that may appear in a NET workup. An important limitation is that proton-pump inhibitors, medicines commonly used for reflux and ulcer-related conditions, can raise its concentration. An elevated result while taking one of these medicines does not automatically mean a tumor has grown or that cancer is present.
A prospective study of patients with well-differentiated NETs found that some unexpectedly high measurements fell substantially after clinicians stopped or replaced proton-pump inhibitor treatment. This illustrates why the medication history belongs beside the laboratory result. It does not mean that every abnormal result is explained by a reflux medicine.
Any pause or substitution should be arranged by the treating clinician. The reason for taking the medicine may make an unsupervised change unsafe or uncomfortable. Ask whether the marker is useful for your particular tumor, what could distort it, and whether subsequent results will be measured under comparable conditions. A trend is easier to interpret when the circumstances of testing are documented consistently.
Evidence: [8]
Imaging locates disease and helps select treatment
Imaging answers questions that hormone tests cannot: where a tumor is located, whether it has spread, and whether it has features that make a particular treatment appropriate. Somatostatin-receptor PET uses a radioactive tracer designed to bind to receptors commonly found on NET cells. The resulting images show receptor-bearing tissue throughout the body.
A receptor scan is different from a blood or urine hormone measurement. A tumor can show receptor uptake without causing carcinoid syndrome. Conversely, the clinical team must interpret a scan in the context of the tumor type and other examinations rather than treating every bright area as proof of cancer.
Receptor imaging is particularly helpful for staging, finding an otherwise difficult-to-locate primary tumor, and considering receptor-targeted therapy. It complements anatomical imaging rather than replacing every other scan. Before an appointment, ask which clinical question the scan is intended to answer and whether any medicines need to be timed around it. Follow the imaging center’s preparation instructions instead of adjusting injections independently.
Evidence: [9]
The syndrome is not the same thing as the cancer stage
Staging describes the anatomical extent of a cancer. For gastrointestinal NETs, the TNM framework considers the main tumor, involvement of nearby lymph nodes, and spread to distant sites. The details differ according to where the tumor began. A stage label is therefore meaningful only when paired with the correct tumor type and site.
Carcinoid syndrome instead describes a hormone-related clinical problem. A person’s diarrhea frequency cannot be translated into a TNM stage. Similarly, a quiet symptom period does not prove that previously identified metastases have resolved. Imaging, pathology, and clinical assessment supply information that symptoms alone cannot provide.
When discussing results, ask the team to separate three questions: where the disease is, how its cells behave, and how actively it is producing symptoms. This avoids confusion when a report describes advanced disease but the person feels relatively well, or when symptoms are troublesome despite limited visible change on scans. Stage is important for planning, but it is not a complete forecast of an individual’s future.
Evidence: [10]
Carcinoid heart disease: why screening matters
Long-term exposure to tumor-related substances can damage heart valves, particularly the tricuspid and pulmonary valves on the right side of the heart. They may become thickened and less mobile, causing leakage or narrowing. This is called carcinoid heart disease. It can progress before a person recognizes obvious heart symptoms.
Echocardiography, an ultrasound examination of the heart, is central to detecting and assessing this complication. A blood marker called NT-proBNP can help identify people who need further cardiac evaluation, while serotonin-related measurements contribute additional risk information. Neither a normal exercise tolerance nor a single reassuring blood test should replace the surveillance plan agreed with the specialist team.
New breathlessness, reduced stamina, ankle swelling, or abdominal swelling should be reported. These symptoms have other possible causes, but they matter in someone with carcinoid syndrome. The frequency of repeat heart assessment depends on findings, hormone activity, and clinical changes. A universal screening timetable or a single threshold taken out of context is less useful than an individualized plan.
Evidence: [11]
What a cardiac assessment is looking for
A heart scan assesses more than whether a valve looks abnormal. It evaluates the direction and severity of blood flow, the size of the heart chambers, and how effectively the right ventricle works. These findings help distinguish early structural changes from disease that is placing a substantial burden on circulation.
Some structures are harder to see on a standard echocardiogram. Additional imaging may be considered when the initial study does not adequately answer the clinical question. Repeated examinations are also valuable because a change over time can be more important than a single isolated measurement.
If valve surgery is discussed, the cardiac and NET teams need a shared understanding of the hormonal disease and overall treatment plan. Follow-up imaging remains important after an operation; replacing a valve does not remove the underlying tumor. Patients should understand which team will arrange the next scan, what symptoms should prompt an earlier review, and how cardiac findings may affect the timing of other procedures.
Evidence: [12]
Carcinoid crisis is a medical emergency
Carcinoid crisis involves abrupt, potentially dangerous circulatory instability, sometimes with severe flushing or breathing problems. Surgery and anesthesia are recognized settings in which it can occur. A patient should make sure the procedural and anesthesia teams know about a NET and any hormone-related symptoms well before an intervention.
Seek emergency help for collapse, severe difficulty breathing, confusion with marked weakness, or rapidly worsening symptoms that suggest shock. Do not wait for a routine clinic reply or assume these changes are an ordinary flushing episode. Emergency clinicians need to consider other causes too, including an allergic reaction, infection, bleeding, or a heart problem.
Prevention and treatment require an experienced clinical team. In a prospective surgical series, crises still occurred despite preventive octreotide infusions. That finding is important because receiving preventive medicine does not guarantee protection. Close monitoring and rapid treatment of blood-pressure instability remain essential. Patients should not try to reproduce hospital crisis protocols with extra medication at home unless a specialist has supplied a specific emergency plan.
Evidence: [13]
Planning safely for procedures
Studies of perioperative carcinoid crisis use different definitions and preventive protocols, which makes risk estimates difficult to compare. A systematic review found substantial variation between surgical studies and did not establish that preventive octreotide reliably eliminates crisis risk. This is an area where careful local planning is more appropriate than promising that one standard regimen works for everyone.
For a planned procedure, the practical questions are who has assessed the hormonal and cardiac risks, what monitoring is planned, and whether the team has experience managing sudden circulatory changes. A procedure may still be appropriate; the point is preparation rather than automatic avoidance.
Provide a current medicine list and describe recent flushing, diarrhea, wheezing, fainting, or changes in exercise tolerance. Tell the procedural team about previous complications with anesthesia. If instructions from different services conflict, ask them to reconcile the plan before the day of treatment. Decisions about injections, fasting, fluids, and other medicines should come from the clinicians responsible for the procedure.
Evidence: [14]
Somatostatin analogues are central symptom treatments
Somatostatin analogues, including octreotide and lanreotide, are commonly used to suppress hormone-related symptoms. Long-acting formulations provide ongoing treatment, while a clinician may prescribe short-acting octreotide for breakthrough episodes. The products and formulations are not interchangeable without a treatment plan.
The ELECT trial tested lanreotide against placebo in patients with carcinoid syndrome and allowed rescue short-acting octreotide. Participants receiving lanreotide needed rescue treatment on fewer days on average. This supports its role in symptom control, while also showing that some people still require additional treatment.
Useful follow-up includes more than asking whether the injection helped. Record how often breakthrough medication is needed, whether the benefit lasts throughout the injection cycle, and whether flushing and diarrhea respond differently. These details give the specialist a clearer basis for adjustment. Do not shorten injection intervals or add rescue doses without instructions. Persistent symptoms may indicate inadequate hormone suppression, but they can also reflect a different cause that would not improve with more of the same medicine.
Evidence: [15]
Symptom control and tumor control are measured differently
Somatostatin analogues can also have an antiproliferative effect, meaning they may slow tumor growth in appropriate NETs. The PROMID trial evaluated long-acting octreotide in patients with well-differentiated metastatic midgut tumors and demonstrated a delay in tumor progression compared with placebo. That is a tumor-control outcome, not a claim that the treatment eradicates metastatic disease.
This distinction helps explain why a treatment can be considered useful even when scans do not show dramatic shrinkage. Stable tumor measurements over time may represent a worthwhile result. Equally, a reduction in bowel movements does not necessarily tell the team what is happening to tumor size.
Clinical reviews therefore consider symptoms and imaging separately. Ask what outcome the current treatment is intended to achieve and which test will measure it. The answer may include maintaining stability, reducing hormone-related problems, or preparing for another therapy. A trial’s average result provides evidence for a treatment choice; it cannot predict exactly how long a particular person will benefit.
Evidence: [16]
Why the exact NET diagnosis affects treatment choices
Evidence from one NET population cannot always be transferred to another. For example, CLARINET studied lanreotide in selected advanced, receptor-positive, nonfunctioning enteropancreatic NETs. Its findings supported delaying progression in that population, but the trial was not designed primarily to test diarrhea relief in people with active carcinoid syndrome.
This matters when reading about a treatment online. A drug may have evidence for tumor control, hormone control, or both, and the study population may differ from the person considering it. Tumor origin, differentiation, proliferation rate, and receptor findings influence how closely a published study applies.
A useful discussion with the specialist is therefore: “Which features of this tumor make this treatment suitable?” That question is more informative than asking which drug is best for every NET. It also helps explain why two people with apparently similar diagnoses receive different sequences of therapy. Differences in previous treatment, disease behavior, and tolerance can matter even when the medicine names and scan terminology look familiar.
Evidence: [17]
When symptoms break through treatment
Symptoms that remain troublesome despite standard therapy are sometimes described as refractory carcinoid syndrome. Before escalating treatment, specialists review whether the medication is being delivered and absorbed as intended. Injection-site problems and loss of effect toward the end of a dosing cycle can be relevant. New tumor-related activity is another possibility.
Options may include modifying the somatostatin-analogue regimen, using prescribed short-acting rescue treatment, adding a diarrhea-specific medicine, or considering treatment directed at tumor deposits. Some strategies are outside standard product labeling and require specialist judgment. Availability also differs between health systems.
A structured symptom record can help distinguish a consistent end-of-cycle pattern from symptoms that persist continuously. Include injection dates, missed doses, rescue use, and the timing of bowel changes. Bring this information to the team rather than attempting your own dose escalation. If tumor-directed treatment is added, the team should explain how ongoing hormone suppression will be maintained. A new cancer therapy does not automatically replace the existing plan for managing secretory symptoms.
Evidence: [18]
Telotristat: an additional option for persistent diarrhea
Telotristat ethyl reduces serotonin production and is used with somatostatin-analogue therapy for adults whose carcinoid-syndrome diarrhea is inadequately controlled by that therapy alone. It is a targeted symptom treatment, not a general substitute for the tumor-management plan. A clinician should first consider whether serotonin is actually driving the ongoing diarrhea.
Constipation can become severe. The prescribing information advises stopping telotristat and contacting the prescriber immediately for severe constipation or severe, persistent, or worsening abdominal pain. Follow the medicine’s safety instructions; fewer bowel movements are not beneficial when accompanied by concerning symptoms.
The prescriber also reviews other medicines for interactions and explains the timing relative to any short-acting octreotide. This is a reason to keep an accurate medication list across oncology, primary care, and pharmacy appointments. Ask what improvement to expect, when response will be reviewed, and what side effects should trigger a call. The appropriate treatment endpoint includes safer, more manageable bowel function, not merely the lowest possible stool count.
Evidence: [19]
What a falling hormone marker does and does not show
The TELECAST trial studied telotristat in a broader carcinoid-syndrome population than earlier studies and evaluated changes in urinary 5-HIAA as well as safety. It found reductions in this biochemical marker with treatment. That result supports the medicine’s effect on serotonin production.
However, a biochemical response and a clinical response are not identical. A laboratory value can improve while another cause of diarrhea remains active. Conversely, a person may experience a meaningful reduction in urgency without every test returning to the reference range. Both experiences deserve discussion rather than being dismissed because only one measurement has improved.
It is also important not to extend a biomarker finding beyond what a study established. A lower 5-HIAA result does not by itself demonstrate that existing valve damage has reversed, that metastatic deposits have disappeared, or that a treatment has extended an individual’s life. Monitoring should connect the measurement to a specific clinical question. Ask how the result will change management and what other information is needed before drawing conclusions.
Evidence: [20]
Persistent diarrhea may reflect poor digestion
Somatostatin analogues can reduce pancreatic digestive enzyme secretion as well as suppress tumor-related hormones. Some treated patients therefore develop pancreatic exocrine insufficiency, in which food is not digested adequately. A prospective observational study documented this problem during therapy, emphasizing that diarrhea after treatment starts is not always evidence that the syndrome is worsening.
Symptoms can include bloating, gas, and diarrhea; fatty or difficult-to-flush stools may provide another clue. The team may consider stool testing and, when appropriate, pancreatic enzyme replacement. The goal is to address impaired digestion while retaining necessary control of the NET and its secretions.
Describe changes in stool appearance, meal-related symptoms, and weight when seeking help. Simply removing more foods can reduce nutritional intake without correcting the underlying problem. Likewise, increasing a hormone-suppressing medicine without reassessment may fail to address the reason for continued bowel symptoms. This is one example of why oncology and gastrointestinal expertise can be useful together, especially when a patient’s symptoms change after a treatment adjustment.
Evidence: [21]
Bile acids can contribute to diarrhea too
Bile acids normally help digest fats and are then largely reabsorbed. When excessive bile acids reach the colon, they can contribute to loose stools. This is especially relevant after some intestinal operations, but it should not be ruled out simply because a patient has not had ileal surgery.
A study of patients with NETs who were being investigated for diarrhea found bile acid malabsorption in many of those tested, including some without ileal resection. Because the participants were selected for clinical evaluation, its percentage should not be treated as the prevalence in all people with NETs. The practical message is that this is a potentially overlooked explanation for symptoms.
A specialist may use locally available testing or an appropriately supervised therapeutic approach to investigate the possibility. The important distinction is causal: treatment aimed at serotonin secretion does not necessarily correct bile acid handling. Tell the team exactly which bowel operations you have had and when diarrhea began relative to them. Operative records can be useful when anatomy is uncertain.
Evidence: [22]
A practical way to reassess ongoing bowel symptoms
More than one mechanism can be present at the same time. A person may have genuine carcinoid-syndrome diarrhea together with poor fat digestion, bile acid malabsorption, or reduced absorptive capacity after bowel surgery. Treating a second cause does not invalidate the original diagnosis. It often explains why partial improvement rather than complete relief followed the first treatment.
The assessment should connect the stool pattern with the treatment and surgical history. Antidiarrheal medicines can have a supporting role, but symptom suppression should not replace evaluation when there is a substantial change. Persistent diarrhea deserves attention because of its effects on hydration, nutrition, and daily functioning.
| Observation to report | Why it helps the review |
|---|---|
| Symptoms worsen before the next injection | Suggests reviewing the duration of hormone control |
| Greasy stools, gas, or meal-related bloating | Raises questions about digestion and absorption |
| Diarrhea began after bowel surgery | Makes the remaining bowel anatomy important |
| Several treatments help only partly | Supports considering overlapping causes |
Evidence: [23]
Nutrition includes checking for deficiencies
Serotonin production uses tryptophan, an amino acid that also contributes to the body’s production of niacin, or vitamin B3. Excessive diversion toward serotonin can therefore affect niacin availability. Research comparing patients with and without the syndrome found biochemical deficiency more often in the syndrome group.
Severe deficiency can cause pellagra, but waiting for a dramatic skin or neurological picture can miss earlier nutritional problems. In the study, biochemical deficiency was more common than overt clinical pellagra. This supports a careful nutritional assessment rather than assuming that the absence of a classic rash means nutrition is adequate.
Unintentional weight loss, a restrictive diet, persistent diarrhea, and new skin changes should be discussed with the care team. Supplementation, when needed, should be selected with clinical guidance. High-dose over-the-counter products are not a substitute for checking the overall problem, and different preparations are not automatically equivalent. The broader goal is adequate energy, protein, and micronutrients while identifying the specific effects of hormone production, impaired absorption, and reduced food intake.
Evidence: [24]
Eating well without unnecessary restrictions
There is no single food list that every person with carcinoid syndrome must avoid. Trigger foods differ, and a food that causes symptoms for one person may be tolerated by another. A dietitian can help preserve nutritional variety while identifying changes that genuinely improve symptoms.
Some people find that smaller meals are easier than large meals, or that alcohol, caffeine, spicy foods, or very fatty meals aggravate symptoms. A food-and-symptom diary can reveal whether an apparent trigger is consistent. Make changes in a way that allows their effect to be assessed rather than eliminating many foods simultaneously.
Protein-containing foods and adequate overall intake remain important, particularly when appetite is poor or weight is falling. Restrictive diets can unintentionally make deficiencies worse. Foods temporarily excluded before a laboratory test are not necessarily foods that must be excluded permanently. If diarrhea persists despite sensible dietary adjustments, contact the clinical team; the next step may be medical evaluation rather than further restriction. Ask for dietetic support early when eating has become difficult or anxiety-provoking.
Evidence: [25]
When liver-directed treatment may help
For selected patients with substantial tumor deposits in the liver and inadequate symptom control, reducing the hormone-producing tumor burden may improve symptoms. Liver-directed options include procedures that interrupt a tumor’s blood supply or otherwise treat deposits locally. Selection depends on disease distribution, liver function, prior treatment, and the overall management strategy.
These procedures are not interchangeable, and symptom improvement does not necessarily mean all disease has been eliminated. Specialists weigh the potential benefit against procedure-related risks and the need to preserve functioning liver tissue. They also consider how an intervention will fit with other available therapies.
A multidisciplinary discussion is particularly useful when several reasonable options exist. Ask whether the main goal is hormone relief, tumor control, or both; what recovery may involve; and how the team will determine success. Hormone-related and cardiac risks need attention around an intervention. A decision to use a liver-directed treatment should come with a clear plan for symptom medicines, monitoring, and follow-up rather than an assumption that the procedure ends all ongoing care.
Evidence: [26]
PRRT can address selected receptor-positive disease
Peptide receptor radionuclide therapy, or PRRT, delivers radiation through a compound that targets somatostatin receptors. It is considered for appropriate receptor-positive NETs after the specialist team reviews the tumor’s characteristics and treatment history. It is a tumor-directed treatment, although improvement in hormone-related symptoms may also be an important benefit.
In the NETTER-1 study population with progressive midgut NETs, lutetium-177 dotatate delayed deterioration in several quality-of-life measures compared with high-dose octreotide. These included diarrhea, fatigue, pain, and overall health status. Those results support discussing function and wellbeing alongside scan measurements when evaluating treatment.
A clinical trial result describes outcomes in a selected group. It does not establish that every patient with carcinoid syndrome should receive PRRT, or that every symptom will respond. Receptor imaging and other clinical assessments help determine suitability. Ask which benefits are realistic in the individual situation, what alternatives remain available, and whether the existing hormone-suppression regimen will continue during the treatment course.
Evidence: [27]
PRRT requires safety monitoring
Targeted radiation still has potential effects on healthy tissues. Before and during lutetium-177 dotatate treatment, the team evaluates blood counts and kidney function and considers other relevant organ risks. Treatment may need to be delayed or adjusted if safety measurements change. Monitoring continues afterward because some complications can appear later.
An amino acid infusion is used as part of the treatment protocol to reduce radiation exposure to the kidneys. The clinical service also provides instructions about hydration, urination, and limiting radiation exposure to other people after treatment. These instructions should come from the treating center and reflect the person’s circumstances.
Discuss pregnancy, breastfeeding, contraception, and fertility concerns before therapy. Do not assume that a treatment described as targeted has no reproductive or long-term risks. Ask for written home precautions and a contact number for unexpected symptoms. Understanding the practical plan in advance helps patients arrange travel, caregiving, and household contact appropriately without relying on rules found for a different radioactive treatment.
Evidence: [28]
Other tumor therapies depend on the cancer, not just the syndrome
Treatment options for the underlying NET continue to evolve. In March 2025, the US Food and Drug Administration approved cabozantinib for previously treated, unresectable, locally advanced or metastatic, well-differentiated pancreatic and extra-pancreatic NETs in adults and eligible adolescents. The approval was based on tumor-control evidence from the CABINET trial.
This does not make cabozantinib a universal first treatment for carcinoid syndrome or a replacement for specific management of hormone-related diarrhea. Its place depends on the cancer diagnosis, prior therapies, suitability, and local availability. A tumor-directed medicine may have side effects that overlap with existing symptoms, so baseline bowel function and other problems should be documented.
When a new medicine is proposed, clarify whether the purpose is to slow cancer progression, reduce secretion, or achieve both. Ask what monitoring is required and how side effects will be distinguished from the syndrome itself. Approval in one country also does not establish access or reimbursement everywhere. The care team can explain which current options are relevant in the local setting.
Evidence: [29]
Living with symptoms is part of the clinical picture
The burden of carcinoid syndrome extends beyond a bowel-movement count. A survey of treated adults found that greater symptom burden was associated with poorer quality of life. Urgency can affect work, social plans, sleep, and confidence about leaving home. These effects deserve a place in the consultation even when scans are stable.
Describe what symptoms prevent you from doing. For example, needing immediate bathroom access is different from simply passing an additional stool each day. Fatigue, disturbed sleep, and avoidance of meals can make a modest numerical change clinically meaningful. A treatment review should consider whether everyday functioning is improving, not just whether a laboratory marker has fallen.
Supportive care can be discussed alongside active cancer treatment. Practical adjustments, emotional support, and help coordinating appointments can reduce the burden of living with a chronic illness. These needs do not imply that the symptoms are psychological. They recognize that hormone-related disease affects a whole person. Ask which member of the team can help with the particular problem that is limiting daily life most.
Evidence: [30]
Follow-up and questions for the next appointment
Follow-up remains important after treatment, including when symptoms have improved. Visits can assess recovery, persistent side effects, new symptoms, and evidence of recurrent or changing disease. The schedule depends on the tumor and treatment history, and some patients need monitoring for many years. A general timetable cannot replace the plan made for an individual case.
Do not wait for the next routine visit to report new or worsening flushing, persistent diarrhea, or abdominal pain. Ask who should be contacted between appointments and whether there is an out-of-hours number. Keeping a treatment summary can help different clinicians understand the diagnosis and current medicines.
Useful questions include: Which symptoms should prompt an urgent call? What tests are being followed and why? Who is coordinating heart assessment? Could an additional cause explain the diarrhea? How will we judge whether the present treatment is working? What support is available for nutrition and treatment side effects? Clear answers turn follow-up into an active care plan rather than a sequence of disconnected tests.
Evidence: [31]
For broader symptom context, read our guide to other causes of diarrhea. Our separate guide explains pheochromocytoma and its hormone effects.
Video explanation
This existing overview is supplementary educational material. The written guide and its dated official sources should guide your discussion with a specialist; a video cannot provide an individual diagnosis or treatment plan.





