

Pheochromocytoma is a rare tumor of the adrenal gland that can release excess stress hormones. It may cause episodes of headache, sweating and a racing heart, but some people have few symptoms or normal blood pressure between episodes. Diagnosis depends on appropriately collected laboratory tests and imaging, followed by specialist assessment. Many localized tumors can be removed surgically; careful preparation and long-term follow-up remain important. This guide explains the condition, its relationship to paraganglioma, testing, genetics and current treatment options. [1, 2]
Educational information, updated October 6, 2026. This page does not diagnose symptoms or replace care from a qualified health professional.
What is pheochromocytoma?
The adrenal glands sit above the kidneys. Each has an outer cortex and an inner medulla, which perform different jobs. Pheochromocytoma develops from chromaffin cells in the medulla. These cells normally make catecholamines, including epinephrine and norepinephrine, also called adrenaline and noradrenaline. The hormones help adjust circulation and energy use during stress. A tumor can disrupt that regulation and expose the body to more hormone activity than it needs. [1]
Catecholamines act through receptors in blood vessels, the heart and other tissues. Excess activity can tighten blood vessels, accelerate the heartbeat and alter blood glucose. Hormone release may occur in bursts, remain more continuous, or be too limited to cause recognizable symptoms. The amount released, the mixture of hormones and the body’s response all help explain why two people with the same tumor diagnosis may have very different experiences. [1, 2]
Pheochromocytoma and paraganglioma are related
A similar tumor outside the adrenal gland is called a paraganglioma. These tumors develop from related cells along nerve pathways, including in the abdomen, chest, pelvis, head and neck. Clinicians often use the abbreviation PPGL for pheochromocytoma and paraganglioma together. The location matters because it affects which hormones may be produced, what symptoms appear, which scans are useful and how treatment can be performed safely. [1]
Many abdominal or chest paragangliomas can produce catecholamines. Most head and neck paragangliomas do not cause the typical adrenaline-related syndrome, although exceptions occur. Instead, a head or neck tumor may be noticed because of a lump, hearing changes, swallowing problems or pressure on nearby structures. A normal hormone test therefore does not answer every question about every paraganglioma. Specialist assessment combines the tumor’s location with laboratory and imaging findings. [1, 2]
How common is it, and what causes it?
Pheochromocytoma is uncommon, and it accounts for only a small proportion of high blood pressure. It can occur at different ages and may affect one adrenal gland, both glands or occur alongside other related tumors. Some diagnoses follow investigation of symptoms; others begin with an adrenal mass seen on a scan performed for an unrelated reason. Genetic screening can also identify a tumor before a person feels unwell. [1]
The underlying problem is abnormal growth of the cells that form the tumor. In some people, a disease-associated genetic change is inherited. In others, changes arise within tumor cells without an identified inherited predisposition. There is no established lifestyle measure that reliably prevents pheochromocytoma. Ordinary emotional stress does not establish its cause, although stress can influence symptoms or test results. Having the condition is not evidence that someone failed to manage stress appropriately. [1, 6, 7]
Symptoms and blood pressure can vary
Headache, sweating and a pounding or rapid heartbeat are the best-known symptom combination. Other possible features include trembling, pallor, a sense of alarm, nausea, fatigue and changes in weight or glucose regulation. Episodes can begin suddenly and may vary in intensity and duration. Some people describe a clear pattern; others cannot identify one. The classic combination is useful background knowledge, but requiring all three symptoms would miss some cases. [1, 2]
Blood pressure may remain high, rise sharply during episodes or be normal when it is measured. Some people also experience dizziness on standing or periods of low pressure. A single normal office reading cannot rule out PPGL when there is a stronger reason to investigate. Equally, a high reading does not identify the cause. Most people with hypertension do not have this rare tumor, so clinicians consider the broader pattern. [1, 2]
Physical exertion, certain medicines, anesthesia, childbirth or manipulation of a tumor may provoke hormone release in some circumstances. Symptoms may also occur without an obvious trigger. This variability makes a detailed history more useful than a checklist of foods or activities. A person awaiting evaluation should discuss medicines and procedures with their clinical team instead of attempting to reproduce an episode or stopping prescribed treatment to see what happens. [1, 2]
Symptoms overlap with more common conditions
Palpitations and sweating can occur with anxiety, menopause, thyroid disease, low blood glucose, medication effects and several heart conditions. Overlap does not make symptoms imaginary, and it does not make pheochromocytoma the most likely explanation. Testing becomes more informative when a clinician weighs symptoms alongside blood pressure patterns, imaging findings, family history and previous results. A careful evaluation can investigate a possible hormone disorder while remaining open to another explanation. [2, 5]
Some tumors are discovered without noticeable symptoms. This can happen during assessment of an incidental adrenal finding or surveillance for a genetic condition. Lack of symptoms does not automatically mean a tumor is hormonally inactive or safe to manipulate. Conversely, the presence of an adrenal nodule does not prove it is a pheochromocytoma. The laboratory and imaging stages of evaluation address those different questions. [1, 4]
Why a catecholamine crisis is an emergency
Severe catecholamine excess can place dangerous stress on the heart and circulation. Complications can include abnormal heart rhythms, heart muscle injury, heart failure, stroke and damage to other organs. A crisis does not always present as a straightforward high blood pressure episode: circulation can become unstable, and shock may occur. Emergency assessment is therefore driven by the person’s symptoms and overall condition, rather than a single numerical threshold. [1, 2, 3]
Sudden chest pain, severe trouble breathing, fainting with ongoing illness, new neurological symptoms or a sudden severe headache require urgent assessment whether or not pheochromocytoma is suspected. Someone with an established diagnosis should tell emergency staff about it and provide a current medication list if available. Managing a crisis requires monitored medical treatment. Online medication instructions, additional tablets taken without direction or waiting for another home measurement can delay appropriate care. [2, 12]
When clinicians consider testing
Testing may be appropriate when suggestive episodes occur with unusual or difficult-to-control hypertension, when imaging reveals an adrenal mass with relevant features, or when a person has a known hereditary risk. A previous PPGL diagnosis is another reason for ongoing assessment. These pathways differ: investigating a symptom is not the same as monitoring an inherited predisposition or clarifying an incidental scan finding. That distinction influences the choice and interpretation of tests. [1, 2, 4]
The initial consultation usually considers the timing of symptoms, medical history, family history and medicines, including nonprescription products and supplements. Previous scan reports and laboratory results can prevent unnecessary repetition. Clinicians may also assess heart rhythm, glucose or other possible causes of the symptoms. Because the condition is rare, the likelihood before testing matters: a mildly abnormal result has a different meaning in someone with a known risk variant than in someone with isolated, nonspecific symptoms. [1, 2]
Adrenal incidentalomas require their own structured assessment. Clinicians consider whether a mass produces hormones and whether its imaging appearance is concerning. Not every clearly benign-appearing adrenal lesion needs the same PPGL testing pathway under current incidentaloma guidance. The decision belongs with a clinician who can review the actual scan characteristics and clinical context. The phrase “adrenal mass” alone is too broad to determine either a diagnosis or the appropriate next investigation. [4]
Blood and urine metanephrine tests
Common initial tests measure plasma free metanephrines in blood or fractionated metanephrines in a twenty-four-hour urine collection. Metanephrine and normetanephrine are breakdown products of epinephrine and norepinephrine. Measuring these metabolites is generally more informative for initial detection than looking only for a brief rise in the parent hormones. The choice between blood and urine depends on the clinical situation, laboratory methods and whether a reliable sample can be obtained. [1, 2]
A blood test is not simply an adrenaline snapshot taken during an attack. Tumor cells can continuously form metanephrines, which helps make testing useful between episodes. Collection conditions still matter. Many protocols use a period of quiet rest while lying down before the blood draw, with reference ranges appropriate to that sampling method. The laboratory and ordering clinician should provide the instructions for the particular test rather than expecting patients to assemble their own preparation rules. [2, 5]
A timed urine test measures output across the collection period. Missing samples, collecting for the wrong duration or misunderstanding storage instructions can make interpretation unreliable. Laboratories may assess urine creatinine to help judge collection completeness. Practical difficulties, kidney function and the reason for testing can influence whether urine is the best option. Reporting a collection problem is more helpful than assuming that the laboratory result will compensate for it automatically. [5]
Specialist testing sometimes includes other metabolites, such as three-methoxytyramine, in selected circumstances. These tests are not interchangeable with routine screening, and availability differs among laboratories. A test panel should answer a defined clinical question. More measurements do not necessarily create greater certainty, especially when a rare condition is being investigated in someone whose symptoms could have several causes. Interpretation must remain connected to the person’s history and the characteristics of the suspected tumor. [2, 5]
Why an abnormal result needs interpretation
Metanephrine results can be influenced by acute illness, stress, physical activity, sampling position and some medicines. Certain drugs affect the body’s sympathetic signaling, while others interfere with a particular laboratory method. A borderline elevation therefore does not automatically establish a tumor diagnosis. The clinician looks at the size and pattern of the abnormality, the assay and reference range, and whether the collection conditions make a false-positive result plausible. [1, 2, 5]
When findings are uncertain, the next step may be repeating the test under controlled conditions, choosing an alternative test or obtaining specialist advice. Occasionally, a supervised suppression test helps resolve a specific question. This is different from trying to provoke hormone release, which can be dangerous. A markedly abnormal result and a borderline one should not be treated as equivalent, but neither should be interpreted from a number copied out of an online discussion. [1, 2]
Medicines should be reviewed with the prescriber rather than stopped independently. The risks of withdrawal, unstable blood pressure or worsening another condition can outweigh any benefit from altering a test result. Normal metanephrines generally make a catecholamine-producing PPGL less likely when the correct test is properly collected. Important exceptions include some very small tumors and tumors that produce little or none of the measured metabolites, particularly in surveillance or head and neck disease. [2, 5]
How imaging locates and characterizes a tumor
For a suspected hormone-producing PPGL, convincing biochemical evidence usually comes before scans intended to locate the source. There are exceptions, including a mass already found incidentally, suspected nonsecreting disease and urgent clinical circumstances. Computed tomography, or CT, and magnetic resonance imaging, or MRI, show the tumor’s position and relationship to nearby organs and blood vessels. That anatomical information helps the team plan further assessment and, when appropriate, an operation. [1, 2]
Functional imaging asks a different question: whether tissue takes up a tracer associated with a particular biological property. Options include selected PET tracers and MIBG imaging. Choice depends on factors such as the tumor’s location, genetic background, suspected spread and whether a tracer-targeted treatment is being considered. A scan used to select a treatment is not necessarily the best first scan for every patient. Availability and local expertise also affect the pathway. [1, 2]
No single scan answers every diagnostic question. A mass can resemble other adrenal lesions, while small or biologically different deposits may be more visible with one method than another. Imaging is interpreted together with laboratory findings and previous studies. Comparison over time can matter as much as a single measurement. Questions about contrast, radiation, pregnancy, kidney function or implanted devices should be discussed before the study so the imaging team can choose an appropriate approach. [1, 2, 4]
Why biopsy is approached cautiously
Putting a needle into an unsuspected catecholamine-producing tumor can trigger a dangerous hormone release. For that reason, an adrenal mass should not simply proceed to biopsy without appropriate endocrine assessment. Biopsy is not the routine way to establish most pheochromocytoma diagnoses. When tissue sampling is genuinely necessary in a complex case, the decision and safety planning belong to the specialist team, which weighs what the result would change against the procedural risk. [1, 2, 4]
| Test | Main question | Important limitation |
|---|---|---|
| Plasma or urine metanephrines | Is there evidence of excess catecholamine metabolism? | Collection conditions, medicines and tumor biology affect interpretation |
| CT or MRI | Where is the mass, and what structures surround it? | Appearance alone may not establish tumor type or future behavior |
| Selected functional imaging | Where is tracer-avid disease, and could a targeted approach be relevant? | The best tracer depends on the clinical question and availability |
| Germline genetic testing | Is there an inherited tumor predisposition? | A negative or uncertain result may leave some questions unresolved |
Genetic counseling is part of modern care
PPGL has an important inherited component. Genetic counseling and consideration of germline testing are relevant to everyone with a confirmed diagnosis, even when there is no obvious family history. Examples of associated conditions include multiple endocrine neoplasia type two, von Hippel-Lindau disease, neurofibromatosis type one and hereditary paraganglioma-pheochromocytoma syndromes. The specific gene can influence the chance of additional tumors, appropriate surveillance and the information that may be useful to relatives. [6, 7]
A germline variant is present in the genetic material a person was born with and may be passed through a family. A somatic variant develops in tumor cells and does not automatically imply that relatives carry it. Genes implicated in PPGL include RET, VHL, NF1 and several genes involved in the succinate dehydrogenase complex, as well as others. For background on DNA and inheritance, Sly Academy’s nucleic acids study guide explains the underlying biology. [1, 7]
A genetic result can be positive for a disease-associated variant, negative for the variants tested, or uncertain. A variant of uncertain significance is not the same as a confirmed inherited diagnosis and generally should not drive predictive testing or major management decisions by itself. Testing also has limits: a negative panel does not exclude every inherited explanation. A genetics professional can explain what the laboratory has established and what remains unresolved. [11]
When a pathogenic germline variant is identified, relatives may be offered targeted testing and gene-specific surveillance. Inheritance patterns, the chance that a carrier develops disease and the age at which screening begins vary by gene. Families should not apply one person’s monitoring schedule to everyone else. Counseling can also address the practical and emotional implications of testing, including how to share relevant information without assuming that every relative will develop a tumor. [6, 7]
Localized disease and metastatic potential
Older descriptions often divide these tumors into “benign” and “malignant.” Contemporary discussions increasingly emphasize whether disease is localized or metastatic and recognize that PPGLs have metastatic potential. Metastatic disease means tumor deposits are found in sites where normal chromaffin tissue does not belong, such as bone, liver or lymph nodes. A second tumor in another typical paraganglial location may instead represent an additional primary tumor, particularly in hereditary disease. [1, 2]
Microscopic examination helps confirm the diagnosis and provides useful information about tumor features. However, pathology alone cannot guarantee that a tumor will never recur or spread. Risk assessment can take account of tumor size, location, genetic findings and other clinical or pathological features. Some SDHB-associated tumors carry a higher metastatic risk, but a genetic association describes probability across groups; it does not establish an individual person’s future course. [1, 6]
Prognosis varies substantially. Localized disease that can be fully removed differs from a tumor involving vital structures or disease present at multiple distant sites. Even among people with metastatic PPGL, the pace of growth and response to treatment can differ. Survival figures drawn from small or mixed study populations should not be treated as a personal forecast. A more useful discussion explains the known extent of disease, the uncertainties and the plan for reassessment. [1, 2]
Specialist treatment begins before an operation
A coordinated team may include endocrinology, endocrine surgery, anesthesia, radiology, genetics and, when needed, oncology or other specialists. The immediate priorities are to understand hormone production, assess the extent of disease and reduce avoidable risk. Heart and circulatory complications can influence preparation and timing. Experienced centers are particularly valuable for hereditary disease, multiple tumors, complex locations, pregnancy and metastatic disease, where decisions often cross several specialties. [1, 2]
For a hormone-producing tumor, preparation commonly includes clinician-directed medicines that reduce catecholamine effects. Alpha-adrenergic blockade is an established component of many preoperative plans. Other medicines may be added for specific reasons under supervision. Drug choice, monitoring and the order of treatment matter because the wrong approach can worsen cardiovascular instability. These decisions depend on blood pressure, heart function, other conditions and the operation being planned. A general article cannot supply a safe individual medication sequence. [1, 2]
Fluid and salt management may also form part of specialist preparation, but it must reflect the person’s heart, kidney and circulatory status. Generic advice to increase either can be inappropriate for someone with a complicating condition. Preparation is a supervised process with a clear contact plan for troublesome symptoms. Patients should receive instructions from their own team about existing medicines, planned procedures and the circumstances that require urgent review before surgery. [1, 2]
Surgery and early recovery
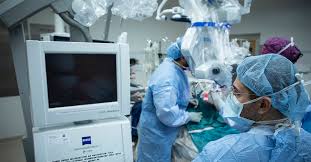
Surgery is the main treatment for many localized pheochromocytomas. The surgeon considers the tumor’s size, anatomy, evidence of invasion and the person’s overall health when choosing an approach. Minimally invasive adrenal surgery is suitable in many cases, while an open operation may be preferable when disease is larger or more complex. The aim is safe removal with appropriate handling of the tumor, rather than choosing an incision solely for its cosmetic appearance. [1, 2]
In selected patients, especially some with hereditary disease or tumors affecting both adrenal glands, a team may consider adrenal cortex-sparing surgery. Retaining functioning cortex can reduce the likelihood of permanent adrenal hormone replacement, but the operation has tradeoffs, including the possibility of another tumor in retained tissue. This is a specialized decision based on the pattern of disease and the person’s priorities. It is not suitable for every tumor or every surgical situation. [1, 2]
During and after surgery, blood pressure and heart function require close observation. Once the hormone source is removed, circulation and glucose regulation can change quickly. Monitoring may identify low blood pressure or low blood glucose, as well as ordinary surgical complications. Existing antihypertensive or diabetes treatment may need adjustment by the team. Improvement in symptoms is encouraging, but it does not replace postoperative laboratory assessment or review of the surgical and pathology findings. [1, 2]
Removing one adrenal gland does not usually mean a person will need lifelong adrenal replacement hormones if the other gland functions normally. Removing both glands, or losing adequate functioning cortex, creates a different situation and requires an ongoing replacement plan. Recovery advice should clearly explain medication needs, wound care, activity, warning symptoms and follow-up arrangements. The long-term plan also needs to account for any remaining tumor, inherited risk or cardiovascular problems identified before surgery. [1, 2]
Treatment when disease cannot be fully removed
Unresectable or metastatic PPGL requires an individualized strategy. The team considers how quickly disease is growing, where it is located, the symptoms it causes and what treatment the person can tolerate. Hormone control remains important even when a treatment is directed at tumor growth. For selected slowly progressing cases, planned observation may be appropriate; other situations call for treatment sooner because of symptoms, progression or risk to an organ. [1, 2]
Options can include surgery for selected sites, external radiation, local procedures, chemotherapy, targeted medicines and radionuclide therapies. These approaches have different purposes: reducing hormone-related symptoms, controlling a painful or threatening deposit, or slowing disease across the body. Some radionuclide approaches require the tumor to take up a particular tracer sufficiently. A scan can therefore help determine eligibility, but treatment availability, regulatory status and access vary among countries and specialist centers. [1, 2]
A recent change in United States treatment options
On May 14, 2025, the US Food and Drug Administration approved belzutifan for adults and children aged 12 years and older with locally advanced, unresectable, or metastatic pheochromocytoma or paraganglioma. Belzutifan targets hypoxia-inducible factor two alpha, part of a pathway involved in cellular responses to oxygen. This approval means it should no longer be described simply as an experimental PPGL treatment in the United States. Eligibility and approval elsewhere require local verification. [9, 10]
Belzutifan does not work for every person and can cause serious adverse effects, including anemia and low oxygen levels. Its prescribing information also includes an embryo-fetal toxicity warning. Decisions about it require specialist assessment, monitoring and a discussion of other options. An approval does not establish one universal first choice for every tumor. The appropriate sequence of treatments depends on disease biology, prior care, competing risks and the person’s goals. [9, 10]
Why long-term follow-up matters
Follow-up checks whether hormone excess has resolved and whether disease persists, recurs or develops elsewhere. A reassuring postoperative result establishes a useful baseline, but recurrence can happen years later. The care plan may include symptom review, blood pressure assessment, biochemical tests and imaging when appropriate. A tumor that did not produce measurable hormones may need a different surveillance approach because routine metanephrine testing alone may not reliably identify a recurrence. [1, 8]
Guidelines support prolonged follow-up after surgery. European guidance recommends at least ten years for all operated patients and lifelong annual follow-up for people at higher risk, including those with a genetic disease, young age, a large tumor or a paraganglioma. Other guidance supports lifelong biochemical surveillance more broadly. The practical schedule should be individualized and documented, rather than ending automatically when someone feels well or reaches an arbitrary anniversary. [1, 8]
Continuity becomes especially important when people move, change clinicians or transition from pediatric to adult services. Keeping a concise record of the tumor location, operation, pathology, genetic results and planned surveillance can help the next team understand what needs monitoring. Persistent hypertension may still require treatment even after successful tumor removal. Follow-up should therefore assess the person’s overall health as well as the specific question of recurrent PPGL. [1, 2, 8]
Pregnancy, children and family planning
Pregnancy with a known or suspected PPGL needs prompt coordination among endocrine, obstetric, anesthetic and surgical specialists. Hormone excess can pose serious risks, while the safest investigations and treatment timing depend on the circumstances. High blood pressure during pregnancy has several possible causes, so diagnosis should be established carefully. People with a known hereditary predisposition can discuss assessment before pregnancy rather than waiting for symptoms to become difficult to interpret. [2, 6]
Children and adolescents require age-appropriate evaluation and support. A hereditary explanation is especially relevant in younger patients, and surveillance may begin in childhood for some known familial variants. Counseling should involve parents or guardians while giving the young person an appropriate voice in decisions. The transition to adult care needs an explicit monitoring plan. Genetic and reproductive discussions should explain options and uncertainties without implying that one family-planning decision is right for everyone. [6, 7]
Living with the diagnosis and understanding research
A rare diagnosis can create practical burdens alongside its medical effects: travel to specialists, time away from work, uncertainty while results are pending and questions from relatives. Useful clinical conversations clarify who coordinates care, which symptoms require urgent attention and how results will be communicated. A symptom record can help describe patterns, provided it does not delay care during an emergency. People should also be able to discuss fatigue, sleep, distress and support needs. [1, 2]
Research continues into genetic pathways, biomarkers, imaging and treatment combinations. A promising laboratory result is an early step; evidence from people is needed to assess benefit, safety and the groups most likely to respond. Clinical trials have eligibility criteria and tradeoffs, and their availability changes. A specialist can help distinguish an established treatment from an off-label option or a research intervention and explain what participation would involve. [1, 2, 9]
Research reports also use outcome measures that need careful reading. An objective response means a tumor has shrunk enough to meet specified criteria; it does not mean that the disease has been permanently eliminated. The FDA’s belzutifan assessment included a group of 72 patients and considered both response and how long responses lasted. Findings from a treated group can demonstrate activity, but they do not by themselves prove that a medicine is superior to every alternative. Benefits and adverse effects both matter. [9]
For students, pheochromocytoma connects hormone signaling, receptor biology, metabolism and genetics. Sly Academy’s biology flashcards can support revision of general biological concepts alongside this guide. Clinical decisions require additional context that a study resource cannot provide. The most useful understanding is that hormone activity, tumor location, inherited risk and disease extent are separate questions, and each contributes to an appropriate diagnostic, treatment and follow-up plan. [1, 2, 6]
Frequently asked questions
Can you have pheochromocytoma with normal blood pressure?
Yes. Blood pressure can be normal between episodes, and some tumors cause few recognizable symptoms. A normal reading does not exclude pheochromocytoma when there is a relevant adrenal finding, inherited risk or other clinical reason to investigate. Most people with palpitations or hypertension have another explanation. [1, 2]
Does a raised metanephrine result mean I have a tumor?
No. Illness, stress, collection conditions and some medicines can affect results, particularly small elevations. A clinician interprets the pattern and degree of elevation alongside symptoms, risk factors and the laboratory method. Repeat testing under controlled conditions may be appropriate. Do not stop prescribed medicines without medical advice. [1, 2, 5]
Is pheochromocytoma always cancer?
Many pheochromocytomas are localized when diagnosed. These tumors have metastatic potential, and pathology alone cannot guarantee that a tumor will never recur or spread. Specialists assess disease extent and risk factors, then plan long-term follow-up. Metastatic disease means spread to sites where normal chromaffin tissue is not present. [1, 2]
Should everyone with pheochromocytoma discuss genetic testing?
Yes. Genetic counseling and consideration of germline testing are relevant to all people with a confirmed pheochromocytoma or paraganglioma, including those without a known family history. Results can influence surveillance and help identify relatives who may benefit from testing. The appropriate test and interpretation require genetic expertise. [6, 7]
Will surgery mean that follow-up can stop?
No. Removing a localized tumor may resolve hormone excess, but recurrence or additional tumors can develop later. Follow-up is long term and often lifelong, especially with hereditary disease or other higher-risk features. The schedule depends on the original tumor, genetics, biochemical findings and the treating team’s guidance. [1, 8]
Are there treatments for metastatic pheochromocytoma?
Yes. Specialists may use hormone-control medicines, selected local treatments, radiation, radionuclide therapy, chemotherapy or targeted treatment. In the United States, belzutifan is approved for adults and children aged 12 years and older with locally advanced, unresectable, or metastatic PPGL. Treatment choice, eligibility and availability depend on the individual situation and country. [1, 9, 10]
Sources
Numbered references support the medical information above. Sources were checked on October 6, 2026. Guidelines from earlier years remain useful for established principles; newer regulatory information is cited separately for treatment approvals.
- National Cancer Institute: Pheochromocytoma and Paraganglioma Treatment, health professional PDQ. Anatomy, presentation, diagnosis, management and follow-up. Genetic testing discussion is supplemented by sources 6 and 7.
- Japan Endocrine Society Clinical Practice Guideline for the Diagnosis and Management of Pheochromocytoma and Paraganglioma 2025. Current specialist guidance; local testing and reimbursement provisions are not presented as universal rules.
- NHS: Phaeochromocytoma. Symptoms and urgent complications.
- European Society of Endocrinology clinical practice guideline on adrenal incidentalomas, 2023. Assessment of incidental adrenal masses and precautions around biopsy.
- ARUP Consult: Pheochromocytoma and Paraganglioma. Metanephrine testing, sampling conditions and interpretation; updated September 2026.
- GeneReviews: Hereditary Paraganglioma-Pheochromocytoma Syndromes. Genetic testing, counseling and hereditary surveillance.
- MedlinePlus Genetics: Hereditary paraganglioma-pheochromocytoma. Genes, inheritance and variable disease expression.
- European Society of Endocrinology: Long-term follow-up after surgery for pheochromocytoma or paraganglioma, 2016. Duration and risk-based follow-up.
- US Food and Drug Administration: Belzutifan approval for pheochromocytoma or paraganglioma, May 14, 2025. Approved population and treatment evidence.
- DailyMed: Current Welireg (belzutifan) prescribing information. Indications, warnings and monitoring requirements; updated June 2026.
- National Cancer Institute: Genetic testing for inherited cancer risk. Germline and tumor testing, negative findings and variants of uncertain significance.
- NHS emergency guidance: heart attack symptoms, stroke symptoms, headache warning signs and fainting with warning signs.





