

This guide is general education for adults. It cannot diagnose diabetes, set personal treatment targets or replace care from your own health professionals. Editorial source-checking is not review by a licensed clinician.
What type 2 diabetes mellitus means
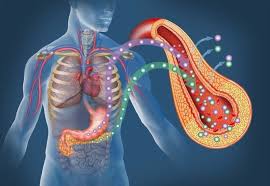
Type 2 diabetes mellitus is a long-term condition in which blood glucose, often called blood sugar, becomes too high. Insulin is a hormone made by the pancreas that helps glucose enter cells for energy. In type 2 diabetes, cells respond less effectively to insulin and the pancreas eventually cannot produce enough to meet the body’s needs. Treatment supports both everyday well-being and long-term health. Food choices, movement, medicines and regular checks can work together; needing medication does not mean that someone has failed. [1]
Insulin resistance and prediabetes are related terms, but they are not interchangeable with diabetes. Insulin resistance describes a reduced response to insulin. Prediabetes describes glucose results above the usual range but below the diabetes threshold. Some people with prediabetes develop type 2 diabetes, while others do not. A clinician can explain which result you have and what follow-up is appropriate. This distinction matters because an abnormal screening result should lead to a specific plan, rather than an assumption that diabetes is inevitable or already established. [2]
Risk factors are a reason to check, not a judgment
Family history, increasing age, previous gestational diabetes, lower physical activity and overweight or obesity can increase the chance of type 2 diabetes. Risk also differs across populations. No single characteristic proves that someone has the condition, and appearance cannot diagnose it. Some risk factors are changeable and others are not. A useful conversation focuses on your actual history, test results and access to support. Telling a clinician about diabetes in a parent or sibling or during a previous pregnancy can help them decide when testing is appropriate. [3]
Possible symptoms include increased thirst, frequent urination, unexplained weight loss, tiredness, blurred vision, slow-healing wounds and repeated infections. Symptoms may build gradually, and some people notice none. Feeling well therefore does not rule out diabetes. Arrange an assessment if these changes develop, especially if several occur together. A symptom list cannot distinguish diabetes from every other cause of fatigue, thirst or urinary frequency. Sudden severe illness, difficulty breathing, confusion or marked drowsiness needs emergency assessment rather than a routine screening appointment. [4] [26]
How diabetes is diagnosed
Diagnosis uses appropriate blood testing interpreted by a health professional. A home glucose meter is useful for monitoring but cannot establish a diagnosis on its own. The following thresholds apply to nonpregnant people; pregnancy uses additional testing pathways and different thresholds. The tests measure different aspects of glucose regulation, so results can disagree. Ask for the actual test name, value and units instead of relying on a message that your “sugar is high.” The clinician must also establish the type of diabetes because treatment depends on it. [5]
| Test | Diabetes threshold | Important context |
|---|---|---|
| HbA1c | 6.5% or higher (48 mmol/mol) | Measures longer-term glucose exposure; some blood conditions affect accuracy. [6] |
| Fasting plasma glucose | 126 mg/dL or higher (7.0 mmol/L) | After at least eight hours without calories. [5] |
| Two-hour oral glucose tolerance test | 200 mg/dL or higher (11.1 mmol/L) | Measured after a standard 75-gram glucose drink. [6] |
| Random plasma glucose | 200 mg/dL or higher (11.1 mmol/L) | Diagnostic with classic hyperglycemia symptoms or a hyperglycemic crisis. [6] |
Unless there is unequivocal hyperglycemia, diagnosis requires two abnormal results: different tests obtained together, or repeat testing at different times. Classic symptoms or a hyperglycemic crisis with diagnostic random plasma glucose can remove that confirmation requirement. When tests disagree, the clinician investigates and repeats the appropriate test rather than averaging incompatible results. A continuous glucose monitor is not a substitute for the diagnostic tests above. [6]
Why HbA1c is useful, and when it misleads
HbA1c, also written A1C, reflects average glucose over roughly three months by measuring glucose attached to hemoglobin in red blood cells. It does not show each daily high or low. Recent blood loss or transfusion, certain anemias, hemoglobin variants and some kidney or liver conditions can make it misleading. Tell the clinician about these circumstances, especially if A1C and home readings seem inconsistent. An unexpectedly reassuring average does not cancel repeated low readings, and an unexpected result should be interpreted in context before treatment is changed. [7]
Screening recommendations are designed to find diabetes before symptoms appear. For example, the U.S. Preventive Services Task Force recommends screening nonpregnant adults aged 35 to 70 who have overweight or obesity, and offering effective prevention support when prediabetes is found. That recommendation is not a reason to ignore symptoms outside that age range. Earlier testing may be appropriate depending on individual risk, and other professional guidelines use broader criteria. Ask which recommendation applies in your setting and when the next test should be repeated if today’s result is normal. [8]
Build a care plan you can actually use
Diabetes self-management education and support, often shortened to DSMES, turns a diagnosis into practical skills. A diabetes educator can help with meal planning, activity, medicines, monitoring, problem-solving and coping with the daily workload. Bring the questions that affect your real routine: night shifts, cooking for a family, needle concerns or uncertainty about a device. Education is useful after diagnosis and when treatment or circumstances change. Ask for a demonstration, then show the technique back so that misunderstandings are caught before you have to manage alone at home. [9]
Glucose targets are personal treatment goals, not diagnostic cutoffs. Common targets for many adults are 80–130 mg/dL before meals and below 180 mg/dL two hours after the start of a meal, but these are not instructions for everyone. Age, other conditions, medicines and the risk of low glucose can change the plan. Agree on when to check, which results require a call and what action is safe between visits. Record the context of an unusual result, such as illness or a delayed meal, rather than treating every number as an isolated verdict. [10]
Meters and continuous glucose monitors
A continuous glucose monitor, or CGM, estimates glucose in the fluid between cells and displays trends over time. Some systems provide alerts or allow data sharing with a chosen supporter. Whether continuous or occasional use is helpful depends on treatment needs, preferences and access. Learn the instructions for your specific model, including when a finger-stick confirmation is needed if readings seem unreliable. Not every device has identical calibration requirements. Discuss alerts and sensor problems with the care team so the information remains useful rather than overwhelming. [11]
Meter technique can affect the result. Wash and dry your hands, use the correct strips and follow storage instructions. Heat, humidity, damaged supplies, certain medicines and some health conditions can interfere with accuracy. Keep the meter and lancing equipment for your own use; sharing can transmit infections. Ask a nurse or pharmacist to watch you test if readings are unexpected. When choosing equipment, consider ongoing strip costs and accessibility features, such as a readable display or spoken results, as well as the initial price. [12]
Medicines are chosen for the whole person
Current ADA/EASD guidance emphasizes individualized care that considers glucose, weight, cardiovascular and kidney health, preferences and practical access. SGLT2 inhibitors and GLP-1-based therapies with proven benefits may be important for people with particular heart or kidney risks even when their A1C is already near goal. The right question is not simply which medicine lowers glucose most, but which outcomes matter for you and what risks or burdens accompany it. Ask why each prescription was selected, what improvement to expect and when the team will review whether it is helping. [46]
Metformin is one established treatment for type 2 diabetes and may be used alone or with other medicines. Stomach upset and diarrhea can occur, and vitamin B12 deficiency is another issue to discuss. Suitability depends partly on other health conditions, including kidney problems. If side effects interfere with eating, work or taking treatment consistently, tell the prescriber rather than quietly abandoning it. A pharmacist can clarify how your particular formulation should be taken and what to do about missed doses. Vomiting, diarrhea or fever also warrants advice about dehydration and your medication plan. [13]
Empagliflozin is an example of an SGLT2 inhibitor. It helps remove glucose through urine and is also used in appropriate patients for heart failure or chronic kidney disease. This explains why a diabetes medicine might be prescribed for a reason beyond a glucose reading. Combination tablets may contain empagliflozin plus another medicine, so keep a list of active ingredients as well as brand names. Ask the pharmacist to help identify what you take and which instructions apply; two differently named boxes can otherwise make a regimen unnecessarily confusing. [14]
Semaglutide is an example of a GLP-1-based treatment. It helps the pancreas release insulin when glucose is high, slows stomach emptying and can reduce appetite. Benefits, indications and precautions depend on the product and the person. A prescriber needs to know about relevant thyroid tumor history, pancreatitis, significant stomach-emptying problems, eye disease and pregnancy plans. Read the medication guide and report troubling symptoms. These treatments are not interchangeable with insulin, and an online description cannot determine which product, formulation or treatment schedule is suitable for you. [44]
Insulin replaces or supplements a hormone the body needs. Different preparations act for different lengths of time, and the prescribed product, device and timing matter. Ask for hands-on training in checking the label, using the device, storing supplies and disposing of needles safely. Never share injection pens, even if the needle is changed. Do not swap insulin types or alter doses without the agreed clinical plan. Insulin use does not turn type 2 diabetes into type 1 diabetes; it is one way to manage insufficient insulin action or supply. [16]
Avoid buying injectable “research” products or assuming that an unapproved compounded GLP-1 product has undergone the same review as an approved medicine. The FDA has reported concerns about dosing errors, fraudulent labels and ingredients in unapproved products. Obtain prescriptions through a qualified professional and a licensed pharmacy, and ask who to contact if instructions or packaging are unclear. A lower advertised price does not establish product quality. If affordability is driving the search, raise that directly with the care team so they can explore legitimate options. [15]
Food, activity and weight without rigid rules
A helpful eating plan can include familiar foods and should fit culture, budget, appetite and other health needs. One practical starting point is the plate method: half nonstarchy vegetables, one quarter a protein food and one quarter carbohydrate-containing foods. It is a planning aid, not a mandatory diet or a promise of a particular glucose result. Water or unsweetened drinks can replace sugary drinks. A registered dietitian can adapt portions and meal timing when kidney disease, digestive problems or medicines make generic advice less useful. [17]
Carbohydrates include sugars, starches and fiber. Bread, rice, potatoes, beans, fruit and milk can all contribute carbohydrate, so looking only at added sugar misses part of the picture. Food labels list total carbohydrate in grams, and the portion you actually eat matters. There is no single carbohydrate allowance that fits every person with diabetes. If you use mealtime insulin, learn the prescribed method for matching food and treatment with an educator. Do not borrow someone else’s insulin-to-carbohydrate calculation or treat a sample menu as a personal prescription. [18]
Fiber-rich foods such as vegetables, whole grains, beans, lentils, nuts and whole fruit can support a balanced eating pattern. Fiber behaves differently from sugars and starches and can help with fullness, bowel function and glucose management. Introduce larger amounts gradually if your usual intake is low, because a sudden change may cause bloating or discomfort. There is no need to replace every familiar food at once. One repeatable change, such as adding beans to a meal or choosing a whole-grain option, can be easier to maintain than a complete kitchen overhaul. [19]
Regular physical activity supports glucose management, heart health and well-being. A common adult goal is at least 150 minutes of moderate activity weekly, approached gradually according to ability. Walking, dancing, swimming and adapted movement can all be options. Start with a manageable duration and choose something you can repeat. Ask about restrictions before a new or harder activity, especially if you have health complications. The goal is a sustainable routine, not exercising through pain or exhaustion to compensate for eating. Keeping a simple activity record can help you notice progress. [20]
For some people with obesity and type 2 diabetes, metabolic or bariatric surgery is a treatment option worth discussing. It can improve glucose regulation and other obesity-related conditions, but it does not guarantee lasting weight loss or permanent remission. Assessment considers likely benefit, surgical risks and the follow-up needed afterward. Ask what long-term nutritional monitoring, support and medication review would involve before making a decision. Surgery belongs within continuing care, rather than being a one-time solution that removes the need for future diabetes checks. [21]
Supplements marketed as a natural diabetes cure deserve caution. Evidence for many products is limited or inconsistent, and some can interact with medicines or harm the kidneys or liver. A supplement label does not establish that the contents will safely control glucose. Tell your clinician and pharmacist about herbs, vitamins and other products you use, including those bought online. Treatment for a documented nutrient deficiency is different from taking an unproven product to replace diabetes care. Do not stop an effective treatment because a testimonial promises reversal. [22]
Low glucose and high-glucose emergencies
Recognize and treat a low promptly
Low glucose, or hypoglycemia, is especially relevant for people taking insulin or medicines such as sulfonylureas. Shaking, sweating, hunger, dizziness, irritability or confusion may develop quickly. A reading below 70 mg/dL is a usual low-glucose threshold. Skipped meals, alcohol, illness and more activity than usual can contribute. Exercise-related lows can occur afterward as well as during activity. Ask which of your medicines can cause lows and how to prevent them. Repeated episodes or loss of warning symptoms should prompt a treatment review, even if the average A1C looks satisfactory. [23]
For an adult who is awake and can swallow safely, a common approach is 15 grams of fast-acting carbohydrate, followed by a glucose check after 15 minutes. Repeat if glucose remains below 70 mg/dL, following the person’s own plan. Glucose tablets or gel with a clearly labeled carbohydrate amount are useful; chocolate and high-fiber foods act too slowly for first treatment. After recovery, have the planned snack or meal to help prevent another low. Get urgent help if the low is not resolving or the person’s ability to treat themselves deteriorates. [24]
High glucose can become a medical emergency
Diabetic ketoacidosis, or DKA, occurs when insufficient insulin leads to a dangerous buildup of ketones. Although more common in type 1 diabetes, it can occur in type 2. Vomiting, abdominal pain, fruity-smelling breath and rapid or deep breathing are warning signs. Seek emergency care for trouble breathing, persistent vomiting with inability to keep fluids down, high ketones or several DKA symptoms together. Do not wait for a routine appointment or assume that type 2 diabetes rules DKA out. Hospital treatment addresses fluids, electrolytes, insulin needs and the trigger. [25]
Hyperosmolar hyperglycemic state, or HHS, is another dangerous complication of type 2 diabetes. Very high glucose and severe dehydration may develop over days or weeks, often with illness. Marked thirst and frequent urination can progress to confusion or unusual sleepiness. These changes require emergency assessment. There is no safe home strategy for deciding that drowsiness is “just high sugar,” and a person who is confused should not drive themselves. The absence of a ketone result does not make severe illness safe to manage alone. [26]
SGLT2 inhibitors have a particular safety issue: ketoacidosis can occur even when glucose is normal or only mildly raised. Nausea, vomiting, abdominal pain, unusual tiredness or breathing difficulty while taking one require prompt medical attention. FDA advice is to stop the SGLT2 medicine and seek immediate care if ketoacidosis symptoms occur. Tell the treating team exactly which medicine you take. Discuss precautions for illness, reduced food intake, fasting and procedures in advance, including when a medicine must be held and how the team will decide it is safe to restart. [43]
Prepare an individual sick-day plan
Illness can raise glucose even when you eat less, while vomiting or reduced intake can also create a risk of low glucose. Before you become ill, agree on a written plan covering glucose checks, whether and when to test ketones, food and fluids, and whom to contact out of hours. Medicine instructions must be individualized; do not apply a blanket rule to continue or stop every diabetes tablet. Ask separately about insulin and each other medicine. Seek urgent help when you cannot keep fluids down or your readings and symptoms are worsening. [27] [13]
Protect your heart, kidneys, eyes and feet
Heart protection involves more than glucose alone. Blood pressure, cholesterol, smoking and existing cardiovascular disease all affect risk. Ask what your blood pressure and cholesterol goals are and whether protective medicines, including a statin, are appropriate. Aspirin is not automatically suitable for everyone. Our guide to blood pressure care and follow-up provides related background, while your diabetes team sets your individual plan. Chest pressure, sudden one-sided weakness or new speech difficulty needs emergency help rather than an adjustment to your next diabetes appointment. [32]
Diabetic kidney disease can develop without obvious symptoms. A urine test checks for albumin leakage, while a blood test estimates how well the kidneys filter. Both matter: a person may feel well and still need follow-up for an abnormal result. People with type 2 diabetes generally need kidney testing every year, with closer monitoring when problems are identified. Ask for the results and what they mean for medicines and future testing. Glucose and blood pressure management can help protect kidney health, and early detection creates more opportunities to act. [28]
Diabetic retinopathy affects blood vessels in the retina and may initially cause no symptoms. Arrange regular retinal assessment rather than waiting until reading or driving becomes difficult. A comprehensive dilated eye examination is one way to detect it, and the eye-care professional sets the follow-up interval according to findings. New floating spots, streaks or worsening vision should be assessed promptly. Managing glucose, blood pressure and cholesterol helps protect vision, but those measures do not replace eye examinations or treatment when retinal disease is already present. [29]
Inspect your feet every day, including the soles and between toes, using a mirror or another person’s help if necessary. Reduced sensation can hide an injury, while poor circulation can impair healing. Look for cuts, blisters, redness, swelling and other changes, and report a wound or suspected infection promptly. Wash in warm rather than hot water, dry carefully and wear well-fitting footwear. Avoid walking barefoot and do not cut away a corn or callus yourself. Ask for professional foot assessment, particularly if you cannot see or reach your feet safely. [30]
Nerve damage can cause burning, tingling, pain or numbness in the feet and sometimes the hands. Other nerves control digestion, bladder function, sexual function and blood pressure responses, so symptoms are not limited to the skin. Tell the clinician about these changes instead of assuming they are an unavoidable part of aging. An assessment can clarify the cause and identify support or treatment. Managing diabetes remains important, but a new symptom should not automatically be labeled diabetic neuropathy without considering the person’s wider health history. [33]
Mouth care is part of diabetes care. Gum disease, dry mouth and oral thrush may be more troublesome, and gum disease can make glucose harder to manage. Brush twice daily, clean between teeth and keep dental appointments. Tell the dentist that you have diabetes and describe bleeding gums, soreness, persistent dryness or white patches. A mouth problem may affect eating and therefore complicate the rest of the care plan. Seek treatment rather than relying on mouthwash alone, and ask how to coordinate dental procedures with your usual meals and medicines. [31]
Hearing difficulties can be easy to overlook when other checks take priority. Diabetes can be associated with hearing loss, so mention trouble following conversations, frequently asking people to repeat themselves or needing a louder television. An audiologist can assess hearing and discuss support. Ask how hearing checks fit into your care schedule, and protect your ears from loud noise. Good communication also matters during medical visits: request clearer written instructions or other accommodations if spoken advice is difficult to hear, rather than leaving with uncertainty about your treatment. [39]
Make care fit everyday life
Diabetes distress is the frustration or exhaustion that can accompany constant decisions about a long-term condition. It can coexist with depression or anxiety, but it is not a personal weakness. Tell the care team if worry, low mood or the workload is interfering with daily life. An educator can help simplify practical problems, and mental health support can address emotional difficulties. Choose one or two manageable goals instead of trying to fix everything at once. Family members can help most by asking what support is wanted rather than policing food or numbers. [34]
Smoking adds to the risk of blood-vessel damage and diabetes complications. Stopping can improve health, but nicotine dependence often requires support rather than willpower alone. Tell your clinician what you currently use and ask about counseling and appropriate cessation treatment. A previous unsuccessful attempt can provide information about difficult moments and what help was missing. If glucose patterns change while you are quitting, share the readings with your care team. The aim is to support both tobacco cessation and safe diabetes management through the transition. [40]
Travel can change meal timing, activity, temperature and access to supplies. Before leaving, ask how to handle time-zone changes and prescription refills, and keep medicines and monitoring equipment accessible in hand luggage. Carry extra supplies and a source of fast-acting carbohydrate if you are at risk of lows. Follow the manufacturer’s temperature instructions; insulin and devices can be harmed by excessive heat or cold. Check device-specific airport screening guidance rather than assuming all equipment can go through the same scanner. Planning these details makes disruptions easier to handle. [35]
If you plan a pregnancy, arrange preconception care because glucose levels and medicines need review before the earliest weeks. Contact your care team promptly if you become pregnant unexpectedly. Pregnancy changes glucose targets, treatment choices and monitoring needs, and some medicines need replacement. Type 2 diabetes present before pregnancy is different from gestational diabetes first developing during pregnancy. Do not use the general adult targets in this guide as pregnancy targets or stop all treatment on your own. A diabetes and maternity team can coordinate the safer plan. [36]
Children and teenagers can also develop type 2 diabetes, but adult weight-loss instructions should not simply be transferred to a growing child. Growth, puberty and family routines matter. Ask the child’s clinician about testing when there are symptoms or relevant risk factors. Family-wide changes, such as shared meals and enjoyable movement, can support health without singling a child out or making body size a moral issue. This adult guide is background information; a child with suspected or diagnosed diabetes needs an age-appropriate clinical assessment and care plan. [37]
The cost of medicines, strips, sensors, appointments and food can make an otherwise sensible plan impossible to follow. Bring that up early, including which item is unaffordable and when you will run out. Depending on your location and eligibility, insurance support, community clinics, assistance programs or different prescribed options may help. Ask about the total ongoing cost rather than just the price of a starter device. Skipping treatment to stretch supplies can be unsafe; the team needs to know about the access problem to help address it. [42]
Remission and continuing follow-up
Some people with type 2 diabetes achieve remission. The international consensus definition usually means A1C below 6.5% for at least three months without usual glucose-lowering medication. Remission is not a cure: glucose can rise again and earlier exposure to high glucose can still matter. Ongoing glucose assessment and complication checks remain important. Do not stop medicine merely to see whether you qualify, particularly when it is providing other health benefits. Discuss the meaning and monitoring of remission with the clinician, including alternatives when A1C is unreliable. [38]
Keep a written record of what is due next: glucose review, kidney tests, eye and foot assessment, dental care and other preventive care relevant to you. Follow-up should also cover medication difficulties and changes in health or circumstances. Bring your medicine list, available glucose records and two or three priority questions to the appointment. Ask who will communicate results and what to do if you do not hear back. A care schedule is most useful when it names the next action and responsible service, rather than simply saying “review annually.” [41]
Frequently asked questions
Can I have type 2 diabetes without symptoms?
Yes. Type 2 diabetes can develop gradually with few or no noticeable symptoms. That is why risk-based testing matters. A person should not wait to feel unwell before discussing screening, and a clinician should interpret an abnormal result rather than relying on a home reading alone. [1]
Does a good A1C mean I can stop checking for low glucose?
No. A1C is an average and cannot show every glucose swing. Someone can have an apparently satisfactory average while experiencing clinically important lows. Follow the monitoring plan appropriate to your medicines and discuss unexpected readings or symptoms with the care team. [7]
Do people with diabetes have to avoid all fruit?
No. Fruit can be part of a diabetes eating plan. Portion size and the overall meal pattern matter, and whole fruit can contribute fiber and nutrients. A dietitian can help you fit preferred foods into your plan rather than relying on a universal banned-food list. [17]
Is remission the same as permanent reversal?
No. Remission describes a sustained improvement that meets defined criteria; it does not guarantee that diabetes will never return. Continue the agreed monitoring and health checks even when glucose is below the diagnostic threshold. Medicines should only be changed with the prescribing team’s guidance. [38]
The page’s original video is retained below as supplementary material. Its full content has not been independently reviewed for this update and may contain older guidance. Use the written, source-checked article and your clinical team’s advice for current decisions.





