

This guide provides general education, not a diagnosis or an individual treatment plan. A clinician or pharmacist can help identify the cause of a rash and choose appropriate care. Editorial source-checking is not a licensed clinical review.
What ringworm symptoms can look like
Ringworm is a fungal infection that can affect skin, hair and nails. The name comes from the circular rash it sometimes produces; there is no worm under the skin. An itchy, scaly patch with a more noticeable outer edge is a common presentation, but the appearance changes with the body site. Athlete’s foot and jock itch belong to the same family of infections. A scalp patch with hair loss or a thickened, brittle nail can therefore need consideration even when there is no visible ring. [1]
The most useful questions are where the change started, how it has developed, whether hair or nails are involved, and what has already been applied to it. This guide explains the patterns worth noticing, reasons that a similar-looking rash may have another cause, and when to get help. Use these descriptions to prepare for an assessment rather than to match your skin to a photograph. When asking for help, describe what you can actually see and feel before giving the rash a name.
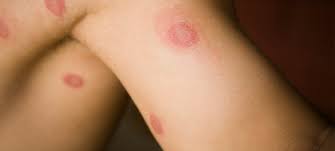
Color, shape and texture all matter
On lighter skin, ringworm patches often look pink or red. On darker skin, they can look brown or gray, so a search for bright redness alone may miss an important change. The outer border may be raised and flaky while the center looks less affected. Itching can be intense, although the appearance and discomfort vary between body sites. Pay attention to the outline, scaling and change from your usual skin color together. No single color, and no single photograph, represents everyone’s presentation. [2]
On the trunk or limbs, tinea corporis may begin as one round patch and enlarge outward. Several patches can appear and join into irregular overlapping outlines. The advancing edge can contain small bumps or pustules rather than being a perfectly smooth circle. The distribution is often uneven, with one side or area more affected than another. This helps explain why an early patch and a later, larger eruption may look different. A neat empty center is a possible feature, not a requirement that every patch must satisfy. [5]
Color can also remain after inflammation has settled. Postinflammatory hyperpigmentation is a darker mark left at the site of a previous skin problem, including infection. It can affect any skin tone but is often more noticeable and longer-lasting in darker skin. A remaining dark area therefore needs to be considered separately from continuing symptoms. Tell the clinician whether the mark is still changing or whether the main concern is its color. Pigment alone is not a reliable home test of whether a previous infection has cleared. [27]
Symptoms on different parts of the body
Scalp: scaling, broken hairs and bald patches
Scalp ringworm, or tinea capitis, does not always look like a ring on bare skin. It can produce scaly areas with hair loss, hairs broken close to the scalp that look like black dots, or a grayish patch. Some cases resemble widespread dandruff, with little obvious hair loss. Inflamed forms can develop pustules and a tender, swollen area. A child with new scalp scaling and broken hair should be assessed, and adults can also be affected. Mention changes in the hair itself rather than reporting only an itchy scalp. [6]
Beard: inflamed follicles and crusting
Tinea barbae involves the beard or moustache area and can affect coarse facial hairs. It often produces lumpy inflammation, pustules and crust around the hairs; affected hairs may loosen easily. The degree of itching or pain does not always match how inflamed the area looks. Animal exposure can be relevant, particularly contact with farm animals. A clinician may collect hairs and skin scrapings for microscopy and culture. Because hair involvement often calls for oral treatment, a suspected beard infection deserves assessment rather than repeated experiments with an ordinary skin cream. [7]
Face: an uneven patch that may resemble dermatitis
Ringworm on facial skin outside the beard area is called tinea faciei. It can cause round or oval scaly patches, sometimes with a quieter-looking center, and may affect one side more than the other. Some eruptions spread quickly; others extend slowly and are only mildly inflamed. Eczema, rosacea and other facial conditions can look similar, making an examination especially useful. Tell the clinician about rashes on the feet, groin or nails as well, because another infected site may be relevant to the facial problem. [11]
Feet: toe-web peeling, sole scale or blisters
Athlete’s foot, or tinea pedis, has several patterns. One produces itchy peeling or damaged skin between the toes, often near the smaller toes. Another causes broader scaling over the sole and sides, sometimes called the moccasin pattern because of its distribution. A third produces blisters, especially along the inner foot. One foot may be more affected than the other. Foot eczema and reactions to footwear can resemble these changes. Describing the exact location is more helpful than simply saying that the feet are dry. [8]
Hands: persistent peeling on one palm
Tinea manuum may cause a slowly enlarging area of dryness, peeling and mild itch on one palm. Skin lines can become more prominent because scale collects within them. Sometimes there are blisters at the edges of the fingers or palm, and a ring-shaped patch can occur on the back of the hand. The familiar clinical pattern of one hand and both feet being involved is a clue, not a diagnosis. Hand dermatitis remains another possibility, and sampling can help distinguish the causes when the pattern is unclear. [10]
Groin: an itchy border around the upper inner thigh
Tinea cruris, commonly called jock itch, often begins in a groin crease and spreads onto the adjoining inner thigh. It can be uneven on the two sides, with a raised, scaly advancing edge. The buttocks or lower abdomen may also be involved. Typical tinea cruris usually spares the penis, scrotum and vulva, but this is not a rule for identifying every genital rash. Mention exactly which structures are affected. Infection on the feet or nails can also be relevant because fungi can be transferred between body sites. [9]
Nails: thickening, discoloration and crumbling
Fungal nail infection commonly starts near an edge and can spread across the nail. A toenail or fingernail may become white or yellow, thicker, brittle or crumbly, and sometimes lift away from the skin beneath it. Discomfort can occur when the surrounding area becomes swollen or painful. Nail changes deserve their own assessment, especially if several nails become involved or a person has diabetes or a weakened immune system. A skin-rash treatment should not automatically be assumed suitable for a changed nail. [14] [30]
| Area | Useful observation | Why mention it |
|---|---|---|
| Scalp | Scale with broken hairs or a new bald patch | Scalp infection can have subtle hair loss or resemble dandruff; hair changes help direct the assessment. [6] |
| Beard | Crusting or pustules around loose hairs | Hair-follicle involvement changes the assessment and often the treatment approach. [7] |
| Feet | Peeling between toes versus scale over a whole sole | Both patterns can occur in athlete’s foot, and other foot conditions can look similar. [8] |
| Groin | Which crease, thigh or genital skin is affected | The precise distribution matters; the everyday label “jock itch” does not explain every rash in this area. [9] |
| Hands | One palm affected, with or without foot symptoms | Uneven hand involvement and infection elsewhere can be useful clues when distinguishing tinea from dermatitis. [10] |
What else can look like ringworm?
Discoid, or nummular, eczema can produce round, intensely itchy patches that are swollen, crusted, cracked or flaky. The center sometimes clears, leaving a ring-like outline. Dry skin between patches or a history of similar flares can be useful information, but neither settles the diagnosis by itself. The overlap matters because treatments used for eczema differ from antifungal treatment. If a circular patch keeps returning or a suggested treatment is failing, ask whether the diagnosis needs checking instead of choosing another product based only on the shape. [16]
Pityriasis rosea often starts with one larger scaly “herald patch,” followed later by multiple smaller spots, commonly across the chest and back. The initial patch can resemble ringworm. The wider eruption often appears on both sides of the body, and its color varies with skin tone. Tell the clinician which patch appeared first and how the rest followed. A new rash during pregnancy needs prompt advice from the maternity team or another clinician rather than an assumption that it is harmless ringworm or pityriasis rosea. [17]
Psoriasis can cause dry, sore, itchy patches with conspicuous scale. It may affect the scalp, elbows and knees, but also skin folds and nails. Nail pitting and a history of recurring patches elsewhere can help a clinician understand the whole picture. Psoriasis itself is not contagious. This is another reason to avoid deciding that any scaly patch must be an infection. If you already have psoriasis, describe what is new or different about the current rash rather than assuming every future skin change has the same cause. [18]
Contact dermatitis follows irritation or an allergic response to something touching the skin. It can cause itching, cracking, dryness and blisters, particularly on the hands or face. A new cosmetic, cleanser, detergent or repeated wet work may provide a useful lead. The reaction can appear hours or days after exposure, so bring a short timeline rather than only the name of the last product used. Continuing to add unfamiliar creams to an unexplained rash can make that timeline harder to reconstruct. [19]
An expanding round or oval rash after possible tick exposure deserves prompt medical assessment for Lyme disease. That rash is often not itchy or hot, and it does not always form the classic target shape. A tick bite may go unnoticed. Mention recent time in woodland or grassy areas, along with fever, aches, headache or unusual tiredness. Lyme disease is a bacterial infection with different treatment needs. Do not wait for a perfect bullseye appearance, or for an antifungal trial to finish, before asking about that possibility. [35]
How clinicians check the diagnosis
An examination can raise suspicion for ringworm, but appearance alone can be unreliable. Current professional guidance recommends in-office testing when feasible, such as examining a potassium hydroxide preparation of a skin sample. Testing is particularly important before committing to treatment for suspected fungal nail infection, because nail injury and psoriasis can look similar. Also, “fungal nail infection” is broader than ringworm: some nail infections involve yeasts or other molds. A precise diagnosis helps avoid treating the wrong problem or using a medicine that does not fit the cause. [24]
For a superficial infection, the sample may be skin scrapings or a nail clipping. A fungal culture grows organisms from the sample so the laboratory can investigate what is present. A clinician may request it when the symptoms are not improving or when knowing the organism would guide care. Culture is different from simply looking at a sample under a microscope, and the results may arrive at different times. Ask what was ordered, how you will receive the result, and whether the initial treatment plan might change afterward. [15]
A negative test does not always settle the question. Fungal material can be difficult to find, and sample collection or earlier antifungal use can affect culture results. Clinicians may sample an active edge, hair or material beneath a nail, depending on the site. Some services use molecular tests as well. Tell the clinician everything already applied or taken, including dates if possible. Do not scrape your own skin or pull hairs to produce a specimen; ask the service what preparation, if any, it needs. [32]
Before leaving the appointment, ask what the working diagnosis is and what finding would prompt a different plan. If a test is pending, write down who is responsible for reviewing it. If you cannot follow the proposed routine because of work, caring responsibilities, cost or difficulty reaching the affected area, say so at the start. A useful plan should include understandable instructions, a way to ask about problems, and a clear point for reviewing whether the approach has helped.
Why steroid creams can disguise ringworm
Tinea incognito is ringworm whose appearance has been altered by treatment that suppresses inflammation, most often a steroid cream. The itch may initially feel quieter even as the infection extends. Compared with a typical untreated patch, the border can become less raised and less scaly, while the eruption becomes broader or more pustular. This can lead to a cycle of temporary relief followed by worsening. Tell the clinician if a rash changed after an eczema cream, an anti-itch product or a combination cream, and bring the packaging. [12]
Do not start a steroid-containing cream on a rash that might be ringworm without appropriate clinical advice. “Antifungal plus steroid” does not make a product a safer all-purpose choice for an uncertain rash. A pharmacist can identify the active ingredients if the label is confusing. If a prescribed cream is already in use, contact the prescriber about the new concern and explain what changed, rather than repeatedly increasing the amount or extending the course yourself. [24]
A separate rash does not always mean the fungus has spread
An inflammatory fungal infection can sometimes trigger a dermatophytide, also called an id reaction: an itchy eruption at a different body site. For example, blistering on the hands can accompany a significant foot infection. The secondary eruption is an inflammatory response, and fungus is not grown from that secondary rash. This is a clinician’s distinction, not something to decide from a photograph. Report new rashes during treatment so that infection, irritation, medication reactions and an id reaction can be considered, each with its own management needs. [28] [26]
Why treatment depends on the site
For a suspected limited skin infection, a pharmacist can advise whether an appropriate antifungal product is reasonable or whether medical assessment is needed. The medicine and its form depend on where the rash is. Follow the specific product or prescription instructions, including how long to continue, even if the visible rash improves sooner. If the recommended treatment has not helped, arrange review. Scalp symptoms and a weakened immune system are additional reasons to involve a clinician rather than repeatedly trying pharmacy products on your own. [3]
Scalp ringworm generally requires a prescription antifungal taken by mouth. A medicated shampoo may be added to reduce spread, but it is not a substitute for the oral treatment needed to address infected hair. The organism identified, age and individual circumstances help determine the plan. A clinician may begin treatment before the culture result if suspicion is strong, then adjust it when results arrive. Close contacts may also need checking to help prevent reinfection; this should be coordinated with the treating service. [23]
Nail treatment has different practical demands. A dermatologist considers how much nail is involved, the fungus, other health conditions and medicines before choosing a topical nail medicine, oral treatment or another approach. Nails grow slowly, so the goal of controlling infection and the goal of seeing a normal-looking nail are not identical milestones. Ask what improvement should look like in your situation and how follow-up will be handled. Do not judge a nail treatment by whether it produces the rapid visual change expected from a small skin patch. [30]
Antifungal medicines are not interchangeable. Before using one, discuss allergies, other medicines, pregnancy or breastfeeding and relevant medical conditions with a pharmacist or prescriber. Children may need different products or instructions from adults. Local itching or burning can occur with some treatments, while oral medicines have their own side effects and interactions. Read the patient leaflet and ask which reactions require stopping the product or getting help. Having used an antifungal safely in the past does not establish that every new formulation or course is suitable. [26]
When comparing treatment information, separate the body site, the formulation and the instructions for that exact medicine. Our related explanation of how ringworm treatment differs by body site provides further context. Bring any conflicting instructions to a pharmacist or clinician rather than combining parts of several routines. In particular, ask what to do if symptoms improve early, a dose is missed, or the product causes discomfort; those are useful questions to settle before starting.
When to seek prompt or emergency care
Seek urgent assessment for skin that becomes hot, painful and swollen. These can be features of cellulitis, a bacterial infection requiring different treatment. Redness may be harder to see on darker skin, so warmth, pain and swelling matter. Get emergency help if an apparent skin infection is accompanied by confusion, fainting, fast breathing, a very fast heartbeat, cold clammy skin or severe systemic illness. Do not assume that a previous ringworm diagnosis explains a sudden deterioration. [20]
A soft, boggy, inflamed scalp lump with pus and loose hairs may be a kerion, a strong inflammatory response to fungal infection. Fever or swollen nearby glands can occur. Prompt assessment matters because some cases can leave permanent hair loss, particularly if prolonged. Kerion can be mistaken for a bacterial problem, and bacterial infection can also occur alongside it. The clinician may need both fungal sampling and a bacterial swab. Ordinary antifungal cream alone does not adequately treat fungal involvement deep in the hair follicle. [13]
Seek medical advice for suspected athlete’s foot if you have diabetes, a weakened immune system, substantial pain, spread to other areas, or no improvement with pharmacy treatment. A hot, painful foot or leg needs more urgent assessment for a potentially more serious infection. These circumstances change the threshold for getting help; they do not mean that every foot rash will become dangerous. Tell the clinician about your health conditions at the first contact so the urgency and next steps can be judged appropriately. [29]
After any new medicine, sudden swelling of the lips, mouth, tongue or throat, breathing difficulty, collapse or marked confusion can signal a severe allergic reaction. Call your local emergency number immediately. If you have a prescribed adrenaline auto-injector for anaphylaxis, use it according to its instructions and seek emergency help. Do not wait to see whether the skin rash changes or whether an antifungal is starting to work. These are emergency symptoms regardless of the original reason for taking the medicine. [31]
Transmission and practical prevention
Ringworm can pass through contact with an infected person or animal and through contaminated items or surfaces, including combs, clothing and communal shower areas. Warm, moist conditions support the fungi, and sweating or small skin injuries can contribute. A household exposure is therefore relevant even when you cannot identify one particular encounter that caused the infection. When discussing possible sources, focus on shared items and routines rather than blame. People of all ages can develop ringworm, and finding a possible route is mainly useful for preventing another episode. [4]
Keep skin clean and dry, change socks and underwear daily, and avoid sharing towels or personal sports equipment. Wear protective footwear in communal showers and changing areas, and wash hands after touching pets. Avoid direct skin contact, including sexual contact, with a suspected or known infected area. These measures work alongside appropriate treatment. They do not provide a fixed date when every infection becomes noncontagious, and a small-looking patch can still be a reason to ask about protecting close contacts. [1]
If a cat has patchy hair loss, broken hairs, scaling or crusting, a veterinarian can check whether ringworm or another skin disorder is responsible. Infected cats can pass the fungus to people, and some can carry it without the obvious picture owners expect. Let the veterinarian know if a person in the home has a confirmed infection. The animal needs its own assessment and treatment plan; a human product or an online photograph should not become a substitute for veterinary advice. [33]
Cleaning and disinfecting are different steps. Cleaning removes dirt and germs; disinfectants are chemicals used to kill germs on suitable surfaces. When cleaning pet items, follow the product label, including any pre-cleaning, contact-time, rinsing and drying instructions, and keep animals away during use. Never mix bleach with other cleaners. Ask the veterinarian which measures fit a confirmed pet infection and the items involved. A safe, specific cleaning plan is preferable to repeatedly using stronger mixtures or exposing people and animals to unnecessary fumes. [25]
For school, childcare, work or sport, ask the treating service which return rules apply to that setting and body site. Also ask the school, coach or workplace for its written requirements so that advice can be reconciled before returning. Record whether a clearance note, treatment record or particular covering is requested. Keep the discussion factual: which area is affected, what care has been arranged, and what the relevant policy requires. Avoid using a general internet timeline as a substitute for that decision.
What persistent symptoms and resistant ringworm mean
Some ringworm infections are harder to treat because the fungus is resistant to a medicine. Trichophyton indotineae is one important example. A published investigation of the first reported United States cases described extensive itchy eruptions that did not improve with oral terbinafine and required further evaluation. One patient had no recent international travel, showing why travel history alone cannot exclude the possibility. This report does not mean that every persistent rash is resistant ringworm; it illustrates why failure of a well-chosen treatment warrants reassessment rather than automatic repetition. [21]
Identifying T. indotineae can require specialized laboratory work. Routine culture may not distinguish it from certain related fungi, so a dermatologist may seek testing through a specialist laboratory or public health service. A routine skin test cannot provide every detail about the species or drug resistance. If an infection is extensive, recurrent or unusually difficult to treat, ask whether the diagnosis, organism and previous medicines need review. A clinician can interpret those findings together instead of relying on an internet label such as “super ringworm.” [34]
Another emerging fungus, Trichophyton mentagrophytes genotype VII, or TMVII, can spread through sexual contact and affect the genitals, buttocks, face or other skin. It is distinct from T. indotineae; emerging does not automatically mean resistant to the same medicines. A New York City investigation documented infections that responded to antifungal treatment. Persistent or painful genital lesions deserve assessment, including consideration of other causes. Explain relevant contact and travel history privately and without assumptions about anyone’s identity: the useful information is the exposure and symptoms, not a stereotype. [22]
Make follow-up easier to act on
Bring a brief record rather than a long list of possible diagnoses. Write down the first affected area, later changes, and the names of products used. If you have photographs, keep their dates and explain whether lighting or camera settings changed between them. Include the concern that matters most to you, such as interrupted sleep, difficulty walking, hair loss or uncertainty about close contact. That makes it easier to discuss both the medical question and the practical problem you want the appointment to resolve.
| Question | What to clarify |
|---|---|
| What are we treating? | Ask for the working diagnosis, whether a sample is needed, and who will tell you about any pending result. Write the answer in everyday language you can refer to later. |
| How should I use it? | Confirm the product name, the exact area it is intended for, the instructions and the planned duration. Say if the routine is impractical rather than quietly substituting something else. |
| When should I check back? | Ask what change should prompt an earlier call and when to arrange review if the expected improvement does not happen. Confirm how to contact the service between appointments. |
| What about other people? | Ask whether household members, close contacts, a school or a sports setting need advice. If a pet is being evaluated, bring the veterinary information you have rather than assuming the diagnoses match. |
Frequently asked questions about ringworm symptoms
Does ringworm always form a complete ring?
No. Body ringworm can develop overlapping or irregular patches, and treatments that suppress inflammation can change its appearance. The textbook outline is useful for understanding one pattern, but it is not a checklist that all infections must pass. A spreading scaly patch still deserves assessment when it is incomplete, uneven or lacks a clear center. [5]
Can ringworm happen without a very itchy rash?
Yes. Beard ringworm may not be particularly itchy or painful even when the affected area looks very inflamed. The intensity of itch is therefore not a reliable measure of how much attention the problem needs. Describe crusting around hairs, loose hairs and new lumps as well as discomfort, and arrange assessment rather than waiting for severe itching. [7]
Can I treat a child’s scalp with shampoo alone?
A suspected scalp infection needs clinical assessment. Shampoo can help reduce spread, but treatment usually also requires a prescription medicine taken by mouth. Ask how the child should take that medicine, how results will be reviewed and whether close contacts need checking. Do not apply the instructions for an adult foot product to a child’s scalp. [23]
Does a darker mark after treatment mean ringworm remains?
Not necessarily. Skin inflammation can leave postinflammatory pigmentation after the original problem has healed. A color change is different from a clearly expanding, newly symptomatic patch. If you cannot tell which is happening, arrange reassessment rather than extending treatment until every trace of color disappears. Ask about the remaining mark as a separate concern. [27]
What should I do if an antifungal has not helped?
Return to a pharmacist or clinician for review and bring the product details and the way you actually used it. The NHS recommends medical assessment when ringworm has not improved after a pharmacist-recommended antifungal. Mention any scalp involvement and relevant immune-system conditions. A review can establish the next step more safely than repeatedly switching products without checking the cause. [3]
The original older video is retained below for context. Its full medical content has not been independently reviewed for this update; use the current written guidance and linked sources rather than relying on the video for diagnosis or treatment instructions.





