

Sources checked on 9 October 2026. This guide explains how prostatitis is assessed, how care differs by type, and what patients and families can discuss at follow-up appointments.
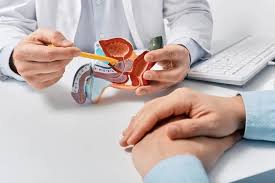
Prostatitis Treatment Starts With the Type
Prostatitis treatment depends on what is causing the symptoms. Acute bacterial prostatitis is a sudden infection, while chronic bacterial prostatitis involves persistent or recurring bacterial infection. Chronic prostatitis/chronic pelvic pain syndrome, shortened to CP/CPPS, describes ongoing pelvic pain without the same evidence of bacterial infection. A fourth category, asymptomatic inflammatory prostatitis, is found during other investigations, causes no symptoms, and generally needs no treatment. These categories explain why one person’s antibiotic prescription cannot serve as another person’s plan. Similar discomfort can arise through different processes, requiring clinical assessment before treatment. [3]
When Symptoms Need Urgent Assessment
New pelvic or urinary pain with fever, chills, or significant illness needs prompt clinical assessment. Suspected acute bacterial prostatitis requires clinician-selected antibiotics. A urine culture should be collected before antibiotics when feasible, without delaying urgent treatment. Inability to pass urine needs urgent medical care because retention is a recognized complication. Worsening symptoms require reassessment immediately. NICE recommends hospital referral when acute symptoms are not improving within 48 hours of starting antibiotics, or when sepsis, retention, or an abscess is suspected. A clinician may need to investigate resistant bacteria or another diagnosis. Recovery can take several weeks, but deterioration is not an expected milestone. [1]
Recognize a Possible Infection Emergency
An infection can trigger sepsis, a dangerous reaction affecting the whole body. Warning signs include new confusion, shortness of breath, clammy skin, an unusually fast heartbeat or weak pulse, extreme discomfort, and fever or feeling very cold. Someone with a suspected infection who becomes very unwell needs emergency medical help. Do not wait for every sign or an online checklist to confirm the cause. Urinary infections can lead to sepsis, and prompt treatment matters because organ damage can develop quickly. [2]
How Clinicians Check for Infection
Urine testing helps distinguish bacterial prostatitis from other explanations for pelvic pain. A midstream urine culture identifies bacteria and can guide antibiotic selection; blood tests and cultures may be needed during an acute illness. For chronic bacterial prostatitis, specialists sometimes use additional localization tests. Prostate massage must not be performed during acute bacterial prostatitis because it can spread bacteria into the bloodstream. PSA can rise during active prostatitis and should not be used to diagnose the infection; interpretation of a raised result requires clinical context. Imaging is reserved for questions such as a suspected abscess or obstruction. Severe infection may require intravenous antibiotics and treatment of impaired drainage. [4]
When STI Testing Is Relevant
Burning urination and genital discomfort can also come from urethritis, which may have an infectious or noninfectious cause. A clinician may recommend tests for gonorrhea, chlamydia, or other organisms when the history and examination suggest them. Choosing appropriate tests avoids treating every episode as a prostate infection. Persistent symptoms deserve reassessment: symptoms alone, without evidence of urethral inflammation, do not justify automatic retreatment. The CDC also advises considering CP/CPPS in men with persistent pelvic symptoms and referring ongoing pain to appropriate urological expertise. [5]
Why Culture Results Need Follow-Up
The first antibiotic decision during an acute illness may need revision when the laboratory result returns. An observational study of 410 people with acute bacterial prostatitis found that inadequate definitive antibiotic treatment was associated with relapse. Resistance was frequent in that hospital population. This supports checking that the final prescription matches the organism’s susceptibility results. It does not establish a preferred drug for everyone: treatment was not randomly assigned, and participants’ age, other illnesses, and local resistance patterns limit how broadly the comparisons apply. [6]
Chronic Bacterial Prostatitis Takes Planning
Confirmed chronic bacterial prostatitis needs an antibiotic strategy that accounts for the organism and whether the medicine reaches prostate tissue. A Cochrane review found broadly comparable results among several fluoroquinolones but could not settle the best treatment duration. Evidence for some alternatives was inconclusive. Recurring infection therefore needs clinical review, not a borrowed prescription. These findings concern bacterial disease and cannot be transferred directly to CP/CPPS. The review’s evidence search is older, making current resistance information and safety guidance essential to today’s decisions. [7]
Resistant Infection May Need Specialist Options
A prospective study followed 44 patients given fosfomycin for confirmed chronic bacterial prostatitis, often involving organisms resistant to other drugs. Many improved, although some relapsed and diarrhea occurred. This illustrates why specialists may consider less familiar options after reviewing laboratory findings and previous treatment problems. It was not a randomized comparison, so it cannot show that fosfomycin is superior to established alternatives. These results also do not support experimenting with this medicine or using it for pelvic pain without proven bacterial infection. [8]
Antibiotic Benefits and Serious Side Effects
Fluoroquinolone antibiotics can be useful for certain bacterial infections, but their risks deserve an explicit conversation. FDA warnings describe potentially disabling, lasting problems involving tendons, muscles, joints, nerves, and the central nervous system. These effects may occur together. New tendon pain, unusual weakness, tingling, numbness, or confusion during treatment warrants immediate contact with a healthcare professional. The prescriber must balance the infection being treated against the person’s risks and available alternatives. A treatment’s familiarity does not remove the need to discuss its safety, and trial reports of few adverse events cannot rule out rare serious reactions. [9]
Current Restrictions Shape Prescribing
In the United Kingdom, the MHRA strengthened restrictions in 2024: systemic fluoroquinolones should be used only when other commonly recommended antibiotics are inappropriate. Reasons can include resistance, a contraindication, troublesome previous side effects, or failure of another suitable treatment. The agency specifically includes nonbacterial chronic prostatitis among conditions for which these medicines should not be prescribed. Previous serious reactions and other risk factors matter when choosing a drug. These restrictions make the diagnostic distinction practical: identifying bacterial infection affects both the potential benefit and whether exposure to this antibiotic class can be justified. [10]
A Targeted Plan for CP/CPPS
Under the AUA’s 2025 guideline, alpha blockers should be offered when CP/CPPS includes voiding symptoms. Clinicians may consider daily tadalafil with or without erectile dysfunction, a conditional recommendation rather than guaranteed pain relief. Pain medicines require individualized benefit-risk discussion. The guideline supports discussing low-intensity shockwave therapy and permits acupuncture. Psychological support should accompany appropriate medical assessment and never imply that symptoms are imaginary. Repeated antibiotics should be avoided when cultures and STI tests are negative. Prostate surgery should not be used solely for pelvic pain; coexisting obstruction or cancer may justify a separate discussion. Alpha blockers may cause postural dizziness. Tadalafil must not be combined with nitrates. [11]
Why Several Treatments May Be Combined
CP/CPPS can involve urinary symptoms, muscle tenderness, broader pain problems, and emotional strain. In a prospective study, 100 patients received treatments selected through UPOINT, a framework organizing different clinical features. Symptoms and quality of life improved over follow-up. Without a randomized control group, however, the study cannot prove the framework caused improvement or identify the best combination. Its practical contribution is defining the problems that need attention. A plan for prominent muscle tenderness may therefore look different from one centered on difficult urination. [12]
Pelvic Floor Care Starts With Assessment
Pelvic floor treatment is not automatically a strengthening program. The EAU describes addressing overactive muscles and painful muscle points as part of chronic pelvic pain care, with specialist physiotherapists helping patients learn relaxation and restore comfortable movement. That makes a blanket instruction to perform repeated Kegel contractions inappropriate: the treatment should reflect what the examination finds. Chronic pain also involves biological, psychological, and social influences, so distress and everyday functioning deserve attention alongside physical symptoms. This approach recognizes that the pain is real. Physiotherapy and psychological care can be components of a coordinated plan, with ongoing review of what is helping. [13]
What Manual Therapy Evidence Shows
Manual pelvic floor therapy has encouraging evidence, but a frequently cited trial needs careful interpretation. The study compared targeted myofascial therapy with general massage in a small group containing both men and women with different urological pain syndromes. Overall response favored myofascial treatment. In the small CP/CPPS subgroup alone, however, the difference was not statistically significant. This was primarily a feasibility study, rather than definitive proof of a universal treatment effect. The findings support further research and an individualized discussion; they do not establish that every person labeled with prostatitis has the same muscle problem. [14]
Biofeedback Helps Explain Muscle Control
Biofeedback uses information about muscle activity to help someone recognize how their pelvic floor works. In a small study of men with CP/CPPS, pelvic floor retraining and biofeedback were associated with lower symptom scores and resting muscle tone. Results were reported for 31 of 33 participants. Without a randomized comparison, the study cannot separate treatment effects from other influences. It illustrates why a therapist may emphasize coordination and relaxation instead of stronger contractions. Assessment determines whether that approach fits the person’s findings. [15]
Movement Can Be Part of Rehabilitation
A randomized study compared aerobic activity with stretching and movement exercises in men whose CP/CPPS had not responded satisfactorily to conventional treatment. The aerobic group improved more in several symptom and quality-of-life measures. Participants were screened for their ability to undertake moderate exercise, so this is not a fixed exercise prescription for everyone with pelvic pain. The trial was relatively small, with limited follow-up. Rehabilitation can extend beyond medication, while activity choice, pace, and tolerability belong within an individual care plan. [16]
Support for the Burden of Pain
Psychological treatment can address the strain of persistent symptoms without declaring the pain imaginary. A small feasibility program for men with difficult CP/CPPS explored cognitive and behavioral skills involving coping, activity, and distressing pain thoughts. Eleven men completed it, and some measures of disability and symptom impact improved. There was no control group, and complete final symptom questionnaires were available for only eight participants. This offers preliminary support rather than a guaranteed outcome. Such care addresses a painful experience alongside assessment and treatment of physical contributors. [17]
Measure More Than Pain Intensity
Progress is easier to discuss when pain, urinary symptoms, and daily impact are recorded separately. The NIH Chronic Prostatitis Symptom Index was developed with patient input to measure these domains consistently. Its nine items capture several aspects of the experience. The instrument tracks symptoms; it does not identify bacteria or replace examination. A lower total score can reflect improvement in one domain while another remains troublesome. Asking which part changed makes follow-up more precise and keeps a headline improvement from obscuring an unresolved problem. [18]
Pain Improvement Does Not Prove Infection
Feeling better during antibiotics does not by itself prove that they treated an infection. A placebo-controlled study of 80 men with CP/CPPS and no infection localized to the prostate found improvement in both groups, without a significant advantage for levofloxacin. Most participants had symptoms for years, and the trial was small, so it cannot answer every question about newly presenting symptoms. It shows why change over time cannot confirm a bacterial cause. Laboratory evidence, the clinical picture, and reassessment help clinicians interpret a treatment response. [19]
Antibiotics and Persistent Symptoms
A trial of 196 men compared ciprofloxacin, tamsulosin, their combination, and placebo for persistent CP/CPPS. Participants had substantial previous treatment and symptoms lasting an average of more than six years. Neither drug produced a significant advantage on the main symptom measure, and secondary outcomes were similarly unconvincing. The result is especially relevant to interpreting repeated treatment attempts in longstanding illness. Its limits matter: the brief study did not establish the response in newly diagnosed, minimally treated patients or assess durable recovery. It also did not study confirmed bacterial prostatitis as the target condition. [20]
Alpha Blockers and Mixed Trial Results
Alfuzosin was tested in a multicenter trial involving 272 men diagnosed with CP/CPPS within the previous two years who had never used an alpha blocker. The drug and placebo groups were equally likely to reach the study’s main threshold for symptom improvement. Overall patient ratings also showed no meaningful advantage. This challenges the assumption that an alpha blocker necessarily helps when introduced relatively early. However, the findings concern alfuzosin in this defined population and short follow-up period; they do not settle whether every medication in the class has identical effects. [21]
Silodosin and Exploratory Evidence
A phase II trial assessed silodosin in 151 men with moderate to severe CP/CPPS who had not previously received an alpha blocker for the condition. One active treatment group showed greater improvement than placebo in total symptoms, urinary complaints, quality of life, and overall patient ratings. The other active group did not provide additional benefit. The findings suggest possible benefit within the selected study population, without establishing that all alpha blockers produce a uniform effect. The researchers explicitly called for further confirmation before treating this exploratory finding as settled evidence. [22]
Tadalafil and Different Symptom Domains
A placebo-controlled trial enrolled 140 men aged 45 or younger who had both moderate to severe CP/CPPS and erectile dysfunction. Tadalafil produced better total symptom, urinary, and quality-of-life scores than placebo. Pain scores improved relative to the treatment group’s own starting point, but did not improve significantly compared with placebo. That distinction prevents an overall symptom result from being mistaken for established pain relief. Only 115 participants remained available for the final assessment, and the selected population and brief follow-up limit conclusions about older men or those without erectile dysfunction. [23]
Pregabalin and Outcome Priorities
Pregabalin was studied in 324 men with CP/CPPS at specialist centers because pelvic pain may involve altered nerve signaling. More men receiving the drug reached the predefined symptom-improvement threshold, but the difference from placebo was not statistically significant. Some secondary measures, including overall symptom scores and patient-rated improvement, favored pregabalin. These findings illustrate why a positive secondary result should not replace a trial’s main conclusion. The study offered a short assessment window and did not prove which particular pain subgroup, if any, would have a reliable benefit. [24]
Celecoxib and Temporary Improvement
Celecoxib was compared with placebo in 64 patients with difficult inflammatory CP/CPPS. During the trial, pain, quality of life, and overall symptom scores improved more in the celecoxib group, while urinary symptoms did not show the same advantage. After treatment stopped, the difference from placebo was no longer significant. The study therefore supports a distinction between symptom relief during exposure and sustained recovery. Its small sample and restriction to inflammatory disease limit generalization, and a short trial cannot establish the balance of benefits and harms over prolonged use. [25]
Finasteride and Preliminary Signals
Finasteride was evaluated in a placebo-controlled pilot study enrolling 76 men with inflammatory CP/CPPS. Sixty-four had at least one assessment while receiving their assigned treatment. Patient-rated improvement and symptom scores tended to favor finasteride, but the investigators considered the evidence insufficient to support its general use alone for CP/CPPS. They called for a larger study capable of confirming benefit. The useful lesson is that a promising numerical difference in a small pilot remains preliminary. Results from this inflammatory subgroup also cannot automatically be extended to every presentation of pelvic pain. [26]
Plant Extracts Have Product-Specific Evidence
An early quercetin study randomized 30 men with inflammatory or noninflammatory CP/CPPS to the botanical compound or placebo. Symptom scores improved more with quercetin, and a greater proportion reached the study’s improvement threshold. However, only 28 men completed the blinded comparison, making the result vulnerable to uncertainty from a very small sample. The paper also described a separate, unblinded group receiving a combination supplement; that observation is not equivalent to another placebo-controlled trial. The findings are promising preliminary evidence, without establishing durable benefit or interchangeability among commercial supplement formulations. [27]
Pollen Extract and Product Specificity
A multicenter trial evaluated a standardized pollen extract in 139 men with inflammatory CP/CPPS. Compared with placebo, the extract improved pain, overall symptom scores, and quality of life, and more participants met the trial’s response definition. Reported adverse events were minor within the study. The evidence concerns a particular preparation in a particular inflammatory subgroup, rather than every product described as pollen extract. Its short follow-up also leaves lasting benefit and uncommon harms uncertain. A positive botanical trial is not a recommendation to buy or combine supplements without clinical advice. [28]
Saw Palmetto and Newer Evidence
A 2021 multicenter trial investigated Serenoa repens, commonly called saw palmetto, against placebo for CP/CPPS. Researchers randomized 226 participants and included 221 in the main analysis. The extract produced greater improvements in overall symptoms and their component scores, with more participants meeting the response definition. Only minor adverse events were reported during observation. This is evidence for the extract tested, rather than proof that all saw palmetto products perform alike. The limited follow-up cannot establish lasting recovery, and the sample does not rule out uncommon or delayed harms. [29]
Acupuncture Has Support With Boundaries
A multicenter trial randomized 440 men with moderate to severe CP/CPPS to acupuncture or a sham procedure. More participants receiving acupuncture achieved a meaningful symptom reduction, and the difference persisted after treatment. This represents symptom improvement, not eradication of infection or a guaranteed cure. The trial was conducted in specialist hospitals in China, and sham acupuncture may itself have physiological effects. These findings support discussing acupuncture as an option. Availability, treatment burden, practitioner training, and individual preferences also matter when deciding how it fits into care. [30]
Shockwave Results Need Careful Interpretation
A 2026 systematic review of eight randomized trials found that low-intensity shockwave therapy improved CP/CPPS symptoms, mainly pain, compared with control treatments. Results differed substantially across studies and device types. Comparisons between focused, radial, and multifocal devices were exploratory, with few studies and no direct head-to-head evidence establishing a dependable winner. The main analysis emphasized outcomes around three months, leaving longer-term durability less certain. This supports an informed specialist discussion about the particular device and protocol, rather than accepting a general claim that shockwave treatment cures prostatitis. [31]
Practical support during assessment and prostatitis treatment
These suggestions adapt general guidance on healthcare communication, pain, work and caregiving. They offer practical ways to organise life around assessment and prostatitis treatment; they are not outcomes from prostatitis trials. Use the parts that fit your circumstances alongside the individual plan agreed with your healthcare team.
Describe the effect on everyday life
A short symptom record can make a difficult conversation more concrete. Note when discomfort occurs, what you were doing, and what seemed to make it better or worse. Include the effect on sleep, work, ordinary tasks and relationships, rather than recording a pain number alone. Cleveland Clinic’s general pain guidance discusses both daily functioning and pain diaries. For example, describing a meeting you could not finish gives your clinician useful context. Keep observations separate from explanations: noticing discomfort after an activity does not establish its cause. Ask which details would be most useful to bring to your next review. [32]
Choose your appointment priorities
Before the appointment, choose the concerns you most want addressed and put them at the top of a short list. One might concern the working diagnosis; another might be a symptom affecting your day; a third might be difficulty carrying out the existing plan. Bring relevant health history and mention previous problems with care. AHRQ recommends preparing questions and explaining barriers to following instructions. Say early if embarrassment makes a topic difficult to discuss. If time runs out, agree how the remaining questions will be handled. The list can help you return to a concern after an interruption. [33]
Keep medicine information together
Prepare one current list of the products you actually use, including prescriptions, nonprescription products, vitamins, herbal preparations and home remedies. Add known allergies and previous medicine reactions, describing what happened rather than relying only on a label such as ‘did not suit me’. ASHP advises sharing this information with your doctor or pharmacist and being open about how medicines are actually used. Bring packaging or an existing pharmacy list if names are difficult to remember. Ask the pharmacist to explain any confusing information. Keep the list available for different appointments so each professional can review the same account of your medicines. [34]
Leave with a clear explanation
At the end of the conversation, check that you can describe the main problem being addressed, your next actions and the reason for them. These are the three areas behind the Institute for Healthcare Improvement’s Ask Me 3 programme. If the explanation is unclear, ask for simpler language or an everyday example. You might say that you understand the appointment is for review but are unsure what information to bring. Ask the clinician to clarify that specific gap. Understanding the purpose of the plan also gives a companion a clearer way to help with the practical arrangements. [35]
Discuss privacy before an intimate examination
If an intimate examination is proposed, ask what it involves, why it is needed and what discomfort to expect. You can raise concerns about undressing, positioning or who will be present before it begins. The UK’s General Medical Council guidance requires explanation and consent, privacy while dressing, and stopping if the patient asks. It also addresses offering a trained chaperone. A trusted companion and a chaperone have different roles, so ask about both if you want support. Tell the clinician if you need a pause or another explanation. These discussions should help you participate in decisions about the examination. [36]
Arrange communication support early
Tell the clinic when booking if you need an interpreter, translated information or communication support related to a disability. Explain which language and format work best, and ask how that support will join a telephone or video appointment. HHS describes language assistance obligations for covered US programmes and accessibility considerations for telehealth. Ask the clinic to confirm the arrangements instead of assuming a relative must interpret sensitive discussions. Mention if a hearing, vision or technology barrier could make the proposed appointment difficult. Outside the United States, check the local service’s arrangements; availability and legal duties depend on the healthcare setting. [37]
Connect decisions to your priorities
When your clinician presents reasonable options, explain what matters most to you in choosing between them. That might include participating in family life, managing work responsibilities or reducing the burden of appointments. Australia’s Commission on Safety and Quality in Health Care describes shared decisions as a conversation combining clinical information with the person’s values and preferences. Ask how each suitable option relates to your priorities, what benefits and harms are uncertain, and how you will review the decision together. A useful goal is specific enough to discuss at the next visit. Goals can change as your circumstances and understanding develop. [38]
Make the follow-up arrangements explicit
Before leaving, write down how any planned test is booked, who will explain the results and when you should expect that explanation. Healthdirect’s general appointment guidance encourages questions about booking, results and what happens next. Ask which service is responsible if several clinicians are involved, and keep the contact details with your appointment notes. If you cannot use the patient portal, request another way to receive information. Put the agreed review in your calendar and note whom to contact if the promised information does not arrive. A result appearing on a screen may still need explanation in the context of your symptoms. [39]
Ask for specific workplace changes
If symptoms interfere with work, describe the task that is difficult and a change you would like to discuss. Examples include more evenly spaced breaks, a different working pattern or arrangements for medical appointments. Acas explains that reasonable adjustments are individual and depend on the circumstances. For someone troubled by prolonged sitting or unpredictable appointment needs, a conversation about the working day may be more useful than a vague request for flexibility. Agree how any arrangement will be reviewed and who needs to know. Acas guidance concerns Great Britain; a diagnosis alone does not establish identical employment rights in every country. [40]
Raise cost and access concerns
Tell the care team if cost, travel or limited help at home could prevent you from attending or carrying out the agreed plan. The Patient Advocate Foundation encourages open discussion of financial concerns and the practical support available. Ask the office who can explain expected charges, insurance questions or local assistance, rather than leaving an unanswered billing question until after a visit. Record the estimates and any remaining uncertainty. If several appointments are proposed, explain the combined effect on your time and budget. Assistance programmes have their own eligibility rules, so ask what applies to your situation. [41]
Agree on a companion’s role
If you want someone involved, decide what help would be welcome: taking notes, organising transport or keeping track of questions. Tell the clinic whom you want included and ask what permissions it needs before sharing information. Family Caregiver Alliance’s communication guidance recommends clarifying permissions and keeping useful notes. A supporter can help describe an observed difficulty while leaving room for your own account. Agree which information may be passed to other relatives and which should stay private. If the conversation feels rushed, ask how to arrange time for the unresolved concern. Support works best when its role is understood by everyone. [42]
Discuss a manageable pattern of activity
For ongoing pain that has been assessed, ask whether pacing could help you organise daily tasks within your individual care plan. Mersey Care’s general chronic-pain guidance describes balancing activity and rest instead of repeatedly doing too much on better days. Bring an example, such as catching up on every household job at once, and discuss a manageable arrangement. You might divide a task, share part of it or spread it across the week. Agree how to review the plan when symptoms change. This is a planning conversation with your clinician, not a prescribed exercise routine or a prostatitis cure. [43]
Take the pain account seriously
A useful conversation starts by taking the person’s account of pain seriously. The International Association for the Study of Pain recognises pain as a personal experience and says reports of pain should be respected. Family members can ask what the experience is like and what kind of help would be useful today. Avoid judging its significance only by how someone looks or how well they managed yesterday. If a clinical explanation is unclear, ask what is understood and what remains uncertain. Talking about emotional or social effects should sit alongside appropriate medical assessment, without implying that the person invented the symptoms. [44]
Give emotional strain its own attention
Uncertainty, disrupted plans and repeated appointments can be difficult to live with. Tell a trusted person or healthcare professional if worry, low mood or poor sleep is becoming hard to manage. WHO’s general stress guidance encourages seeking support when coping becomes difficult and keeping connections with people you trust. Be specific about the impact: perhaps you are withdrawing from friends or struggling to concentrate at work. Ask what support is available and how to access it. Caring for emotional wellbeing does not require deciding that stress caused the pelvic symptoms. Both symptoms and emotional burden deserve attention. [45]
Share the practical load at home
If a partner or relative is providing regular help, make the tasks visible rather than letting one person quietly absorb everything. List the jobs that need covering, such as transport, shopping or household administration, and agree who can realistically help. Carers UK encourages carers to consider their own need for breaks and seek practical support from friends, relatives or local services. Include the person receiving help in these arrangements and discuss what support they actually want. Make time for conversation and shared interests. When help is needed for longer, review the arrangement so it remains workable for everyone involved. [46]
Frequently asked questions
Is prostatitis always bacterial?
No. CP/CPPS is different from bacterial prostatitis. [3]
Can PSA diagnose prostatitis?
No. PSA can rise during prostatitis and does not diagnose the infection. [4]
Are repeat antibiotics routine in CP/CPPS?
No. Negative cultures and STI tests argue against repeated courses. [11]
Should everyone do Kegel exercises?
No. Pelvic floor treatment should follow an individual assessment. [13]
Can acupuncture help CP/CPPS?
A trial found symptom benefit, but it does not establish a cure. [30]
What should follow-up cover?
Clarify test results, the next review and whom to contact. [39]
Sources
- NICE NG110: acute prostatitis
- CDC: signs of sepsis
- NIDDK: prostatitis overview
- EAU 2026: bacterial prostatitis
- CDC: urethritis assessment
- Marquez-Algaba et al., 2021
- Cochrane: chronic bacterial prostatitis
- Karaiskos et al., 2019
- FDA: fluoroquinolone safety warning
- MHRA: fluoroquinolone restrictions
- AUA 2025: chronic pelvic pain
- Shoskes et al.: UPOINT, 2010
- EAU 2026: pelvic pain management
- FitzGerald et al., 2009
- Cornel et al., 2005
- Giubilei et al., 2007
- Tripp et al., 2011
- Litwin et al.: NIH-CPSI, 1999
- Nickel et al.: levofloxacin, 2003
- Alexander et al., Annals of Internal Medicine, 2004
- Nickel et al., NEJM, 2008
- Nickel et al., Journal of Urology, 2011
- Tawfik et al., World Journal of Urology, 2022
- Pontari et al., Archives of Internal Medicine, 2010
- Zhao et al., Brazilian Journal of Medical and Biological Research, 2009
- Nickel et al., BJU International, 2004
- Shoskes et al., Urology, 1999
- Wagenlehner et al., European Urology, 2009
- Zhang et al., World Journal of Urology, 2021
- Sun et al.: acupuncture, 2021
- Wu et al.: shockwave review, 2026
- Cleveland Clinic pain guidance
- AHRQ appointment preparation
- ASHP medicine information
- IHI communication questions
- GMC examination guidance
- HHS communication access; HHS telehealth accessibility
- ACSQHC shared decisions
- Healthdirect follow-up questions
- Acas workplace adjustments
- PAF access conversations
- FCA communication guidance
- NHS pacing guidance
- IASP pain definition
- WHO stress guidance
- Carers UK practical support





