
Medical information, not a diagnosis or an individual treatment plan. An endocrinology team should guide treatment. Source-checked October 14, 2026; editorial checking is not a substitute for review by your own clinician.
Hypoparathyroidism: the essentials
Hypoparathyroidism is a rare disorder in which the parathyroid glands do not produce enough parathyroid hormone, usually shortened to PTH. Blood calcium can fall as a result. The condition often develops after neck surgery, although other causes are possible. Treatment can control calcium levels, but ongoing blood tests and a clear medicine plan are important even when you feel well. [1]
A diagnosis introduces several unfamiliar ideas at once: calcium in the blood, calcium in urine, active vitamin D, and a hormone with a name resembling “thyroid.” This guide explains how those pieces fit together. It also separates the questions to raise at a routine appointment from symptoms that need urgent help. Use it to prepare a discussion with your clinical team rather than to choose supplement doses yourself.
When low calcium needs urgent care
Call your local emergency number for a seizure, difficulty breathing, collapse, or severely reduced awareness. Severe low calcium can cause prolonged muscle contractions, including spasm around the voice box, and dangerous heart-rhythm changes. Do not wait for a routine appointment or try to manage a severe episode by repeatedly taking extra supplements. Tell emergency staff about hypoparathyroidism, recent neck surgery, and your current medicines. [7, 8]
After thyroid surgery, contact the surgical team promptly about new tingling around the mouth or fingertips, or muscle spasms. Sudden tight neck swelling with trouble breathing or swallowing is also an emergency: bleeding in the neck is a separate possible postoperative complication. Do not assume that every new neck or breathing symptom is caused by calcium. [6]
In hospital, severe symptomatic hypocalcemia may need intravenous calcium and heart monitoring while clinicians investigate the cause. Symptoms depend partly on how quickly calcium falls, so a single numerical cutoff cannot safely tell a reader whether to stay home. Your own emergency plan should name whom to call and where to go. [8]
What the parathyroid glands do
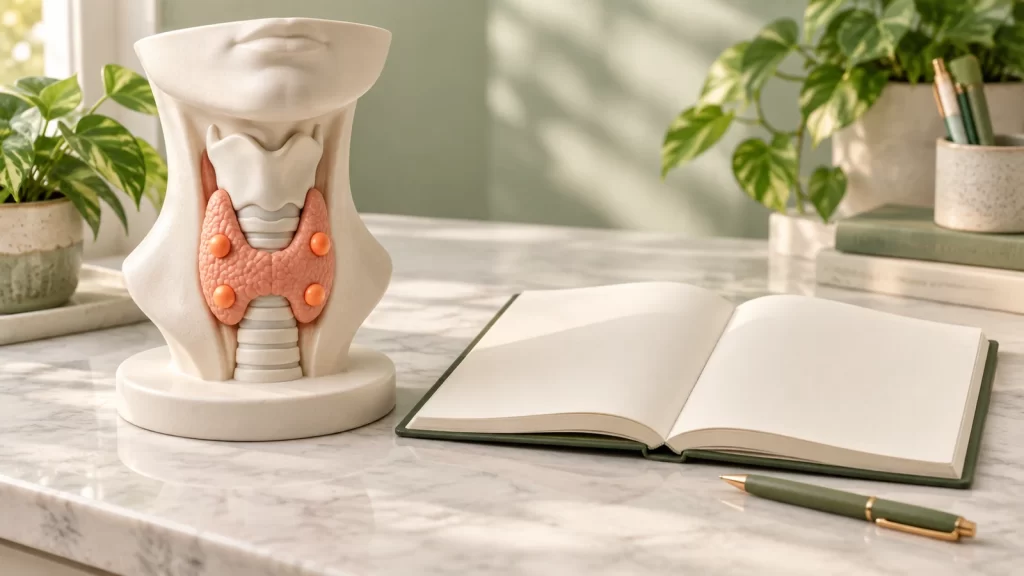
Most people have four small parathyroid glands near the thyroid. PTH helps coordinate calcium movement between the blood, bones, intestines, and kidneys. When calcium drops, PTH normally increases: the kidneys conserve more calcium, and the body supports calcium absorption and release into the circulation. This feedback system matters because nerves, muscles, and the heart depend on an appropriate blood calcium level. [3]
The thyroid and parathyroid glands have different jobs despite their nearby locations and similar names. Thyroid hormones influence metabolism and energy use. Parathyroid hormone mainly regulates mineral balance. Someone who has had a thyroid removed may need both thyroid hormone replacement and treatment for low calcium, but one medicine does not automatically perform the other medicine’s job. [29]
Hypocalcemia means low blood calcium; hypoparathyroidism is one possible cause. Pseudohypoparathyroidism is another, distinct disorder in which the body does not respond properly to PTH. Similar calcium results therefore do not establish the same diagnosis or justify borrowing another person’s treatment. Your clinician needs to interpret the hormone level alongside the calcium result and the wider medical history. [28]
Causes and the meaning of chronic hypoparathyroidism
After neck surgery
The parathyroid glands can be injured or accidentally removed during thyroid or other neck operations. Temporary disruption may improve over weeks or months. A discharge prescription for calcium therefore does not, by itself, prove lifelong gland failure. Keep the planned postoperative checks, and let the surgical or endocrine team decide whether treatment can safely be reduced. [6]
The revised European Society of Endocrinology guideline defines chronic postsurgical hypoparathyroidism as persisting for more than 12 months after surgery. Recovery can occur even later. This is a classification used during follow-up, not an instruction to postpone necessary treatment or stop medicines when a particular month arrives. [2]
Other causes
Nonsurgical causes include autoimmune damage, very low magnesium, and genetic conditions affecting gland development, hormone production, or calcium sensing. Some people have hypoparathyroidism alone; others have a broader syndrome. An unexplained diagnosis, a childhood onset, or relatives with similar calcium problems can prompt an endocrinologist to consider genetic assessment. Testing is selected from the individual history rather than ordered as one universal panel. [5]
For example, autosomal dominant hypocalcemia can involve an overactive calcium-sensing pathway. Some affected people also lose excessive calcium in urine, which can contribute to kidney stones or kidney calcium deposits. This is a reason to clarify the underlying diagnosis before assuming that raising blood calcium as high as possible is desirable. A genetic counselor can explain what a confirmed result means for relatives. [24]
Low calcium can also occur within 22q11.2 deletion syndrome, which may involve heart, immune, feeding, hearing, or developmental differences. Its features vary considerably, and many cases arise without a family history. Mentioning these conditions is not a checklist for self-diagnosis; it explains why a child or adult with several apparently unrelated problems may benefit from coordinated specialist assessment. [25]
Symptoms: recognize a pattern without self-diagnosing
Common clues include tingling in the lips, fingers, or toes; muscle cramps; and painful stiffness or spasms. Dry skin, brittle nails, and hair changes may also occur. More serious presentations include confusion, seizures, and an irregular heartbeat. These symptoms can overlap with other conditions, which is why a history and laboratory testing are more useful than matching an online symptom list. [1]
Some people develop symptoms gradually or have very mild symptoms, and low calcium is discovered on a blood test. Children may have problems with tooth development or enamel, growth, or development. Tell the clinician about changes noticed over time, not only the symptom that prompted today’s visit. A dentist or pediatric team may provide information that helps put the history together. [7]
Fatigue, concentration difficulties, low mood, and reduced quality of life can accompany hypoparathyroidism. They deserve discussion even if the most recent calcium result looks acceptable. At the same time, a symptom should not automatically be attributed to this diagnosis: your clinician may assess other explanations. Describe what has changed, how often it happens, and the activities it prevents you from doing. [5]
For an appointment, a short timeline is often easier to discuss than a long list without dates. Record the symptom, its approximate start and duration, the medicines actually taken that day, and any recent illness. Add the date of a relevant blood test if you have it. This is an organizational aid, not a home test for whether calcium is high or low.
How hypoparathyroidism is diagnosed
Diagnosis usually requires low ionized calcium or low albumin-adjusted total calcium together with PTH that is undetectable, low, or inappropriately normal. “Inappropriately normal” means the hormone has not risen as expected in response to low calcium. International guidance describes confirming the biochemical pattern on two occasions at least two weeks apart; urgent treatment is not delayed to satisfy that definition. [10]
Total calcium includes calcium attached to proteins as well as free calcium. Ionized calcium measures the free, biologically active portion. Because protein levels can influence total calcium, clinicians may interpret it with albumin or order ionized calcium when appropriate. A calcium blood test does not measure how much calcium is stored in the skeleton and cannot replace an assessment of bone health. [9]
| Test | Why it may be included |
|---|---|
| PTH with calcium | Is the hormone response appropriate for the calcium concentration? Reading the two together is more informative than treating either as an isolated abnormal flag. [3] |
| Phosphate, also called phosphorus | Is another part of mineral balance abnormal? Phosphate can rise in hypoparathyroidism, but kidney disease and other factors also affect it; the result needs context. [11] |
| Magnesium | Could a magnesium disturbance contribute to symptoms or abnormal calcium? The clinician also reviews medicines and conditions that change magnesium absorption or loss. [12] |
| Creatinine and estimated GFR | How well are the kidneys filtering? An estimated filtration rate is interpreted with age, medical history, previous results, and other kidney tests when needed. [26] |
| Vitamin D and urine calcium | What is the vitamin D status, and how much calcium is leaving in urine? These help complete the initial assessment and guide later treatment monitoring. [10] |
A PTH result reported as normal can be confusing. The reference interval describes results in a population, while the clinical question is whether enough hormone is present for this particular calcium level. When calcium is low, PTH should normally rise. Ask the clinician to explain the paired results rather than assuming that a normal flag rules out a parathyroid problem. [3]
Read results using the laboratory’s units and reference interval. Laboratories may use different methods, and a flagged result is not always a diagnosis by itself. Likewise, a result inside a reference interval does not explain every symptom. Ask for the trend and the clinician’s interpretation, particularly if you are comparing results from different hospitals or trying to understand a change after treatment. [30]
Treatment with calcium, active vitamin D, and magnesium
Why the combination matters
Conventional treatment commonly uses active vitamin D with adequate calcium intake, adding calcium supplements when needed. It helps correct the mineral imbalance but does not reproduce every action of PTH. The plan needs to balance relief of symptoms against excessive calcium in blood or urine. Dose adjustments are clinical decisions informed by laboratory results, kidney health, and the medicines already being taken. [18]
Calcitriol is an active vitamin D medicine that helps the body use calcium from food or supplements. It comes in different preparations, and the prescribed amount must be followed carefully. Show your pharmacist every vitamin, antacid, laxative, and supplement you take: additional vitamin D, calcium, or magnesium products can affect the plan. Do not add or substitute an over-the-counter product without checking. [13]
Ordinary vitamin D from food, sunlight, or common supplements requires processing in the liver and then mainly the kidneys to become active. The usual vitamin D status blood test measures 25-hydroxyvitamin D, not the same molecule as calcitriol. This explains why a prescription for active vitamin D and a separate discussion about vitamin D stores can coexist; the names do not mean the products are interchangeable. [15]
Keep the prescribed strength and measuring method clear, especially if a liquid replaces capsules. Calcitriol instructions also include what to do after a missed dose; do not double a dose to make up for one missed. If you are unsure how close the next dose is, or your situation differs from the written instructions, ask the pharmacist or prescriber before improvising. [13]
Understanding a calcium label
Calcium carbonate and calcium citrate contain different proportions of elemental calcium. The useful label figure is the elemental calcium amount, together with the serving size, rather than the tablet’s overall weight. Carbonate is more dependent on stomach acid and is generally taken with food; citrate is less dependent on acid. Calcium can cause constipation or bloating. Ask about a different preparation or schedule rather than abandoning treatment. [14]
Bring the actual package or a clear photograph to medicine reviews. Check whether the stated amount is for one tablet or several, and whether vitamin D is included. A brand change can otherwise be surprisingly confusing. Ask the pharmacist to write the agreed product, number of tablets, and timing in one place; do not work out a replacement dose from this article.
Magnesium requires its own assessment
Severe magnesium deficiency can disturb calcium regulation. Magnesium supplements are therefore sometimes part of treatment, but extra magnesium is not automatically helpful when levels are normal. High supplemental intakes can cause diarrhea, and toxicity is more likely when kidney function is impaired. A clinician should select replacement and follow-up rather than relying on a supplement marketed for cramps or sleep. [16]
Monitoring: blood calcium is only part of the picture
For stable adults, the 2025 European guideline suggests routine blood monitoring every three to six months and checks one to two weeks after treatment changes, with timing individualized. It also suggests periodic 24-hour urine calcium testing during conventional therapy. People with symptoms, unstable results, pregnancy, or a medicine-specific monitoring schedule need a different frequency; a routine interval is not a reason to wait when unwell. [2]
A 24-hour urine collection shows calcium excretion over a day. Follow the laboratory’s exact instructions for the start time, every subsequent collection, storage, and return. Usually the first urine is discarded and the collection finishes with a sample at the same time the following day. If a sample is missed or spilled, tell the laboratory and ask what to do rather than presenting the collection as complete. [17]
High urine calcium can matter even when the blood result appears satisfactory. PTH normally helps the kidneys retain calcium; without its usual action, treatment has to be balanced carefully. Your team may discuss dietary sodium and, for selected patients, a thiazide diuretic to reduce urinary calcium. This is not a reason to start a water pill yourself: the choice and monitoring depend on your circumstances. [18]
When a thiazide is used to address urinary calcium, follow-up may include blood pressure, potassium, magnesium, and kidney function. International guidance couples this treatment with a low-sodium approach where appropriate. A drug sometimes called a water pill can have quite different reasons for use, so make sure everyone prescribing for you knows why it was added and who is monitoring it. [10]
Magnesium results also need context. Long-lasting diarrhea, malabsorption, kidney problems, some diuretics, and acid-suppressing proton pump inhibitors can affect magnesium balance. A medication review is therefore part of investigating an unexpected result. Do not stop a prescribed medicine because it appears on a possible-cause list; ask the prescriber whether it is relevant and whether an alternative or closer monitoring is appropriate. [12]
Phosphate is an essential nutrient, not simply something to eliminate. High blood phosphate may occur without obvious symptoms, so a person cannot reliably judge it by how they feel. Your clinician may interpret phosphate alongside calcium, PTH, vitamin D, and kidney results, then decide whether treatment or dietary changes are warranted. A restrictive diet should follow that assessment, not precede it. [11]
Protecting the kidneys and watching for complications
Excessive calcium and vitamin D treatment can raise blood or urine calcium and impair kidney function. Hypoparathyroidism can also be associated with kidney stones, cataracts, and calcium deposits in other tissues. These are possible complications, not a prediction that every person will develop them. Reporting new symptoms and attending follow-up gives the team opportunities to identify problems and reassess treatment. [4, 7]
Creatinine and estimated GFR help assess kidney filtration, but an eGFR is an estimate rather than a complete picture. A change may lead to repeat testing, urine protein assessment, or imaging, depending on the circumstances. Ask what the result means compared with your own previous measurements. Avoid interpreting a single value as proof of irreversible kidney failure or as reassurance that every kidney risk has disappeared. [26]
Seek prompt medical assessment for sharp back, side, lower abdominal, or groin pain; blood in urine; painful urination; or difficulty passing urine. Fever, chills, or vomiting with these symptoms also matter. A stone is one possibility, but other serious conditions can look similar. For background, see our guide to kidney stone symptoms and prevention; your hypoparathyroidism team should individualize any prevention advice. [19]
If a complication is suspected, ask which question a proposed test will answer. An ultrasound for a urinary problem, an eye examination for visual change, and a review of persistent cognitive symptoms address different concerns. Keep the results accessible to the clinicians sharing your care so that a new consultation begins with the findings already established rather than an incomplete recollection.
PTH replacement: current options and important limits
PTH replacement may be considered when symptoms or other important problems continue despite optimized conventional treatment. The 2025 European guideline emphasizes quality of life as well as biochemical control. Under conventional therapy, calcium targets are often toward the lower part of the reference range or slightly below, individualized to symptoms and safety; “higher” is not automatically “better.” [2]
In the United States, Yorvipath, containing palopegteriparatide, is approved for adults with hypoparathyroidism. Its prescribing information was revised in August 2026. It was not studied for acute postsurgical hypoparathyroidism. Initiation requires a clinician-directed transition from the existing calcium and active vitamin D regimen, followed by blood testing; it is not an emergency rescue treatment or a do-it-yourself substitute for tablets. [20]
The US label warns about serious high or low calcium, severe allergic reactions, dizziness related to low blood pressure on standing, potential osteosarcoma risk in susceptible patients, and interactions including digoxin. Abrupt interruption can cause severe low calcium. The label specifies calcium checks after starting or changing relevant doses and at least every four to six weeks once maintenance dosing is reached. Arrange an interruption plan with the prescriber. [20]
Get emergency help for possible severe allergy, such as swelling of the face, lips, tongue, or throat, or difficulty breathing after an injection. The updated label requires permanent discontinuation for a severe hypersensitivity reaction, with the subsequent calcium-treatment plan managed by the prescriber. [20]
In the European Union, Yorvipath is authorized for adults with chronic hypoparathyroidism. It is injected under the skin using a prescribed pen and should be started and monitored by a professional experienced with the condition. Its effect replaces missing PTH activity; authorization does not mean that every adult is a suitable candidate or that every country funds it in the same way. [21]
Older information may describe Natpar or Natpara, products containing PTH(1–84). Natpar manufacturing ended in 2024, and the European Commission’s register now lists its authorization as withdrawn. A historical approval or an old medicine webpage is not evidence of current supply. Anyone affected by a treatment transition needs an endocrine-team plan; products and doses cannot be assumed equivalent. [31, 32]
Before a switch, ask what problem the new treatment is intended to improve, which measurements will track benefit, who will review early blood tests, and whom to contact if the medicine cannot be obtained. Include practical questions about training, storage, travel, and cost. The decision should reflect your priorities and the treatment’s risks and uncertainties, rather than the appeal of needing fewer tablets alone. [27]
Food, supplements, and medicine interactions
Useful food sources of calcium include dairy products, calcium-fortified drinks, calcium-set tofu, and some vegetables or fish with edible bones. Amounts vary by product, so check labels if food calcium is part of your agreed plan. Different foods also differ in how well their calcium is absorbed. Ask a dietitian to fit the plan around allergies, preferences, budget, and other medical conditions. [14]
Kidney-stone prevention advice depends on the stone type and the person’s health. Adequate fluid and sodium choices may be discussed, but prescribed fluid restrictions also matter. Do not remove calcium-rich foods or stop prescribed calcium simply because a stone contains calcium. Nutrition and treatment need to be reconciled by the team caring for both the stone risk and the hormone deficiency. [35]
If you also take levothyroxine, ask for a schedule that separates it from calcium and iron supplements; official medicine information recommends at least four hours. Antacids and other medicines can also interfere. A pharmacist can review the complete regimen rather than solving each product’s timing separately. Consistency matters, and a written schedule is easier to follow than several instructions remembered from different visits. [23]
Tell the laboratory and clinician about biotin, often sold in hair, skin, or nail supplements. It can interfere with some laboratory assays and produce misleading results. Whether an assay is affected and whether a supplement should be withheld are questions for the testing team. Do not choose a universal “stop for this many days” rule or delay urgent testing on your own. [22]
The amount of vitamin D listed for a healthy population is not a treatment instruction for hypoparathyroidism. Large unsupervised supplemental doses can cause toxicity, including excessive blood calcium, kidney problems, and other serious effects. Avoid layering a multivitamin, a bone-health product, and a separate vitamin D preparation without checking their combined contents against the plan your clinician actually prescribed. [15]
Be cautious about products promising to repair the glands, cure the condition, or replace prescribed treatment. In the United States, dietary supplements are not approved by the FDA for safety and effectiveness before marketing. “Natural” does not establish safety, and combining products can introduce interactions or excessive ingredients. Show the exact product label to a pharmacist before buying or taking an additional supplement. [33]
Pregnancy, breastfeeding, and children
Discuss a planned pregnancy with the endocrine and maternity teams early, and contact them promptly if pregnancy occurs. Calcium and active vitamin D requirements can change, and management needs to avoid both low and high maternal calcium. Pregnancy is not a reason to stop treatment yourself. Specialist guidance recommends frequent calcium monitoring, often every three to four weeks, with closer checks around delivery and after changes. [34]
Planning continues after birth. Breastfeeding and later weaning can change calcium requirements, so the pre-pregnancy prescription may not remain appropriate. The maternity and pediatric teams should know about the condition and plan the newborn’s calcium monitoring. Ask who will coordinate maternal testing, medicine review, and the baby’s follow-up before leaving hospital. Medication choices, including PTH therapy, require specialist pregnancy and lactation review. [34]
Children need pediatric endocrine care that considers growth, teeth, development, and the cause of the disorder. Adult instructions or an adult relative’s prescription are not suitable templates. Keep school or childcare information practical: identify the responsible adults, the prescribed medicine arrangements, and the clinician-approved steps for symptoms. The written plan should be reviewed as the child’s needs and treatment change. [4]
Making day-to-day care manageable
Use one current medicine list containing the generic name, brand or preparation, strength, prescribed timing, and the clinician responsible for it. Mark when a new prescription replaces an older one. A separate page can hold the clinic number, out-of-hours contact, laboratory arrangements, and next appointment. The aim is to make the agreed plan easy to find when you are tired, traveling, or seeing an unfamiliar clinician.
Ask your team for instructions covering vomiting, diarrhea, inability to take medicines, missed doses, and an unexpected supply problem. Clarify whether a situation calls for a phone call, a blood test, or urgent assessment. Write down the answer instead of assuming that every medicine follows the same rule. In particular, do not invent a doubling or catch-up schedule from someone else’s online experience.
At follow-up, explain what you most want to improve: perhaps predictable workdays, fewer interruptions from symptoms, or a simpler schedule. Ask about the available choices, their benefits and risks, and how a decision will be reviewed. You may bring a trusted person, request an interpreter, or ask the clinician to write the main instructions down. Repeat the plan back in your own words to check that you understood it. [27]
Frequently asked questions
Is hypoparathyroidism the same as an underactive thyroid?
No. An underactive thyroid concerns thyroid hormone, whereas hypoparathyroidism concerns PTH and calcium regulation. The glands are close together, and an operation can make both issues relevant to one person. Ask which diagnosis each prescribed medicine treats; needing levothyroxine does not by itself establish a parathyroid problem. [29]
Can I tell my calcium level from tingling or fatigue?
No symptom gives a reliable calcium measurement. Low calcium can cause tingling and cramps, but some people with abnormal calcium have no symptoms. High calcium can cause thirst, frequent urination, constipation, weakness, or confusion. New or worsening symptoms warrant the agreed clinical advice, with emergency help for severe features, rather than trial-and-error supplement changes. [9]
Why measure urine calcium if blood calcium is controlled?
The tests answer different questions. Blood testing checks the circulating calcium concentration, while urine testing helps assess how much calcium leaves the body. A urine collection may therefore remain useful even when a blood result is reassuring. Follow collection instructions carefully and ask how the result changes your individual plan. [17]
Can ordinary vitamin D replace calcitriol?
Do not substitute one for the other without your prescriber. Ordinary vitamin D undergoes activation in the body, while calcitriol is the active form. Your team may assess both active-vitamin-D treatment and vitamin D stores, but their roles, preparations, and prescribed amounts differ. A similar name on a bottle does not establish an equivalent treatment. [15]
Does successful treatment mean I can stop follow-up?
Feeling better is welcome, but hypoparathyroidism treatment still needs regular testing. Your team checks whether the medicine remains appropriate and whether calcium is becoming too low or too high. Keep the agreed appointments, and ask how you will receive results and who will act on them if more than one clinic is involved. [1]
What should I bring to an endocrine appointment?
Bring your current medicine packages or photographs, recent laboratory reports with dates and units, the operation or discharge summary if relevant, and a brief symptom timeline. Choose two or three questions you most need answered. Before leaving, confirm the next test date, the person reviewing it, and the contact route if your symptoms change before the next appointment.
Video note: The original video below is retained as supplementary background. It is older material and has not been independently medically reviewed for this update. Current medicine availability, labels, and your clinician’s advice take priority.





