Understanding Hodgkin lymphoma
Hodgkin lymphoma, historically called Hodgkin’s disease, is a cancer of lymphocytes, cells involved in immune defense. It often affects lymph nodes but can involve other tissues. Many people receive treatment intended to cure it, including people with advanced disease. The right plan depends on the precise diagnosis, disease extent, overall health, and response to treatment.
This guide focuses on adults. It explains the decisions behind testing and treatment rather than prescribing a regimen. Children require age-appropriate specialist care. A hematology or oncology team should interpret symptoms, pathology, and scans together; an online description cannot establish a diagnosis or predict an individual outcome.
Classic disease and the lymphocyte-predominant distinction
Classic, or classical, Hodgkin lymphoma is biologically different from the uncommon disease traditionally named nodular lymphocyte-predominant Hodgkin lymphoma. The International Consensus Classification uses the name nodular lymphocyte-predominant B-cell lymphoma for the latter. Older records and other classification systems may still use the Hodgkin name. This terminology difference is worth clarifying rather than assuming two reports describe different cancers.
Classic disease has characteristic Hodgkin/Reed–Sternberg tumor cells within a much larger background of inflammatory cells. The lymphocyte-predominant disease has different tumor-cell features and protein markers. A specialist pathologist combines architecture, cell appearance, and staining results to distinguish them. The distinction matters because management can differ substantially. Ask for the exact pathology diagnosis, not simply the shorthand word “lymphoma.”
Symptoms that deserve medical assessment
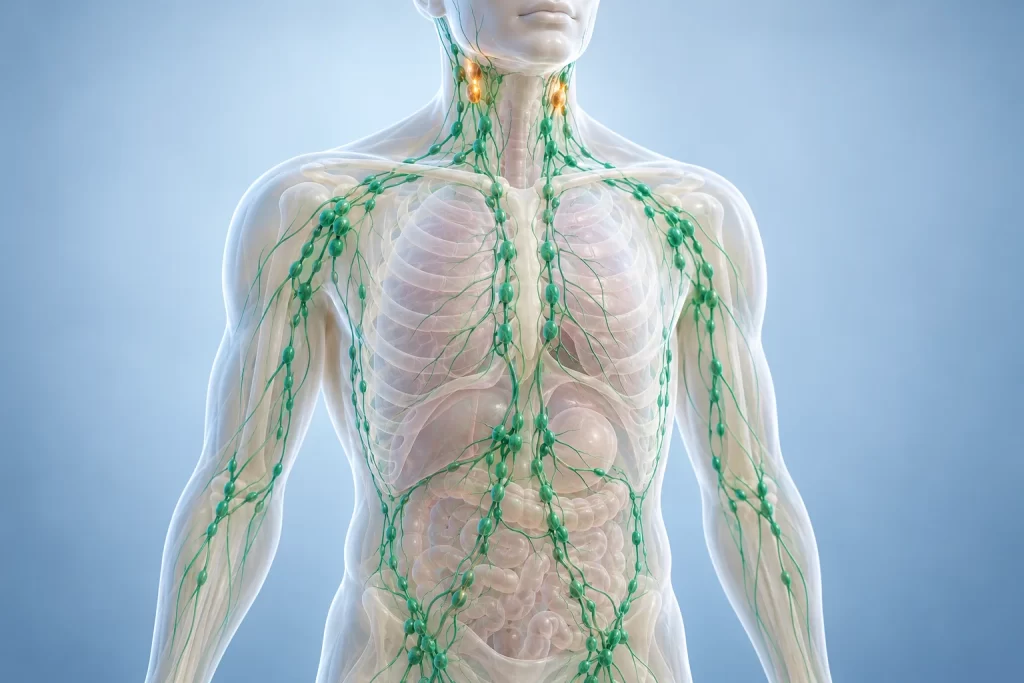
A persistent, usually painless swelling in the neck, armpit, or groin is a common presentation. Other possible symptoms include unexplained fever, drenching sweats at night, itching, weight loss, and breathlessness. Some people notice pain in affected glands after alcohol, but this is neither a reliable screening test nor a reason to try drinking to investigate a lump.
These symptoms have many causes. An enlarged lymph node is often related to infection, and itching or sweating alone does not establish lymphoma. Arrange a medical assessment for unexplained symptoms, particularly a lump that persists or grows. Tell the clinician when it appeared, whether it changes, and what other symptoms accompany it. An urgent referral means further investigation is needed; it does not itself mean cancer has been diagnosed.
B symptoms and symptoms inside the chest
Clinicians use “B symptoms” for a particular group: unexplained fever, drenching night sweats, and substantial unintentional weight loss. Weight loss exceeding 10% of body weight over six months is the conventional threshold. Report smaller changes too, because they can still warrant assessment. Fatigue and itching are important symptoms but are not, by themselves, formal B symptoms.
Nodes deep in the chest cannot usually be felt from outside. Enlargement there may cause cough, chest discomfort, or breathlessness. Abdominal involvement can produce discomfort or a feeling of fullness. The location of symptoms helps guide examination and testing but cannot identify the lymphoma type. Keep a short record of measured temperatures, weight changes, and whether night sweats soak clothing or bedding; concrete observations are more helpful than trying to assign yourself a stage.
Urgent warning: breathing difficulty or upper-body swelling
A large chest mass can sometimes compress the superior vena cava, the major vein returning blood from the upper body to the heart. This can cause facial puffiness, swollen neck veins, headache or pressure that worsens on bending forward, and breathlessness. A clot around a central venous catheter can also obstruct this vein.
These symptoms need prompt assessment rather than waiting for a scheduled lymphoma appointment. Treatment depends on the cause and severity and may involve a stent, cancer-directed treatment, or treatment for a clot. Do not assume a new symptom is harmless because lymphoma treatment has already started.
Causes and risk factors without blame
The exact cause in an individual is usually unknown. Recognized associations include previous Epstein–Barr virus infection, impaired immunity, and having a close relative with Hodgkin lymphoma. Risk also varies with age and sex. An association describes a pattern in populations; it does not mean a factor inevitably causes the disease.
Many people have had Epstein–Barr virus without ever developing lymphoma. Likewise, most relatives of someone with Hodgkin lymphoma do not develop it. A risk factor cannot confirm that a lump is malignant, and having no recognized risk factor cannot rule cancer out. Discuss significant immune conditions, immune-suppressing treatment, and relevant family history with the clinician. Avoid treating a diagnosis as evidence that someone caused their own illness or could necessarily have prevented it.
Screening is different from investigating symptoms
There is no widely recommended screening program for Hodgkin lymphoma in people without symptoms. Routine screening blood tests or scans have not been shown to improve survival from this disease. Buying an imaging package or repeatedly checking blood counts is therefore not a substitute for an appropriate clinical assessment.
When symptoms are present, testing has a different purpose: finding the explanation for a specific concern. A clinician reviews the history, examines relevant areas, and decides whether observation, investigations, or specialist referral is appropriate. People with a significant family history or other risk factors can discuss a sensible follow-up approach with their doctor. The useful question is not “Which scan can guarantee I do not have lymphoma?” but “What findings would make you investigate this symptom further, and when should I return?”
A tissue biopsy establishes the diagnosis
Blood tests and scans can raise suspicion, but diagnosis requires examination of tissue. Removing a whole lymph node, or a substantial part of one, can preserve the structure needed for interpretation. A core-needle biopsy may be appropriate when surgical sampling is difficult. A fine-needle sample alone may not provide enough material for a confident lymphoma diagnosis.
The pathologist assesses the cells and uses tests such as immunohistochemistry to look for relevant proteins. Classic Hodgkin lymphoma commonly expresses CD30 and often CD15, but no single stain should be interpreted in isolation. A small or inconclusive sample may need repeat sampling or specialist review. This is particularly important if the tissue findings and clinical picture disagree. Ask whether the diagnosis is definitive, whether enough tissue was obtained, and whether a hematopathologist has reviewed an unusual result.
PET/CT and the role of bone marrow testing
FDG-PET/CT combines a map of glucose uptake with detailed anatomical images. Because Hodgkin lymphoma is usually FDG-avid, this is an important baseline examination for mapping disease and later comparing treatment response. A CT component also shows the size and position of enlarged structures. Imaging findings must fit the clinical context.
A bone marrow biopsy is no longer routine for every person with Hodgkin lymphoma when an adequate PET/CT has been performed. The team may still recommend additional testing if unexplained blood abnormalities, uncertain findings, or a different diagnostic concern would change management. This does not mean marrow assessment is unimportant; it means modern imaging often supplies the relevant information without another invasive procedure. Ask what question each proposed test is intended to answer and whether its result could change treatment.
What stages I to IV mean
Stage describes the distribution of lymphoma, not how someone feels. The diaphragm is the muscle separating the chest from the abdomen.
| Stage | Simplified description |
|---|---|
| I | One lymph-node region or lymphoid site; a single isolated extranodal site has a specific designation. |
| II | Two or more lymph-node regions on the same side of the diaphragm, sometimes with nearby local extension. |
| III | Lymph-node involvement above and below the diaphragm. |
| IV | Disseminated involvement of organs outside the lymphatic system, such as liver or bone marrow. |
The letters A and B indicate the absence or presence of defined B symptoms. Bulk describes a large disease mass and can influence treatment, especially in stage II. The full staging report matters more than the number alone; ask the team to explain any additional labels.
Risk assessment and pretreatment checks
Early-stage disease is often separated into favorable and unfavorable risk groups. Different study groups use somewhat different combinations of bulky disease, inflammatory markers, number of affected nodal regions, and other features. Two patients with stage II disease may therefore receive different recommendations without either plan being inconsistent.
Before treatment, clinicians assess blood counts, kidney and liver function, and relevant infection history. Heart and lung assessment can establish a baseline before medicines with potential cardiac or pulmonary effects. Existing illnesses, previous cancer treatment, and pregnancy possibility must be discussed. Fertility counseling belongs before potentially fertility-damaging therapy whenever feasible. Bring a complete medication list, including nonprescription products, so the team can assess interactions and plan supportive treatment. The purpose is to choose treatment safely, not simply to complete a checklist.
Interpreting Deauville scores and residual masses
PET response reports often use the five-point Deauville scale, which compares uptake in suspicious areas with reference tissues, including the liver. A score is part of an interpretation, not a diagnosis that patients should act on independently. The definition of a negative interim scan can differ between treatment protocols, particularly when clinicians are considering reducing therapy.
A mass can remain visible after successful treatment because structural tissue does not always disappear. Conversely, increased FDG uptake can reflect inflammation or infection rather than active lymphoma. Timing after treatment and comparison with baseline images matter. When a result is unexpected, the next step may be expert image review, repeat imaging, or biopsy rather than immediately declaring treatment failure. Ask whether the scan shows a complete metabolic response and what evidence supports the proposed next step.
Early-stage treatment: discussing chemotherapy and radiation
For selected early-stage classic Hodgkin lymphoma, clinicians consider chemotherapy with radiation or a chemotherapy-based strategy that avoids radiation. These choices balance the likelihood of controlling lymphoma against later treatment effects. A reassuring interim PET result does not automatically prove that radiation adds no benefit.
The RAPID trial studied selected patients with early-stage disease and a negative PET scan after chemotherapy. It did not establish the prespecified noninferiority of omitting radiation. This is one reason counseling should distinguish freedom from relapse from overall survival: an additional relapse may sometimes be successfully treated, but that treatment brings its own burden. Ask for the expected difference in relapse risk for your particular situation, the radiation field proposed, and the likely exposure of nearby organs. Trial results from a selected population should not be generalized to every stage II presentation.
How modern radiation planning reduces exposure
Modern involved-site radiation aims treatment at relevant disease sites rather than automatically irradiating the broad regions used in older approaches. Planning uses information from the original disease distribution as well as subsequent response. This is why retaining baseline scans can be important even after a mass has shrunk.
The radiation oncologist weighs lymphoma control against exposure of structures such as the heart, lungs, breasts, thyroid, and other nearby tissues. Technique depends on the location and shape of the target and on available equipment. A more sophisticated technology is not automatically the best choice for every person; the actual dose distribution matters. Ask which normal tissues receive meaningful exposure, how the plan limits it, and what short- and long-term effects apply to that field. Radiation decisions should be coordinated with the systemic-treatment team.
ABVD, AVD, and PET-adapted treatment
ABVD combines doxorubicin, bleomycin, vinblastine, and dacarbazine. AVD omits bleomycin. In the RATHL study, patients with an appropriate negative interim PET result after initial ABVD could continue without bleomycin, reducing pulmonary toxicity while maintaining similar disease control within that trial’s framework.
This evidence supports a planned response-adapted approach; it does not mean patients should independently omit drugs or that every regimen uses the same PET rule. The initial regimen, stage, scan timing, and response criteria all matter. Bleomycin can injure the lungs, so new cough or breathlessness during treatment should be reported promptly rather than assumed to be lymphoma or a routine cold. Ask which drugs are intended for the first phase, whether an interim scan could change the plan, and exactly what result would trigger that change.
Nivolumab plus AVD: what the trial showed
Nivolumab blocks PD-1, an immune checkpoint, and can help immune cells attack classic Hodgkin lymphoma. The S1826 trial compared nivolumab plus AVD with brentuximab vedotin plus AVD in previously untreated stage III or IV disease. It enrolled adolescents and adults; this article addresses the adult clinical context.
The published results favored nivolumab-AVD for progression-free survival and showed a different side-effect profile. Progression-free survival measures time without progression or death; it is not identical to a lifetime cure rate. The comparison also does not establish the best approach for every early-stage presentation or every person with major coexisting illness. Ask how your characteristics compare with the study population and whether an immune-mediated condition or previous treatment changes the balance of benefits and risks. Long-term follow-up remains important with newer combinations.
United States indication and eligibility
On March 20, 2026, the US Food and Drug Administration approved nivolumab with AVD for previously untreated stage III or IV classical Hodgkin lymphoma in adults and children aged 12 years or older. The stage and treatment-history restrictions are important. This approval should not be described as a universal indication for all Hodgkin lymphoma, all age groups, or the lymphocyte-predominant entity.
An approved indication establishes a regulatory use; it does not decide which treatment is best for an individual. The clinician still evaluates contraindications, organ function, immune-related risks, competing options, and treatment goals. Insurance or service availability can also require separate confirmation. If a proposed use falls outside the approved population, ask whether it is supported by a guideline, clinical-trial evidence, or a specific individualized rationale rather than assuming it has the same regulatory status.
European authorization and local access
The European Medicines Agency’s current Opdivo information also includes nivolumab with AVD for previously untreated stage III or IV classical Hodgkin lymphoma in adults and adolescents aged 12 years or older. Its other Hodgkin lymphoma indications have their own age, prior-treatment, and combination requirements. Those details should not be merged into a single broad claim.
Regulatory authorization, national reimbursement, and an individual hospital’s treatment pathway answer different questions. A medicine listed by a regulator may not have identical funded access in every health system. Confirm the applicable local indication and coverage with the treating center. Ask whether a recommendation is routine locally, requires a funding decision, or is offered within a study. Patients comparing advice across countries should compare the actual patient population and regimen, not just the medicine’s name.
Brentuximab vedotin plus AVD
Brentuximab vedotin is an antibody-drug conjugate directed at CD30. It delivers a cell-killing payload and is different from a PD-1 checkpoint inhibitor. In the ECHELON-1 trial of adults with previously untreated stage III or IV classic Hodgkin lymphoma, brentuximab-AVD improved long-term outcomes compared with ABVD, including overall survival in the reported follow-up.
This makes it an evidence-based option in appropriate settings, although treatment selection has continued to evolve. Peripheral neuropathy and low neutrophil counts are important practical considerations. Supportive medicines and monitoring form part of the regimen rather than optional extras. A result against ABVD cannot be assumed to establish superiority against every newer treatment. If this combination is proposed, ask why it fits your situation, what prevention of infection-related complications is planned, and how nerve symptoms will affect dose decisions.
BrECADD and more intensive approaches
Other advanced-stage pathways use different combinations and response-adapted schedules. The HD21 trial compared PET-guided BrECADD with escalated BEACOPP in eligible adults with advanced classic Hodgkin lymphoma. BrECADD contains brentuximab vedotin, etoposide, cyclophosphamide, doxorubicin, dacarbazine, and dexamethasone. The study reported less treatment-related morbidity and favorable disease control with BrECADD.
These results matter particularly in health systems that use intensive, PET-adapted treatment. They do not justify treating the regimen as interchangeable with nivolumab-AVD or applying it to everyone, including frail older adults. The trial populations, comparator treatments, and follow-up differ. Ask about expected hospital visits, blood-count support, infection precautions, fertility effects, and the scan-based rules for treatment duration. A shorter planned course is not necessarily less intensive, and the total burden depends on both the drugs and their schedule.
Lymphocyte-predominant disease follows a different pathway
Nodular lymphocyte-predominant Hodgkin/B-cell lymphoma often behaves more slowly than classic disease. Depending on stage, symptoms, and tumor burden, options may include observation in selected patients, localized radiation, or systemic therapy that includes an anti-CD20 antibody such as rituximab. Observation is an organized medical plan, not ignoring the disease.
The evidence base is smaller than for classic Hodgkin lymphoma, and treatment should be discussed by an experienced lymphoma team. Relapses can occur many years later. Some cases transform into an aggressive large B-cell lymphoma, which changes management. A new or rapidly growing node therefore may need another biopsy rather than automatic reuse of the original treatment. Long-term follow-up matters even after a prolonged remission. Ask which name your pathology service uses and whether the treatment recommendation specifically addresses this entity.
If classic Hodgkin lymphoma returns or resists treatment
Relapsed disease returns after an initial response; refractory disease does not respond adequately or progresses despite treatment. Neither term means that further useful treatment is impossible. The next plan depends on previous drugs, response duration, fitness, and whether a transplant strategy is appropriate.
Checkpoint inhibitors and antibody-drug conjugates are among the available tools. KEYNOTE-204 compared pembrolizumab with brentuximab vedotin in adults whose disease had returned after autologous transplantation or who were ineligible for it. Pembrolizumab improved progression-free survival in that study, with different toxicity considerations. These findings do not select a regimen for every relapse, especially when the person has already received one of these agents. Ask whether repeat tissue confirmation is needed, what the current treatment goal is, and how prior exposure affects the next choice.
Treatment to reach an autologous transplant
For suitable patients, second-line treatment aims to achieve a strong response before high-dose chemotherapy and autologous stem-cell rescue. “Autologous” means the stem cells come from the patient. The collected cells support blood-cell recovery after intensive treatment; the procedure is not the same as receiving a donor transplant.
A phase II study of pembrolizumab with gemcitabine, vinorelbine, and liposomal doxorubicin showed promising responses as a bridge to autologous transplantation. This is an example of an evolving salvage strategy, not a guarantee or a universal prescription. Small, nonrandomized studies have limitations, and contemporary choices depend heavily on earlier treatment. Ask how the team will measure response, when stem-cell collection would occur, what admission and recovery involve, and what alternatives remain if the response or fitness assessment does not support transplantation.
Older adults and people with other illnesses
Chronological age alone does not capture someone’s ability to tolerate treatment. Frailty assessment can reveal difficulties with mobility, everyday activities, nutrition, cognition, or support that a brief clinic conversation misses. These issues can affect both treatment risk and the help needed to complete therapy.
An otherwise independent older person and a younger person with serious organ disease may need very different plans. Discuss recent falls, trouble managing medicines, weight loss, and dependence on others for transport or meals. Such information should guide supportive care and shared decisions, not be hidden out of fear that treatment will be withheld. Ask which parts of a standard regimen remain appropriate, what modifications are proposed, and how those modifications might affect disease control. Reassessment during treatment is useful because function can improve or deteriorate.
Pregnancy requires coordinated specialist decisions
A diagnosis during pregnancy requires an individualized plan involving lymphoma and maternal–fetal medicine specialists. Disease urgency, pregnancy stage, imaging choices, and the pregnant person’s preferences all matter. The usual pathway for a nonpregnant adult should not simply be transferred unchanged.
Some slowly progressing presentations can be closely monitored for a period, while symptomatic or aggressive disease may require treatment during pregnancy. The risks of particular medicines and radiation differ by timing and exposure. MRI may be preferred for aspects of staging to avoid ionizing radiation. These are specialist decisions; do not postpone urgent assessment or assume that every treatment must wait until delivery. Tell the team promptly about pregnancy or a possible pregnancy before imaging or medicines are given. Ask for a clear explanation of maternal benefits, fetal uncertainties, and the alternatives being considered.
Discuss fertility before the first treatment
Fertility should be discussed before potentially damaging treatment, including when someone is uncertain about future parenthood. Options may include sperm banking, egg or embryo freezing, and ovarian tissue preservation in suitable circumstances. An urgent referral can clarify what is feasible without an unsafe delay in cancer care.
Risk varies with age, pretreatment fertility, and the drugs and radiation fields proposed. A regular menstrual cycle after therapy does not by itself prove that reproductive potential is unchanged. Fertility counseling can remain useful during survivorship, not just before treatment. Ask about costs, storage, timing, and the realistic limitations of preservation. Also ask for drug-specific advice about contraception and when trying to conceive may be appropriate. Fertility-preservation measures and contraception serve different purposes, and neither should be assumed to cover the other.
Safety during treatment: fever needs urgent attention
Chemotherapy can reduce infection-fighting white cells, allowing an infection to become serious quickly. Fever may be the only early sign. If you cannot reach the treatment service, seek urgent medical assessment and tell staff that you are receiving chemotherapy. Keep the out-of-hours number and a working thermometer available.
Ask when your blood counts are expected to be lowest and what precautions apply to your regimen. Hand hygiene, careful care of cuts and catheter sites, and avoiding close contact with people who are ill can reduce exposure. These measures do not replace urgent assessment when fever develops.
Blood clots are another reason to act promptly
Cancer, some treatments, reduced mobility, and venous catheters can increase clot risk. New swelling, tenderness, warmth, or discoloration in one arm or leg should be reported promptly. A clot around a line may produce arm or neck symptoms; do not assume every swelling is an enlarged lymph node.
A clot that travels to the lungs can cause sudden breathlessness, chest pain that worsens with breathing, coughing blood, or a fast or irregular heartbeat. These symptoms need immediate medical attention. They cannot safely be distinguished at home from infection, drug-related lung inflammation, or other serious problems. Ask your team whether clot prevention is appropriate for your individual risk. Do not start aspirin or an anticoagulant on your own: bleeding risk and treatment-related low platelets can change what is safe.
Checkpoint inhibitors have distinctive side effects
Immune checkpoint treatment can cause the immune system to inflame healthy organs. Problems may involve the bowel, lungs, liver, hormone-producing glands, or other tissues. They can develop during therapy or after it has stopped, so a previous immunotherapy exposure remains relevant when new symptoms appear.
Report new or worsening diarrhea, blood in the stool, persistent abdominal pain, cough, breathlessness, severe weakness, unusual headaches, or other significant changes promptly. Some complications first appear on blood tests. The team may pause treatment or prescribe medicines that suppress excessive inflammation. Do not self-treat a persistent symptom while waiting for the next infusion. Tell emergency clinicians which checkpoint drug you received and when. People with autoimmune disease should discuss that history before treatment because it can affect both risk and management.
Report tingling and numbness early
Peripheral neuropathy can produce tingling, burning, numbness, altered temperature sensation, or weakness, commonly in the hands and feet. It may interfere with buttons, writing, balance, or walking. Nerve symptoms are worth reporting while they are still mild; waiting until they become disabling can make management more difficult.
Describe what you can and cannot do, not only whether the symptom hurts. The team can assess the cause and decide whether treatment adjustment, symptom relief, or rehabilitation is appropriate. Protect numb skin from burns and injury, use supportive footwear, and reduce trip hazards at home. If balance is affected, ask for help before a fall occurs. Recovery varies, and some symptoms persist after treatment, so ongoing assessment is useful. Do not assume a supplement advertised for nerves will be safe or effective.
Mouth care, swallowing, and hydration
Mouth soreness, ulcers, dry mouth, and swallowing discomfort can interfere with eating and drinking during treatment. They may also create opportunities for infection. Ask for a mouth-care plan before problems develop, especially if intensive chemotherapy or transplantation is planned.
Gentle oral hygiene and early reporting of pain can help the team address symptoms before intake falls substantially. Tell the service if you cannot drink enough, have painful swallowing, notice bleeding, or develop signs of infection. Dental procedures during periods of low blood counts may need coordination with oncology; do not schedule invasive work without discussing timing. Treatment may include pain control, infection assessment, and changes to food texture. The goal is to maintain comfort, nutrition, and hydration while identifying complications that need more than a home remedy.
Eating when treatment changes appetite
Nausea, altered taste, bowel changes, fatigue, and mouth discomfort can make usual meals difficult. Focus on maintaining adequate energy, protein, and fluid intake rather than following a restrictive “anti-cancer” diet. Smaller meals, manageable textures, and foods that are appealing on that day may be more practical than a rigid menu.
Ask for a dietitian if weight is falling, eating is painful, or you are struggling to meet needs. Tell the team about persistent vomiting, diarrhea, or constipation so the cause can be treated. Food-safety advice may change when immunity is reduced. Someone else can help by shopping, preparing tolerable meals, and keeping drinks accessible without pressuring you to eat large portions. Nutritional support is individualized: weight alone does not capture muscle loss, hydration, or the quality of intake.
Fatigue needs assessment as well as rest
Cancer-related fatigue can feel disproportionate to activity and may not resolve with a normal night’s sleep. It can be influenced by treatment, anemia, poor nutrition, disrupted sleep, emotional strain, and other medical problems. Tell the team when fatigue is new, severe, or changing rather than assuming it is unavoidable.
Management starts with looking for treatable contributors. Depending on health and blood counts, a tailored balance of light activity, rest, and energy conservation may be useful. Break tasks into smaller steps and prioritize activities that matter most. Ask family or friends for specific practical help, such as transport or meal preparation. Avoid comparing your recovery pace with someone else’s. If exhaustion is accompanied by breathlessness, fever, faintness, or another concerning symptom, follow the appropriate urgent-care advice instead of treating it simply as tiredness.
Vaccines and infection prevention after treatment
Vaccination planning depends on the treatment received and how well the immune system has recovered. Live vaccines are generally unsuitable during substantial immunosuppression. Non-live vaccines may be safe but generate a weaker response at certain times, and some doses may need repeating after immune recovery.
Give the oncology team your vaccination record and ask for a personalized plan rather than booking every overdue vaccine independently. Transplant recipients have additional revaccination requirements. Timing can differ after medicines that deplete B cells, so the date of the final treatment matters. Household vaccination can also help reduce exposure, but particular circumstances deserve professional advice. A vaccine does not eliminate the need to report fever or seek care for infection symptoms. Keep the eventual plan with your treatment summary so primary care and oncology can coordinate it.
Follow-up care: protecting long-term heart health
Some lymphoma treatments can affect the heart or blood vessels. Risk depends on the medicines and cumulative doses, radiation exposure, pre-existing cardiovascular disease, and other factors such as blood pressure and smoking. Baseline assessment helps the team identify who needs additional monitoring or cardiology input.
Report new exertional breathlessness, swelling, chest discomfort, or palpitations rather than assuming they are normal consequences of chemotherapy. After treatment, cardiovascular follow-up should be matched to the exposure and risk profile; a single schedule does not fit every survivor. Ask for the total anthracycline dose and any relevant heart exposure from radiation in your written treatment summary. Managing blood pressure, cholesterol, diabetes, and tobacco use remains worthwhile. These everyday preventive measures complement, rather than replace, surveillance for treatment-related complications.
Late effects and second-cancer screening
Survivorship care looks beyond recurrence. Some people develop thyroid problems, cardiovascular disease, fertility changes, or another cancer related partly to earlier treatment. The particular risks depend on exposure, age at treatment, and time since therapy. Historical studies often involved larger radiation fields or different drug combinations, so their risks cannot be transferred unchanged to modern care.
Ask which screening schedule applies to you, including whether prior chest radiation changes breast-screening recommendations. Keep a record of radiation fields, doses, chemotherapy, and transplant history. New symptoms should be assessed even years after treatment rather than automatically attributed to the old diagnosis. Follow-up is an opportunity to prevent and manage problems, not a prediction that complications will occur. Primary care and oncology should agree on who orders tests and who reviews the results.
Emotional recovery and practical support
Finishing treatment can bring relief alongside uncertainty. Fear before scans, changes in appearance, disrupted work, financial strain, and relationship difficulties can persist even when disease is controlled. Needing support does not mean someone is coping badly or should be more grateful for a favorable response.
Tell the team if anxiety, low mood, or sleep problems interfere with daily life. Counseling, peer support, rehabilitation, and practical advice can address different needs. A gradual return to work or study may be more manageable than an immediate return to the previous workload. Ask about help with transport, benefits, employment discussions, or caring responsibilities. A trusted person can attend appointments and help record the plan, but you should still have opportunities to discuss private concerns directly with the clinician.
Understanding prognosis without promises
Hodgkin lymphoma is often treatable with curative intent, but a population survival statistic cannot predict one person’s outcome. Statistics combine people with different ages, disease characteristics, health conditions, and treatments. They also describe patients diagnosed in earlier years, so they do not fully capture every recent therapeutic advance.
Five-year relative survival compares survival in people with the cancer with expected survival in a similar general population. It does not mean someone will live only five years, nor does it guarantee that a surviving person has no ongoing effects. For an individual discussion, ask which factors are most relevant now and how response to treatment changes the outlook. It is reasonable to request information in broad terms or as numerical estimates, depending on what helps you make decisions.
Supplements and complementary approaches
No complementary health approach has been shown to cure cancer or reliably replace lymphoma treatment. Some approaches may help with symptoms or wellbeing when used appropriately alongside medical care. Their purpose, evidence, and safety should be discussed separately from claims about controlling the cancer itself.
Tell the oncology pharmacist about herbs, vitamins, concentrated extracts, and other products, even if they are marketed as natural. Some can interact with treatment or cause toxicity. Do not delay biopsy or effective therapy while trying an unproven product. Activities such as adapted relaxation or mindfulness may be reasonable ways to manage distress, but physical practices may need modification for low blood counts, neuropathy, or fragile health. Ask what benefit is realistically expected and whether the approach has been evaluated for someone receiving your particular treatment.
Questions about clinical trials and your care plan
A clinical trial may be relevant at diagnosis or after relapse. Before joining, ask what question the study addresses, how treatment is assigned, what the standard alternative is, and which risks remain uncertain. Clarify additional visits, tests, travel, and potential costs. Informed consent is an ongoing discussion, not merely a signature.
You can ask for time to review the information, an interpreter, and an explanation of unfamiliar terms. Participation is voluntary, and the study team should explain withdrawal and what happens to subsequent care. Alongside trial questions, keep your own priorities visible: preserving function, future parenthood, work responsibilities, and acceptable treatment burden. Leave the consultation knowing the next step, who to contact for urgent problems, and when outstanding results will be reviewed. A clear, individualized plan is more useful than comparing isolated drug names online.
Related reading: sarcoidosis symptoms and organ involvement and cough causes and when to seek help.