

“Gluten allergy” can refer to different conditions. This guide explains their symptoms, testing and care. [1]
What does “gluten allergy” actually mean?
“Gluten allergy” is a common search phrase, but it does not name one precise diagnosis. Wheat allergy, coeliac disease and non-coeliac gluten sensitivity describe different problems, even though the same meal may appear in someone’s account of their symptoms. Wheat allergy involves a reaction to wheat proteins; gluten is only part of the protein content of wheat. A precise diagnosis helps identify the relevant foods and investigations. Start by describing what happened after eating, rather than deciding the mechanism from the food alone. [1]
Where gluten is found
Gluten is found in wheat, barley and rye and in foods made from them. Bread and pasta are familiar examples, but ingredients in sauces, soups, processed foods and other products also need attention when a gluten-free diet is medically required. This does not mean every food in those categories contains gluten: the actual ingredients and preparation matter. Many foods, including unprocessed fruit, vegetables, eggs and plain meat, are naturally gluten free. A processed version of an otherwise suitable food may have added ingredients that change the answer. Distinguish the basic food from the finished product, and ask a dietitian how to check foods that you use regularly. Removing gluten is a treatment for particular conditions, rather than a general measure that everyone needs for better health. A restrictive diet without a medical reason can make nutrition harder to manage. [2]
Wheat allergy and rapid reactions
Food allergy occurs when the immune system reacts to a food protein. In an immediate allergic reaction, symptoms can include an itchy mouth, hives, swelling, vomiting, wheezing or other breathing problems. Several body systems may be involved at once. The relationship between eating and symptoms is useful information, but timing alone cannot confirm which ingredient caused the reaction. A meal usually contains more than one food, and sauces or coatings may introduce ingredients that are easy to overlook. An allergist considers the whole episode, previous reactions and relevant test results. Keep packaging or an ingredient list when it is available, without delaying urgent care. Do not deliberately repeat the meal to see whether the reaction happens again. A previous episode that seemed manageable is not a reliable guide to how a future exposure will behave. [3]
When to treat a reaction as an emergency
Anaphylaxis is a rapidly developing, life-threatening allergic reaction. Warning signs include swelling of the tongue or throat, difficulty breathing, a hoarse voice, trouble swallowing, marked dizziness, fainting or collapse. A rash may occur, but waiting for skin symptoms can delay help. Use prescribed adrenaline according to the person’s emergency instructions and call the local emergency number. Do not wait to see whether an antihistamine settles breathing or circulation problems. Emergency assessment is needed even if symptoms begin to improve. Follow the emergency operator’s instructions. Do not let the person stand or walk around. [4]
Coeliac disease is a different immune condition
Coeliac disease, also spelled celiac disease, is an autoimmune condition triggered by gluten. The immune response damages the lining of the small intestine, where nutrients are absorbed. It is not the same process as an immediate wheat allergy, and it should not be described as an allergy that simply becomes more severe with time. Treatment and follow-up address intestinal recovery and the consequences of poor nutrient absorption. A person can have digestive symptoms, effects elsewhere in the body or relatively few obvious symptoms. Because the mechanism differs, an allergy blood test is not a substitute for coeliac testing. Equally, a coeliac diagnosis does not explain a sudden episode of throat swelling or collapse after a meal. Such an episode needs its own emergency assessment rather than being attributed to an established digestive diagnosis. [5]
Symptoms can extend beyond the gut
Coeliac disease can cause bloating, abdominal pain, diarrhoea, constipation, nausea and stools that are loose or greasy. The pattern is variable; a person does not need to have every digestive symptom. Fatigue, mouth problems, bone or joint discomfort and other symptoms may occur outside the digestive system. In children, poor nutrient absorption can interfere with growth and development, so faltering growth or delayed puberty deserves clinical attention. Some people develop dermatitis herpetiformis, an intensely itchy blistering rash commonly affecting areas such as the elbows, knees or buttocks. The rash requires professional assessment rather than comparison with an online photograph. Record digestive and non-digestive concerns together when describing the problem. A symptom list can help a clinician decide what to investigate, but none of these features alone proves that gluten is responsible. [6]
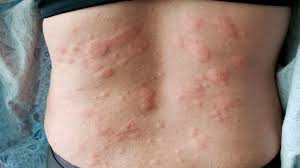
Mild symptoms do not settle the diagnosis
The visibility of symptoms does not tell the whole story in coeliac disease. Some people have mild symptoms or none that they recognise, yet treatment is still recommended because complications can occur. Others have symptoms that resemble more common digestive problems and do not immediately connect them with a long-term condition. For that reason, feeling fairly well after a particular meal cannot establish that an exposure is harmless in someone with diagnosed coeliac disease. Nor does feeling unwell after bread establish the diagnosis in someone who has not been tested. These are different questions: what condition is present, and how is a confirmed condition being managed? Keeping them separate avoids using day-to-day sensations as the only measure of intestinal health or as a replacement for a proper diagnostic assessment. [7]
Family history and associated conditions
Coeliac disease can occur at different ages, and a close family history makes it more likely. Certain other conditions, including type 1 diabetes, are also associated with a higher chance of coeliac disease. Tell the clinician about a parent, sibling or child with a confirmed diagnosis, rather than assuming that relatives all need to adopt the same diet. A family pattern is a reason to discuss assessment; it is not proof that every relative has the disease. Some people are identified through testing prompted by risk factors instead of prominent bowel symptoms. Bring any previous results and explain why they were performed. This helps the healthcare team distinguish a confirmed diagnosis from a past suggestion, a screening result or an informal family description. Individual testing decisions depend on the clinical context. [8]
Non-coeliac gluten sensitivity and uncertainty
Non-coeliac gluten sensitivity describes symptoms associated with gluten-containing foods when coeliac disease and wheat allergy have been excluded. There is no single established routine test that confirms it. Researchers are still investigating the causes, and components of wheat other than gluten may contribute to symptoms in some people. Improvement after removing bread is therefore meaningful as an observation, but it cannot identify the responsible ingredient on its own. The assessment should first consider conditions with established diagnostic pathways, rather than assigning sensitivity immediately. A clinician or dietitian can help decide whether any dietary evaluation is appropriate and how to protect nutritional adequacy. [9]
| Condition | Main distinction | Assessment emphasis |
|---|---|---|
| Wheat allergy | Allergic reaction to wheat proteins | Reaction history and specialist allergy assessment [3] |
| Coeliac disease | Autoimmune response involving the small intestine | Coeliac investigations and appropriate follow-up [5] |
| Non-coeliac gluten sensitivity | Symptoms without confirmed coeliac disease or wheat allergy | Exclusion of those conditions; no established routine confirming test [9] |
Other explanations for symptoms after meals
Irritable bowel syndrome, or IBS, involves recurring abdominal pain with changes in bowel movements, such as diarrhoea, constipation or both. It is a disorder of gut-brain interaction, and the symptoms occur without visible signs of damage or disease in the digestive tract. This differs from the intestinal injury associated with coeliac disease. Symptoms can overlap enough that a person cannot reliably distinguish the conditions from a short checklist. An IBS assessment may therefore include consideration of other causes before a treatment plan is agreed. A meal contains many possible influences, so a symptom after eating wheat does not automatically isolate gluten as the cause. Describe the bowel pattern, how long it has been present and the effect on everyday activities. Avoid replacing assessment with several simultaneous food exclusions, which can make the pattern harder to interpret. [10]
Lactose intolerance is another distinct possibility
Lactose intolerance can cause bloating, gas, abdominal pain and diarrhoea after lactose, the sugar in milk and some dairy products. The problem is incomplete digestion of lactose, rather than an allergic response to wheat or an autoimmune response to gluten. Someone may wrongly focus on bread when a meal also contains milk, cream or another relevant ingredient. That example illustrates why the full meal matters; it is not a reason to remove dairy automatically. Lactose intolerance is also different from milk allergy, which involves the immune system. A healthcare professional can assess the history and whether testing or dietary support would be useful. If dairy intake needs adjustment, nutrition should remain part of the plan. The diagnosis should explain the symptoms while preserving foods the person can safely and comfortably eat. [11]
Digestive warning signs need medical assessment
A suspected food sensitivity should not become an explanation for every new digestive symptom. Unexplained substantial weight loss, rectal bleeding or bloody diarrhoea, or a persistent abdominal swelling or lump require urgent medical assessment. Do not wait to see whether removing another food makes these changes disappear. Tell the service what has changed and when it began, including any existing diagnosis or recent test results. A familiar pattern of bloating is different from a new warning sign, even when both occur after meals. Seeking assessment does not mean that a serious condition is certain; it means the symptom needs investigation instead of an assumption about its cause. [28]
Plan coeliac testing before changing the diet
Speak with a clinician before starting a gluten-free diet for suspected coeliac disease. Coeliac tests can become less informative after gluten has been removed from the diet. Tell the clinician whether you currently eat gluten, how your eating has changed and whether any food has caused an immediate reaction. Blood tests, intestinal samples and sometimes other investigations are interpreted in that context. This is not advice to keep eating a suspected allergen or to restart gluten independently. If you are already avoiding it, ask for an individual testing plan; do not attempt a home gluten challenge. Possible wheat allergy needs particular caution because re-exposure can cause a dangerous reaction. A clinician may need to coordinate allergy and digestive assessment. [12]
What coeliac blood tests look for
Coeliac blood tests look for particular antibodies, rather than measuring whether someone is generally “sensitive” to food. Tissue transglutaminase IgA, often written tTG-IgA, is commonly used. The amount of total IgA can matter because IgA deficiency may make an IgA-based test less reliable. Clinicians may choose other antibody tests in that situation. The meaning of a result depends on the test, laboratory reference range, clinical history and circumstances of testing. A positive result is a reason for appropriate diagnostic follow-up, not a reason to interpret every later symptom as coeliac disease. A negative result may also need further consideration when clinical suspicion remains. Ask which test was performed and what the next step is, rather than comparing numbers from different laboratories or treating a single result as a complete explanation of health. [13]
Why a specialist may recommend a biopsy
Some people need an examination of the small intestine to help confirm coeliac disease. During an upper endoscopy, a thin flexible instrument passes through the mouth so that a specialist can obtain small samples of the intestinal lining. The samples are examined for changes consistent with the condition. Whether a biopsy is needed depends on the individual pathway and specialist assessment; this guide cannot decide that from an antibody result. The appointment should explain preparation, comfort measures and how results will be communicated. Further blood tests may assess iron and other nutrients when coeliac disease is identified. A skin biopsy may be relevant if dermatitis herpetiformis is suspected. These investigations answer different questions, so it is reasonable to ask what each proposed test is intended to establish and how the answer would change care. [14]
Allergy testing starts with the reaction history
An allergy assessment begins with questions and an examination, followed by tests selected for the suspected problem. Skin tests and blood tests can help investigate particular allergens, but their results need interpretation alongside the history. A test result should not be treated as a standalone list of foods that must be removed. Tell the specialist about the exact symptoms, their timing, previous exposures, relevant medicines and any existing allergic conditions. Bring previous test reports rather than only a summary that a test was “positive.” This allows the clinician to see what was actually measured. Testing should be performed and interpreted through an appropriate healthcare service. Broad screening without a clear clinical question can lead to confusing results and unnecessary changes in eating. The aim is to identify a clinically meaningful allergy and a proportionate management plan. [15]
An oral food challenge is a medical procedure
Sometimes an allergist recommends an oral food challenge to clarify whether a food causes an allergic reaction or whether an established allergy has changed. The procedure takes place under medical supervision, with trained staff observing for symptoms and treatment available if needed. It is not equivalent to trying a small bite at home. The clinical team assesses suitability, explains preparation and decides how to respond to symptoms. Do not copy a protocol found online, change medicines to prepare on your own or use a previous mild reaction as reassurance that a challenge will be safe. Any later dietary change should follow the team’s instructions. [16]
Why commercial food sensitivity panels can mislead
Commercial IgG food panels are often marketed as a quick route to identifying many problem foods. Professional allergy organisations advise against using these panels to diagnose food allergy or food intolerance. IgG antibodies to foods can reflect ordinary exposure, and the presence of an antibody does not establish that the food is causing symptoms. A long list of flagged ingredients can seem persuasive while answering the wrong clinical question. Removing them all may create unnecessary restrictions without finding the cause of the original problem. Ask a qualified clinician what a proposed test can reliably diagnose and how a result would alter management. Established coeliac antibody testing and specialist allergy testing have specific uses; the fact that they involve antibodies does not validate every commercial antibody panel sold for food sensitivity. [17]
Management after a wheat allergy diagnosis
A confirmed food allergy needs a plan covering avoidance, recognition of reactions and what to do if exposure occurs. The healthcare team may prescribe emergency treatment and explain how to use it. The details depend on the diagnosis and the person’s circumstances. Share the agreed plan with relevant carers or staff who may need to respond, and make sure they understand where prescribed equipment is kept. Read food information consistently and ask about ingredients when another person prepares a meal. Follow-up is useful because the plan may need adjustment as circumstances change. If a child has an allergy, communication between home, school and other carers should be practical and clear. Do not change an avoidance plan or test whether the allergy has resolved by offering the food again without specialist direction. [18]
Treatment after a coeliac diagnosis
For coeliac disease, treatment centres on a gluten-free diet that allows the intestine to heal and helps prevent further damage. The dietary change is lifelong, and the healthcare team should provide support with implementation and follow-up. Some people improve relatively quickly while intestinal recovery takes longer; the absence of an immediate change does not justify abandoning the treatment plan. A clinician may address nutritional deficiencies or other problems identified during assessment. Supplements are not a substitute for identifying the cause of a deficiency, and individual treatment should follow professional advice. Be cautious about products claiming to let someone with coeliac disease eat gluten safely. Discuss any proposed supplement or alternative approach with the treating team rather than using it to replace established care. Continuing symptoms deserve review, not a promise that one product will cure the condition. [19]
A dietitian can make the plan workable
A dietitian can translate a coeliac diagnosis into meals, shopping habits and food preparation that fit everyday life. Useful discussions include the foods you normally eat, cooking facilities, cultural preferences, budget and any other dietary needs. The aim is to remove the medically relevant source of harm while maintaining adequate energy and nutrients. An explanation that only lists forbidden foods leaves many practical questions unanswered. Ask about suitable replacements, packaged ingredients and how to manage situations in which someone else cooks. Follow-up offers a chance to review symptoms and areas of uncertainty after the first appointments. It can also identify when further specialist advice is needed. A plan should remain understandable and realistic as school, work or living arrangements change, rather than relying on a single handout given at diagnosis. [20]
Gluten free still needs to be nutritionally balanced
A gluten-free label does not describe the overall nutritional quality of a food. A balanced pattern still includes a range of suitable starchy foods, fruit, vegetables, protein sources and other foods that meet individual needs. Rice, potatoes and appropriate gluten-free grains can provide alternatives to familiar wheat-based staples. Packaged substitute products differ in fibre, fat, sugar and salt, so comparing the nutrition information can be useful once suitability has been established. There is no need to assume that every meal requires a specialist replacement product. Equally, convenience foods may help someone maintain a practical routine. Discuss combinations of restrictions, such as a vegetarian or vegan diet alongside coeliac treatment, with a dietitian if meeting nutritional needs is becoming difficult. The purpose is a varied and adequate diet that can be sustained. [21]
Pay attention to fibre when replacing grains
Removing wheat, barley and rye can reduce fibre intake if the replacement foods are mainly refined starches. Fibre is present in plant foods such as fruit, vegetables, pulses and suitable wholegrains. A wholegrain includes the different parts of the grain, whereas refining removes some of them. This helps explain why two products that both meet gluten-free requirements may contribute different amounts of fibre. The ingredients list and nutrition information answer different questions: one helps identify what is in a product, while the other helps compare its nutritional contribution. A dietitian can help select suitable fibre sources around any symptoms and other medical needs. Avoid responding to a dietary problem by assuming that all carbohydrate foods are unsuitable. The useful task is to replace lost sources thoughtfully while keeping the overall eating pattern balanced. [22]
United States labels: gluten free and wheat free differ
In the United States, FDA rules define the voluntary gluten-free claim for foods within the agency’s scope. Among the requirements, unavoidable gluten must be below twenty parts per million. The claim can also appear on a food containing a wheat-derived ingredient that has been processed to remove gluten, provided the applicable requirements are met. That distinction matters for wheat allergy: a gluten-free claim does not automatically establish that a product is suitable for someone allergic to wheat proteins. Read the ingredient and allergen information and follow the allergy team’s guidance. Conversely, avoiding wheat alone does not remove every source of gluten relevant to coeliac disease. These are United States rules, not a universal description of food law. [23]
United States allergen information needs its own check
For packaged foods covered by United States federal allergen-labelling requirements, wheat is one of the major food allergens that must be identified. Information may appear within the ingredient list or in a separate “Contains” statement. Check the current package rather than relying on an old photograph, an earlier purchase or the appearance of a brand. Manufacturers may change ingredients, and similar products can have different formulations. Precautionary statements such as “may contain” have a different role from an ingredient declaration; do not assume their absence guarantees that cross-contact cannot occur. Ask the manufacturer or your allergy professional when information is unclear. Label-reading is one part of a food-allergy plan, alongside communication and emergency preparedness. Requirements vary across countries and types of food, so advice about a particular label should name the jurisdiction it concerns. [24]
Oats require a more specific answer
Oats contain avenin, a protein related to gluten, and most people with coeliac disease can tolerate oats that are labelled gluten free. Ordinary oats may be contaminated with wheat, barley or rye during production, so “oats” on an ingredient list does not by itself settle suitability for a coeliac diet. A small number of people with coeliac disease also react to gluten-free oats. If symptoms persist or there is uncertainty about including them, discuss the issue with the healthcare team rather than assuming that all oats are interchangeable. This guidance concerns coeliac disease and should not be used to decide safety for a separate oat or wheat allergy. The important distinction is between the grain itself, contamination during handling and an individual’s clinical circumstances. A dietitian can help interpret those factors together. [25]
Reducing gluten transfer in a shared kitchen
For someone following a gluten-free diet for coeliac disease, cross-contact means gluten reaches food that would otherwise be suitable. Crumbs in shared spreads, a toaster used for ordinary bread or oil used for coated foods can create avoidable problems. Clean work surfaces, pans and utensils before preparing the gluten-free meal. Ordinary washing with detergent or a dishwasher removes gluten from washable equipment; replacing an entire kitchen is not automatically necessary. Separate spreads, clean cutlery and toaster bags or a separate toaster are practical options depending on the household. Explain the reason for the routine to anyone preparing food so that a clean utensil is not immediately returned to a shared source of crumbs. Choose arrangements that everyone can understand and maintain. Advice for an additional food allergy should also follow that person’s specific clinical plan. [26]
Eating out: ask about preparation as well as ingredients
A restaurant conversation works best when the requirement is specific. For coeliac disease, tell staff that the meal needs to meet a medical gluten-free requirement, and ask how cross-contact is controlled. Contacting the venue ahead of time may make it easier to speak with a manager or chef. Ask about shared fryers, cooking utensils and how the correct dish will be identified when served. A menu description provides a starting point, but it does not answer every question about preparation. Confirm the meal when it arrives and do not eat it if uncertainty remains. Staff should understand the diagnosis that is relevant to the order, especially when wheat allergy and coeliac disease would require different checks. Clear communication is more useful than relying on a broad phrase that different people may interpret differently. [27]
Follow-up checks more than symptom frequency
Ongoing review is part of coeliac care. NICE’s United Kingdom quality standard recommends an annual review to discuss symptoms, the gluten-free diet and any additional support required. Weight and height may be reviewed, with attention to growth and development in children. The discussion can identify a need for further nutritional advice, assessment of possible complications or referral to another professional. A review is also an opportunity to raise practical difficulties before they become a reason to abandon the diet. Explain whether the plan works at home, school or work and whether access to suitable food has changed. Care arrangements differ between health systems, so confirm with your own team how follow-up is organised. Keep copies of important results and ask whom to contact when new concerns arise between routine appointments. [29]
Persistent symptoms need reassessment
Symptoms that continue after a coeliac diagnosis do not automatically mean that treatment has failed or that the disease is refractory. A specialist may review the original diagnosis, assess possible ongoing gluten exposure and consider other explanations such as IBS or lactose intolerance. Further investigation depends on the findings. Refractory coeliac disease is rare and requires specialist evaluation; it is not a label to adopt from symptoms alone. Tell the team about the pattern of difficulties without feeling that the discussion is a test of how well you have behaved. Unintentional exposure can be hard to identify, and a dietitian may help find a practical solution. Do not keep adding new food exclusions while the cause remains uncertain. Reassessment should aim to identify what is happening and provide targeted support while maintaining the established coeliac treatment plan. [30]
Why nutritional and bone health matter
Untreated coeliac disease can interfere with absorption of nutrients and lead to problems such as iron deficiency anaemia, other vitamin deficiencies and weakened bones. These effects help explain why care includes more than relief of abdominal discomfort. A clinician may assess nutritional status and decide whether additional investigation or treatment is needed. Rare serious complications exist, but a list of possible outcomes is not a forecast for an individual. Most people with coeliac disease do not develop the cancers associated with the condition. Ask the healthcare team which risks are relevant to your circumstances and how ongoing care addresses them. Avoid interpreting tiredness, a single laboratory result or a new symptom as proof of a complication. Each needs assessment in context, with attention to both coeliac disease and other possible explanations. [31]
Prepare a clear account for the appointment
A useful appointment starts with a short account of the main concern and the questions that matter most. Note when symptoms began, what happens during an episode, how long it lasts and whether there are symptoms outside the digestive system. Bring a list of medicines and supplements, relevant test results and information about foods already avoided. Ask what the working diagnosis is, what the proposed tests can show and what to do while waiting for results. Clarify how results will arrive and which changes need urgent help. If the explanation is unclear, ask for it in different words or request a written summary. A trusted person can help take notes if wanted. Preparing this information should make assessment easier, but it must never delay emergency care for a serious reaction. [32]
Frequently asked questions
Is gluten allergy the same as wheat allergy?
No. “Gluten allergy” is imprecise; wheat allergy, coeliac disease and non-coeliac gluten sensitivity require different assessment and care. [1]
When does a possible food reaction need emergency help?
Breathing difficulty, throat or tongue swelling, fainting or collapse need emergency help. Use prescribed adrenaline as instructed and call the local emergency number. [4]
Should I restart gluten before coeliac testing?
Ask your clinician for an individual testing plan. Do not restart gluten or attempt a home challenge, especially if allergy is possible. [12]
Is there a blood test for non-coeliac gluten sensitivity?
There is no established routine test that confirms it. Assessment first excludes coeliac disease and wheat allergy. [9]
Can I check a wheat allergy by eating a small amount?
No. An oral food challenge is a medically supervised procedure, not a home test. Follow an allergy specialist’s instructions. [16]
Are gluten-free products always suitable for wheat allergy?
No. Under United States FDA rules, some gluten-free foods may contain specially processed wheat ingredients. Check suitability for your specific allergy. [23]
Sources
- ACAAI. Wheat & Gluten Allergy.
- NIDDK. Eating, Diet, & Nutrition for Celiac Disease.
- AAAAI. Food Allergy.
- NHS. Anaphylaxis.
- NHS. Coeliac disease.
- NIDDK. Symptoms & Causes of Celiac Disease.
- NHS. Coeliac disease: Symptoms.
- NIDDK. Definition & Facts for Celiac Disease.
- Coeliac UK. Non coeliac gluten sensitivity.
- NIDDK. Definition & Facts for Irritable Bowel Syndrome.
- NIDDK. Definition & Facts for Lactose Intolerance.
- NIDDK. Diagnosis of Celiac Disease.
- NIDDK. Celiac Disease Tests.
- NHS. Coeliac disease: Diagnosis.
- AAAAI. Allergy Testing.
- AAAAI. What You Need to Know About Oral Food Challenges.
- AAAAI. The Myth of IgG Food Panel Testing.
- NHS. Food allergy.
- NIDDK. Treatment for Celiac Disease.
- NHS. Coeliac disease: Treatment.
- Coeliac UK. Keeping a balanced gluten free diet.
- Coeliac UK. Fibre and the gluten free diet.
- FDA. Questions and Answers on the Gluten-Free Food Labeling Final Rule.
- FDA. Food Allergies.
- Coeliac UK. Oats and the gluten free diet.
- Coeliac UK. Cross-contamination.
- Coeliac UK. Tips for eating out when following the gluten free diet.
- NHS. Symptoms of IBS.
- NICE. Coeliac disease: Quality statement 5, Annual review.
- Coeliac UK. Non responsive and refractory coeliac disease.
- NHS. Coeliac disease: Complications.
- NHS. What to ask your doctor or other healthcare professional.





