

Sources checked on 9 October 2026. This guide explains symptom patterns, clinical assessment and practical questions for everyday life. Our overview of wheat allergy and gluten-related conditions explains the broader care context.
What people mean by gluten allergy symptoms
People searching for gluten allergy symptoms are often describing a real reaction to bread, pasta or another wheat-containing food. However, “gluten allergy” is an imprecise label. Wheat allergy involves an allergic immune response to wheat proteins, which can include gluten proteins. Coeliac disease, also spelled celiac disease, is an autoimmune condition triggered by gluten in wheat, barley and rye. Non-coeliac gluten or wheat sensitivity describes symptoms considered after coeliac disease and wheat allergy have been appropriately excluded. These conditions can share digestive complaints, but their risks, tests and management differ. A symptom checklist cannot determine which explanation applies, and a negative wheat-allergy test does not exclude coeliac disease. [2]
Before starting a gluten-free diet, discuss diagnostic testing with a healthcare professional. Removing gluten can make coeliac blood tests and intestinal biopsies harder to interpret. If you have already changed your diet, tell the clinician what changed and when, rather than assuming a negative result reliably settles the question. [3]
There is an essential safety exception to advice about eating gluten for testing: never deliberately reintroduce a food that may have caused an allergic reaction without a plan from your clinical team. An oral food challenge is a medical procedure, with trained staff, observation and facilities to treat a serious reaction. Clinicians select the setting and decide when testing should stop. Trying another portion at home cannot provide the same information safely. This also applies when an earlier reaction seemed mild or a blood result looks reassuring. Clarify the allergy risk before discussing any coeliac-related gluten challenge. [4]
Symptoms that need emergency attention
Sudden breathing difficulty, throat or tongue swelling, collapse or marked faintness after food can signal anaphylaxis. A rapidly developing reaction affecting several body systems, such as hives together with breathing problems, also needs emergency attention. Anaphylaxis can occur without a rash, so waiting for visible skin changes is unsafe. Call your local emergency number immediately. Follow your prescribed emergency plan while help is arranged. This is a reason for immediate help, not an opportunity to decide whether the trigger was wheat, gluten or another ingredient. [5]
Recognising a possible wheat-allergy pattern
Wheat allergy may cause raised itchy hives, swelling, nasal symptoms, wheezing, stomach cramps, vomiting or diarrhoea. Symptoms can affect more than one part of the body, and their intensity can vary between reactions. A repeatable pattern after eating wheat raises suspicion, but it does not establish the diagnosis: a mixed meal contains several possible triggers. The exact food, how it was prepared and what happened afterward all matter. Allergic reactions commonly develop soon after exposure, usually within minutes to a few hours. A previous mild episode does not guarantee that another exposure will also be mild. [6]
Occasionally, a wheat-related allergic reaction appears only when another factor is present. Wheat-dependent exercise-induced anaphylaxis is one example; omega-5 gliadin is an important wheat allergen in this setting. A UK study of 132 affected adults documented exercise, alcohol and some anti-inflammatory medicines as accompanying factors, while some people had no identifiable cofactor. This helps explain why reactions can seem inconsistent across otherwise similar meals. It does not mean exercise is necessary in every case or that a particular waiting interval makes wheat safe. Report the surrounding circumstances to an allergist, and never try to reproduce such a reaction yourself. [7]
Coeliac symptoms can extend beyond the gut
Coeliac symptoms may include bloating, persistent diarrhoea, constipation, abdominal pain, nausea or greasy stools. Fatigue and mouth problems can accompany digestive symptoms or draw attention first. Children may have slow growth, poor weight gain or delayed puberty. Some people have few noticeable symptoms despite intestinal injury. Neither the absence of diarrhoea nor feeling well after one wheat-containing meal reliably excludes the condition. [3]
Persistent unexplained symptoms deserve assessment even when they are not dramatic. NICE recommends considering coeliac testing in situations including prolonged fatigue, unexpected weight loss, persistent mouth ulcers and unexplained iron, folate or vitamin B12 deficiency. Testing is also relevant for first-degree relatives of someone with coeliac disease and for certain associated conditions, including type 1 diabetes and autoimmune thyroid disease. These are reasons to discuss testing, not proof that gluten explains the problem. For example, unexplained iron deficiency warrants investigation of its cause rather than simply buying gluten-free food. Tell your clinician about family diagnoses even if your own symptoms seem different. [8]
Normal growth does not completely rule out coeliac disease in a child. In the prospective TEDDY study, many young children identified through screening had no obvious symptoms and were growing normally. The children were selected for genetic risk, so the findings do not tell every family to arrange screening independently. They do show why a clinician may recommend testing based on a child’s risk factors even without the stereotypical combination of a swollen abdomen, diarrhoea and poor weight gain. A child’s full growth record, family history and relevant laboratory results are more informative than appearance alone. [9]
Symptoms are also an imperfect guide after coeliac disease has been diagnosed. In a small study of treated adults, researchers compared detailed food sampling and gluten measurements with participants’ reports; many detected exposures had not produced a noticeable or suspected reaction. This does not mean every stomachache represents gluten exposure, nor does it establish a safe amount for an individual. It shows why “I would feel it if I ate gluten” is unreliable. Symptom changes can be useful information for follow-up, but they cannot by themselves confirm what was eaten or whether the intestine has recovered. [10]
Hives and dermatitis herpetiformis are different
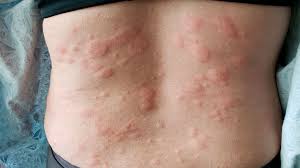
The word rash covers different skin problems. Hives, or urticaria, are raised, itchy swellings that usually change or fade, with an individual wheal generally disappearing within a day. They can occur during an immediate allergic reaction, but recurring hives do not automatically mean food allergy. The 2026 international urticaria guideline notes that IgE-mediated food allergy is very rarely the underlying cause of chronic spontaneous urticaria. Photographs and a description of how long each patch lasts can help a clinician assess the pattern. A rash image online cannot establish its cause. [11]
Dermatitis herpetiformis is a different, intensely itchy skin manifestation associated with coeliac disease. Small blisters or scratched bumps often occur symmetrically, particularly around the elbows, knees and buttocks; scratching may obscure the original blisters. Some affected people have little digestive discomfort. Diagnosis generally involves a dermatologist arranging a skin sample from suitable skin next to a lesion for direct immunofluorescence, which looks for characteristic antibody deposits. The placement and interpretation of that sample matter. Neither an itchy elbow nor improvement after avoiding bread confirms dermatitis herpetiformis, and its autoimmune mechanism differs from an immediate IgE-mediated wheat reaction. [12]
What wheat-allergy tests can and cannot show
An allergist starts with the reaction history and then chooses tests that address a specific suspicion. Skin-prick testing and blood tests for wheat-specific IgE can show sensitisation: the immune system recognises a protein. Sensitisation does not necessarily mean that eating the food causes symptoms. Results therefore need interpretation alongside the history, and test performance is less straightforward for wheat than for some other foods. In selected cases, tests for particular wheat proteins or a medically supervised food challenge clarify the picture. A large number on a report is not a dependable forecast of how severe the next reaction will be. [13]
Cross-sensitisation can complicate wheat testing. In a UK birth-cohort study, sensitisation to grass pollen and wheat frequently overlapped, while confirmed wheat allergy was much less common. Related proteins can therefore help produce a positive test without proving that wheat in food is the cause of a person’s symptoms. This is one reason an isolated result should not trigger an expanding list of forbidden foods. It also explains why an allergist asks about hay fever and the actual eating history. The study cannot calculate your individual likelihood of allergy; that judgment requires a clinical evaluation. [14]
Commercial food-sensitivity panels measuring IgG antibodies are a different issue. AAAAI advises against using these panels to diagnose food allergy or intolerance because their claimed diagnostic role is not established; food-specific IgG can reflect ordinary exposure or tolerance. A long colour-coded list is not evidence that every highlighted food needs removing. This warning should not be confused with targeted IgG-based tests used in some coeliac investigations, which answer a different question. Ask what a proposed test measures, which condition it can identify and how the result would change care. An expensive panel is not necessarily a useful one. [15]
How coeliac blood tests fit into diagnosis
Coeliac testing commonly starts with tissue transglutaminase IgA, usually abbreviated tTG-IgA or TG2-IgA, together with total IgA. Total IgA helps identify people whose low IgA could make an IgA-based result misleading. In that situation, clinicians may use coeliac-specific IgG tests, such as deamidated gliadin peptide IgG or tTG-IgG. Routine IgG testing in someone with adequate IgA is not an interchangeable substitute. The results also depend on gluten exposure and the clinical circumstances. Persisting concern despite a negative initial test warrants review of those circumstances and possible specialist investigation; it does not automatically establish sensitivity or rule out every intestinal condition. [16]
Why biopsy advice differs between countries and ages
United States: biopsy usually confirms diagnosis
Confirmation depends partly on age and the guideline followed locally. In the United States, the 2023 American College of Gastroenterology guideline generally recommends upper endoscopy with multiple small-intestinal biopsies when coeliac disease is suspected. It describes a narrower option for symptomatic adults who cannot or will not undergo endoscopy: very high tTG-IgA, above ten times the laboratory’s upper limit, plus a positive endomysial IgA antibody in a separate sample may support a diagnosis of likely coeliac disease. That qualified exception is not the same as declaring that every positive blood test makes an endoscopy unnecessary. [17]
Europe: selected adults younger than 45
European adult guidance changed in 2025. The European Society for the Study of Coeliac Disease conditionally permits diagnosis without intestinal biopsy in selected adults younger than 45 whose initial IgA anti-TG2 is at least ten times the assay’s upper limit of normal. Coeliac serology must be confirmed in a second blood sample while the person remains on a gluten-containing diet. The decision belongs in specialist care and requires discussion of the benefits and limitations. This route is unsuitable when warning signs suggest another condition, such as gastrointestinal bleeding, swallowing difficulty or obstruction. The criteria are not a reason to interpret a laboratory number independently or to reintroduce a possible allergen without medical planning. [18]
United Kingdom: symptomatic adults in specialist care
The British Society of Gastroenterology published another update in 2026. Its optional no-biopsy pathway concerns symptomatic adults assessed in secondary care with IgA-tTG at least ten times the laboratory’s upper limit, following shared decision-making. This is not a blanket rule for screening an otherwise well person in primary care. Endoscopy remains important when there are warning symptoms or a possible alternative diagnosis, and the guideline urges caution around newly diagnosed autoimmune conditions that can affect antibody results. Because this pathway differs from both US and European recommendations, ask which guideline your service uses and why its approach fits your circumstances. [19]
Children: a separate specialist pathway
Children have a separate pathway. The 2020 ESPGHAN guideline allows selected children to receive a specialist diagnosis without biopsy when tTG-IgA is at least ten times the upper limit of normal and endomysial IgA is positive in a second blood sample, with family agreement. Symptoms and HLA genetic testing are not mandatory criteria for that route. Lower antibody levels and IgA deficiency require different evaluation rather than stretching the high-IgA criteria to fit. Local paediatric practice may vary. An adult rule found online should never be used to decide a child’s testing, and the clinician must check the actual assay and complete results. [20]
Why strict criteria matter
The strict laboratory requirements have a purpose. The international ProCeDE study tested a carefully defined paediatric approach across multiple centres and found very high accuracy in the selected high-antibody group. Its results helped build confidence in avoiding biopsies for appropriately assessed children. They do not mean that a mildly positive result, one home test or symptoms alone carry the same certainty. The study also highlights why the whole diagnostic pathway matters: the population being tested, antibody measurement, confirmation and specialist review work together. If results disagree, resolving that disagreement is more useful than choosing whichever result matches an expectation. [21]
If results are unclear or gluten is already restricted
Genetic testing answers another question. HLA-DQ2 and HLA-DQ8 are susceptibility markers, not proof of active coeliac disease. Many people who carry them never develop the condition. Their absence can be useful when a specialist is trying to make coeliac disease unlikely, particularly if earlier testing was inconclusive. A clinical study of HLA testing also identified rare exceptions involving how relevant genetic combinations were reported, which reinforces the need for professional interpretation. A consumer genetic result cannot replace coeliac blood testing or an appropriate diagnostic assessment. Discuss what uncertainty the test is intended to resolve before treating its result as a diagnosis. [22]
Already avoiding gluten can make the next step more complicated, but there is no reliable shortcut based on how quickly symptoms return. In a controlled study of adults with previously confirmed coeliac disease, symptoms, intestinal changes and antibody responses developed on different timescales. A symptom-free few days therefore cannot be used as a personal exclusion test, and a painful reaction does not by itself prove coeliac disease. If a specialist proposes a gluten challenge, the purpose is to obtain interpretable medical evidence within an individual plan. Its suitability, monitoring and testing schedule need discussion, especially when allergy is also possible. [23]
Research in people who had started a gluten-free diet without a confirmed diagnosis illustrates the uncertainty. In one referral-centre series, 30 of 206 adults assessed with a clinical gluten challenge and subsequent biopsy had findings meeting the study’s coeliac definition. Digestive complaints were common in both those with and without that outcome. The percentage is not your personal probability: these were selected patients referred to a specialist centre. The useful lesson is that symptoms and a self-selected diet do not settle the diagnosis. Previous records, antibody results and the reason gluten was stopped can change the next clinical decision. [24]
When tests point toward non-coeliac sensitivity
Non-coeliac gluten or wheat sensitivity becomes a consideration after appropriate assessment has excluded coeliac disease and wheat allergy. Reported symptoms include abdominal pain, bloating, altered bowel habits, fatigue and difficulty concentrating, but none is specific. There is no single validated blood test that confirms this diagnosis. The Salerno expert framework describes structured symptom assessment and, where appropriate, clinician-directed dietary evaluation with controlled re-exposure. That framework is not a home challenge instruction. It also acknowledges uncertainty about which wheat components cause symptoms. A careful diagnosis protects against both dismissing ongoing discomfort and assigning a lifelong disease label without adequate evidence. [25]
Wheat contains more than gluten. Fructans are fermentable carbohydrates that can contribute to symptoms in some people. In a blinded crossover trial of 59 people reporting gluten sensitivity after coeliac disease had been excluded, fructans produced greater digestive symptom scores than gluten, and gluten did not differ from placebo overall. Individual experiences varied. The result helps explain why improvement after avoiding wheat does not identify gluten as the responsible component. It does not prove that everyone has fructan intolerance or that all gluten-related symptoms share one cause. A clinician can consider this evidence alongside your overall symptom pattern. [26]
Overlap with irritable bowel syndrome adds another layer. A small controlled trial in adults reporting both IBS and gluten sensitivity found that symptoms improved during reduced intake of fermentable carbohydrates, then worsened similarly with different test foods; a reproducible gluten-specific effect was not established. Because the study was small and tightly controlled, it cannot resolve every person’s symptoms. It does show how changing several parts of a diet can obscure what actually helped. Interpreting improvement requires attention to the whole change, not just the word gluten. IBS assessment and coeliac or allergy investigations may therefore answer different, complementary questions. [27]
Expectations can influence digestive symptoms too. A 2024 blinded trial found the greatest symptoms when participants both expected gluten and received it; the investigators could not exclude an additional effect of gluten itself. The experiment was short and involved a selected group, so it cannot justify telling someone that their discomfort is imaginary. Gut symptoms are real even when their trigger remains uncertain. The practical implication is that a carefully designed evaluation can separate possibilities better than repeated anxious experiments with food. Discussing uncertainty respectfully allows the investigation to continue without prematurely declaring either an allergy or an imagined problem. [28]
What a confirmed diagnosis changes
Finally, the diagnosis affects what follow-up should mean. Childhood wheat allergy can resolve, but it does not do so on a predictable birthday. In a referral-clinic study following 103 children, many eventually tolerated wheat while a substantial minority remained allergic into adolescence. Clinicians used food-challenge outcomes to establish resolution rather than assuming that time or a falling test number made eating wheat safe. If a child has an established allergy, periodic reassessment can help avoid unnecessary long-term restriction while protecting against an unsafe return to the food. Any change to avoidance should follow the child’s allergy team’s plan. [29]
Practical support for appointments and everyday life
Keep a useful symptom record
A brief, factual diary can make an appointment more productive. Record what you ate, approximate amounts, ingredients, when symptoms began, and how long they lasted. Describe what happened rather than writing only “gluten reaction”: for example, whether there was itching, abdominal discomfort, or a visible rash. Save packaging and, when practical, photographs of visible symptoms. Note medicines already taken, illness, exercise, and any urgent care received. Allergy UK provides this general food-allergy preparation advice; a diary does not establish that gluten caused the problem. Share the record with your clinician rather than using it to design food challenges or eliminate several foods independently. [30]
Leave with a clear follow-up plan
At the appointment, ask which condition is being investigated and what each proposed test can establish. Discuss dietary changes before starting a gluten-free trial: reducing gluten can affect coeliac testing. If you have already changed your diet, describe exactly what changed and let the clinician plan the next steps. Where allergy is possible, seek individual advice rather than restarting a suspected food yourself. Keep copies of results and referrals together. After a coeliac diagnosis, ask about dietitian support and follow-up appointments. NHS information describes reviews of symptoms, growth or weight, diet, and additional nutritional needs; your clinician should explain your individual plan. [31]
Make nutrition advice fit your household
After a coeliac diagnosis, a dietitian can turn the medical plan into familiar meals. Children’s Hospital of Philadelphia describes individual assessment of nutritional, growth, vitamin, and mineral needs, with attention to cultural preferences. Describe familiar breakfasts, packed lunches, snacks, and evening meals, including culturally important foods. Ask how the recommended diet can remain varied and nutritionally complete, and which concerns need assessment rather than supplements chosen independently. Mention limited cooking facilities, sensory preferences, other dietary restrictions, or difficulty reading packaging. Useful questions include: “Which replacements have similar nutritional value?” and “What would a realistic school or work lunch look like?” Request explanations in a format you can use again at home. [32]
Understand US FDA label distinctions
For packaged foods covered by US FDA allergen rules, wheat is a major allergen that must be identified when present as an allergenic ingredient. Barley and rye are not covered by that wheat declaration, so the absence of “wheat” is not a gluten-free assurance. Separately, an FDA-regulated gluten-free claim requires less than 20 parts per million of gluten and other ingredient conditions. A qualifying product may contain wheat-derived ingredients processed to remove gluten; gluten-free therefore does not mean wheat-free or establish suitability for wheat allergy. Read the full ingredient information, not just a separate “Contains” line. Ask your clinician or dietitian how these distinctions apply to your confirmed diagnosis. [33]
Check prepared meat products carefully
In the US, USDA’s Food Safety and Inspection Service regulates meat, poultry, and processed egg products under a separate labelling framework. Its guidance explains that ingredients containing major allergens must appear by their common or usual names in the ingredient statement; a separate “Contains” statement is voluntary for these products. Consequently, a quick search for that statement can miss information. Prepared items such as chicken nuggets, sausages, or meat dishes may include coatings, fillers, or sauces that need checking. Review the package each time, including familiar purchases, because formulations can change. If an ingredient’s source is unclear, obtain reliable clarification from the manufacturer rather than guessing from the product name. [34]
Read labels in their local context
The Food Standards Agency’s cited guidance applies to England, Wales, and Northern Ireland. It requires relevant cereals to be identified specifically, such as wheat, barley, rye, or oats, and emphasised in ingredient lists. Under this framework, “gluten-free” means no more than 20 milligrams of gluten per kilogram of food. The cereal declaration can still be necessary on a gluten-free product, and a gluten-free claim does not automatically resolve cereal-allergy concerns. When abroad, check the rules relevant to where the food is sold. For unpackaged meals, ask staff where allergen information is available and discuss preparation and ingredients. Packaging conventions should never substitute for a diagnosis-specific plan. [35]
Agree on shared-kitchen routines
For households managing diagnosed coeliac disease, the National Celiac Association describes both dedicated and shared kitchens, with attention to preventing gluten cross-contact. Use that patient-education principle to discuss practical routines with your dietitian and everyone preparing meals. Walk through food storage, preparation surfaces, cooking utensils, and serving arrangements. Pay particular attention to crumbs in shared spreads and equipment that is difficult to clean. Decide which items need separate use and how they will be clearly identified. A short agreed routine helps visitors and occasional carers follow the same approach. Review the setup when someone moves in or a child starts preparing food independently; the arrangement should be understandable to everyone. [36]
Ask restaurants concrete preparation questions
FARE’s general food-allergy guidance recommends contacting restaurants beforehand and discussing both ingredients and cross-contact. For confirmed wheat allergy, communicate that precise diagnosis and the foods your clinical plan identifies. Ask who can check the recipe, whether coatings or sauces contain wheat, and whether shared cooking equipment introduces exposure. A written chef card can support the conversation, but staff need to understand it. At catered events, establish who will identify and serve the appropriate meal. If staff cannot give a dependable answer, choose another suitable option or venue. For anyone prescribed emergency medication, include access to it in the outing plan; a reassuring menu cannot guarantee an uneventful meal. [37]
Discuss cost and food access openly
When a gluten-free diet has been medically recommended, affordability belongs in the care conversation. Coeliac UK’s patient resources address balanced meal planning on a budget and the extra cost of replacement foods. Make a realistic shopping plan around the foods your dietitian has identified as suitable, checking what is available. Compare the cost of a complete meal, storage life, and likely waste rather than the price of one specialist product. Tell the care team if transport, limited shops, cooking equipment, or an unpredictable income makes the plan difficult. Ask about local support without assuming eligibility or availability. A workable plan needs enough suitable food all week, including busy days. [38]
Coordinate support across the school day
For a child with diagnosed food allergy, CDC school guidance emphasises daily management, emergency preparation, staff education, and a supportive environment. Discuss a clinician-informed plan with the school health contact. Include meals, classroom activities involving food, after-school care, transport, and trips, rather than considering lunch alone. Establish who communicates relevant changes and how substitute staff receive essential instructions. Ask how a child can request help discreetly and participate in celebrations without pressure to eat an uncertain food. Keep communication respectful and share only information needed for care. CDC’s framework concerns food allergy; a student with coeliac disease needs a plan reflecting that different diagnosis. Specific arrangements depend on the child’s needs and local processes. [39]
Make workplace arrangements specific
Anaphylaxis UK’s general workplace guidance encourages individual planning for allergies, including food storage, catering, cleaning, and emergency readiness. If wheat allergy has been diagnosed, identify potential problems: shared snacks, catered meetings, staff kitchens, or meals away from the workplace. Discuss what information organisers need before booking food and whom to contact when arrangements change. With your agreement, close colleagues can learn the relevant response plan and where prescribed emergency medication is kept. You can also state how much health information you want shared more widely. Address teasing or food-related “pranks” promptly through appropriate workplace channels. These are planning suggestions, not a promise that a particular accommodation or legal protection applies everywhere. [40]
Prepare for travel disruptions
ASCIA’s travel checklist is written for people at risk of anaphylaxis, including those with food allergies; it is not a coeliac-disease treatment plan. Before a trip, ask your clinician whether your existing action plan and travel documentation need updating. Check transport providers’ allergy policies, suitable food availability, and arrangements for delays. Discuss prescribed medication supplies with the prescriber and keep essential emergency items accessible during travel. Identify emergency contacts and healthcare facilities locally. Translation cards can help communicate the specific allergy and preparation needs when languages differ. Check insurance and customs requirements for your itinerary directly. A requested special meal or seating arrangement should not be treated as a guarantee against exposure. [41]
Support the person as well as the diet
Beyond Celiac’s patient education recognises that managing coeliac disease can involve anxiety, frustration, and social isolation, and describes support groups and counselling as sources of help. Families can respond by asking which part of daily life feels hardest and sharing work such as planning meals or checking arrangements. Include the person in decisions about celebrations and visits instead of making every conversation about food. Take persistent distress or avoidance of social life seriously and discuss professional support when needed. Emotional difficulties should not automatically be attributed to gluten exposure. Peer communities may offer companionship and useful questions for appointments; individual medical decisions still belong with the healthcare team. [42]
Frequently asked questions
Is gluten allergy a precise diagnosis?
No. Wheat allergy, coeliac disease and non-coeliac sensitivity differ. [2]
Can coeliac disease occur without diarrhoea?
Yes. Some people have few or no noticeable symptoms. [3]
Does a positive wheat-IgE test prove allergy?
Not necessarily. Sensitisation needs interpretation alongside the reaction history. [13]
Can children be diagnosed with coeliac disease without biopsy?
Sometimes. Specialists must first confirm that strict diagnostic criteria are met. [20]
Is gluten-free always suitable for wheat allergy?
No. Some gluten-free foods contain wheat-derived ingredients. [33]
Can I test a suspected allergy at home?
No. Discuss food reintroduction or challenges with your allergy team. [4]
Sources
- NHS: anaphylaxis warning signs
- NASPGHAN: gluten-related conditions
- NIDDK: coeliac symptoms; NIDDK: coeliac diagnosis
- PRACTALL: supervised food challenges, 2024
- WAO: anaphylaxis guidance
- ACAAI: wheat-allergy symptoms
- Kennard: omega-5-gliadin allergy cohort
- NICE: coeliac recognition and assessment
- TEDDY: childhood symptoms and growth
- Silvester: measured gluten exposure
- International urticaria guideline, 2026
- EADV: dermatitis herpetiformis guidance
- EAACI: food-allergy diagnosis
- Venter: grass and wheat cross-sensitisation
- AAAAI: commercial IgG food panels
- AGA: coeliac blood-test interpretation
- ACG: US coeliac guideline, 2023
- ESsCD: European adult guideline, 2025
- BSG: British adult guideline, 2026
- ESPGHAN: childhood diagnostic guideline, 2020
- ProCeDE: childhood diagnostic validation
- Pallav: clinical HLA testing
- Leffler: differing challenge-response timescales
- Ventoso: diagnostic challenge outcomes
- Salerno: non-coeliac sensitivity framework
- Skodje: blinded fructan comparison
- Biesiekierski: controlled dietary trial
- de Graaf: expectancy and symptoms
- Keet: childhood wheat-allergy follow-up
- Allergy UK diary; appointment preparation
- NHS diagnosis; ongoing care
- CHOP nutrition services
- FDA allergen labels; gluten-free rule
- USDA-FSIS allergen guidance
- FSA technical guidance
- NCA kitchen guide
- FARE dining guidance
- Coeliac UK budget planning
- CDC school guidance
- Anaphylaxis UK workplace guidance
- ASCIA travel checklist
- Beyond Celiac emotional support





