

Zika virus: the essentials
Zika virus is usually spread through an infected mosquito’s bite. It can also pass through sex and from a pregnant person to their developing baby. Many infections cause no symptoms; when illness occurs, it is often mild. Pregnancy deserves special attention because infection can affect a baby’s development even when the pregnant person feels well. As of October 12, 2026, CDC guidance states that no vaccine or preventive medicine is available for Zika. The most useful protections are avoiding mosquito bites, reducing sexual transmission when exposure is possible, and discussing travel and pregnancy plans with a healthcare professional. A trip, a mosquito bite, or a rash alone does not establish that someone has Zika. [1]
If you have recently visited a place with Zika risk and develop symptoms, seek medical advice promptly, including while you are still traveling. Contact your pregnancy care team if you or your partner is pregnant after possible exposure, even without symptoms. Give the actual travel dates and destination rather than simply saying you went abroad. NHS advice also recommends getting advice if you or your partner becomes pregnant within three months after returning from a risk area. That is a reason to discuss the situation, not proof that infection or fetal harm occurred. If you are planning travel, an appointment four to six weeks ahead is useful, but late advice can still help. [2]
When to get urgent help
Do not assume that a fever after travel is harmless Zika. Dengue can look similar and can become dangerous quickly. Seek immediate medical care for belly pain or tenderness, repeated vomiting, bleeding from the nose or gums, blood in vomit or stool, or extreme tiredness or restlessness. These warning signs can appear as a fever improves, often within the following day or two. A falling temperature therefore does not always mean the danger has passed. You do not need to wait for a Zika or dengue test result before seeking care. Tell the clinician where you traveled and when the fever began, and mention any bleeding or difficulty keeping fluids down. [3]
New or worsening weakness, difficulty walking, or tingling that spreads deserves urgent assessment. Guillain–Barré syndrome is a rare nerve disorder that can follow infections and may affect movement, swallowing, or breathing. Call your local emergency number for difficulty breathing, trouble swallowing or speaking, sudden facial drooping, or inability to lift an arm. Some of these symptoms can signal a stroke or another emergency rather than Zika. Do not try to identify the cause at home or drive yourself when seriously unwell. Medical assessment is important even if an earlier fever or rash has already settled; the timing of a new nerve symptom does not make it safe to ignore. [4]
What Zika symptoms can feel like
When Zika causes symptoms, the common pattern includes a rash, fever, headache, sore joints, muscle aches, and red eyes. People may have only some of these features. Illness usually lasts several days to about a week, and hospitalization is uncommon. Those general patterns are reassuring, but they cannot identify the virus: dengue and chikungunya can produce overlapping symptoms. A photograph of a rash is especially limited because many infections and noninfectious conditions can look alike. A clinician considers the whole picture, including travel and exposure. Seek another assessment if your condition worsens rather than relying on the expectation that Zika is usually mild. Rare complications can involve the nervous system or abnormal bleeding. [5]
Symptoms, when they appear, commonly begin about three to fourteen days after infection. This incubation period is different from the duration of symptoms and from the sexual-transmission precaution period. It helps explain why someone may feel fine throughout a trip and become unwell after returning. CDC estimates that most infected people have no symptoms. Feeling well therefore cannot answer every question about a possible exposure, especially during pregnancy. In babies and young children, joint pain can be difficult to recognize and may appear as irritability or reluctance to move a limb. A child who seems unwell should be assessed on their own symptoms and age, rather than being assumed to have the same illness as a traveling adult. [6]
How infection passes between people and mosquitoes
The main mosquito carriers are Aedes species. A mosquito can acquire Zika after biting someone whose blood contains the virus and later transmit it through another bite. These mosquitoes can bite indoors or outdoors and during the day or night, so protection only at bedtime leaves gaps. Sex and infection during pregnancy provide additional routes; mosquito exposure is not required for every infection. Less common routes involve infected blood or tissues and laboratory exposures. This is why a clinician may ask about both travel and sexual contact. Answering those questions helps them assess exposure; the questions are not a judgment about relationships or behavior. [7]
Sexual transmission can occur within a committed relationship and can involve someone who never realized they were infected. Condoms lower the chance of transmission when used correctly throughout vaginal, anal, and oral sex; dental dams may be used for certain types of oral sex. Avoid sharing sex toys, or discuss appropriate barriers and cleaning with a sexual-health professional. Not having sex prevents sexual transmission during the precaution period. These options can be discussed without blame: the aim is a practical plan that both partners understand. A conversation about precautions is particularly useful before a trip, when there is time to obtain supplies and agree on what will happen after returning. Symptoms are not a reliable substitute for that plan. [9]
How long do sexual precautions last?
CDC’s sexual-transmission guidance, reviewed September 14, 2026, gives the minimum timeframes below for using condoms or not having sex after possible Zika exposure. The difference reflects the virus lasting longer in semen than in other body fluids. The clock begins on return from travel, even without symptoms, or from symptom onset or the diagnosis date. If those dates differ, or exposure continues, ask a clinician to identify the appropriate start and end dates. Testing blood, urine, or genital secretions is not recommended to decide whether someone can still pass Zika through sex. A negative result can be falsely reassuring and should not be used to shorten precautions. [8]
| Exposed person in CDC guidance | Minimum period |
|---|---|
| Male: | use condoms or do not have sex for at least three months. [8] |
| Female: | use condoms or do not have sex for at least two months. [8] |
Pregnancy changes the discussion. Infection during pregnancy can also cause pregnancy loss, stillbirth, or premature birth. WHO advises safer sex, including correct and consistent condom use, or abstinence throughout pregnancy when a partner lives in or returns from an area with local Zika transmission. This is a pregnancy-long precaution rather than simply counting down the shorter intervals above. People who might become pregnant should have access to contraceptive counseling and a choice of methods. If unprotected sex has occurred and pregnancy is not desired, seek prompt advice about emergency contraception and local services. Exposure does not oblige anyone to make a particular reproductive decision. Counseling should explain the uncertainties and options, support informed choices, and include the partner when the patient wants that support. [10]
Zika during pregnancy: risk without assumptions
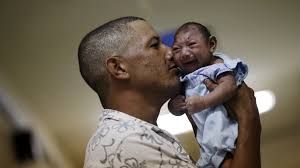
Congenital Zika syndrome describes a pattern of conditions that can follow infection before birth. These can include problems with brain development, a smaller-than-expected head, eye or hearing problems, seizures, feeding difficulties, stiff muscles, and limited joint movement. Not every affected child has every feature, and not every pregnancy with Zika infection results in these problems. CDC reports Zika-associated birth defects in about five percent of babies in a U.S. registry group whose mothers had confirmed or possible infection during pregnancy. That is a finding from a defined population, not a personal forecast. Risk depends on factors including when infection occurred, and complications can follow infection with or without maternal symptoms. Some problems become apparent only as a child grows, so follow-up can matter even when a newborn looks well. [11]
If infection is confirmed or possible during pregnancy, the care team may arrange detailed ultrasound examinations to assess anatomy and growth. CDC says serial scans every three to four weeks should be considered, with the schedule individualized. A normal scan cannot answer every question about infection or later development, and abnormalities may not appear immediately. An amniocentesis may sometimes be discussed, but its role in diagnosing congenital Zika remains uncertain; it is not an automatic requirement after travel. The procedure’s benefits and risks need a personal discussion. A negative Zika result from amniotic fluid does not completely exclude fetal infection, and a positive result does not reliably predict how severely a baby will be affected. A maternal–fetal medicine specialist can help explain these limits. [12]
Planning a pregnancy can involve competing priorities such as age, fertility treatment, family responsibilities, and the details of a possible exposure. CDC supports shared decision-making with a healthcare professional about waiting before conception. Bring both partners’ travel histories, because the relevant exposure may have occurred in the partner who did not become pregnant. Discuss how current destination guidance applies to your circumstances and whether a fertility service needs to coordinate the plan. Do not turn a negative test or the absence of symptoms into a guarantee of safety. The goal is an agreed plan with understandable dates, reasons, and remaining uncertainty, rather than a decision based on an old article, an online anecdote, or a guessed mosquito bite. [32]
Who needs testing, and what can it tell you?
Zika testing is targeted rather than a routine test for every traveler. A clinician first asks about symptoms, pregnancy, destination, travel dates, and possible sexual exposure. Testing is particularly relevant when symptoms follow travel to a risk area, or when a pregnant person has symptoms after an affected partner’s travel. Certain ultrasound findings or a baby’s findings can also prompt an assessment in the context of exposure. Contact a clinician while symptoms are present rather than waiting for them to disappear. Testing to establish that it is safe to become pregnant is not recommended. Ask what question a proposed test can answer, how the result will change care, and what follow-up would be needed for a positive, negative, or uncertain result. [13]
Current CDC guidance does not recommend routine testing for asymptomatic nonpregnant people. For asymptomatic pregnant travelers, the approach depends on the destination and discussion with the care team: molecular testing may be considered after travel to an area with an active Zika notice. Routine testing after travel to an area with current or past transmission is not recommended, but testing can be considered individually. When chosen, a nucleic acid amplification test, or NAAT, can be performed up to twelve weeks after travel. Symptomatic pregnancy requires prompt assessment; testing pathways differ by mosquito or sexual exposure and destination category. For symptomatic nonpregnant patients with relevant travel outside the United States and its territories, CDC generally uses molecular testing during the first seven days and antibody testing in appropriate later or negative-test situations. These are clinician pathways, not reasons to delay seeking care. Local health departments can help arrange suitable tests. [14]
Molecular tests look for genetic material from the virus. Antibody tests look for the immune response. Neither provides a perfect record of an exposure. Viral material may no longer be detectable when a sample is collected, so a negative molecular test does not always exclude recent infection. Antibodies can remain detectable long after the illness, making the date of infection difficult to establish. They can also cross-react with related viruses, particularly dengue. Previous infections or vaccination against some related viruses may complicate interpretation. A confirmatory neutralization test can help in selected cases but may not fully distinguish the viruses. An uncertain result is therefore not automatically a confirmed infection or a laboratory mistake. A clinician combines test results with the timing, symptoms, and local epidemiology, and explains what remains unknown. [15]
Treatment and safer symptom care
There is no medicine that specifically clears Zika. Supportive care usually means rest, fluids, and symptom relief chosen with a clinician or pharmacist. Acetaminophen, also called paracetamol, may be used for fever or pain when appropriate. Avoid aspirin and other nonsteroidal anti-inflammatory medicines, including ibuprofen and naproxen, until dengue has been ruled out, because they can increase bleeding risk in dengue. Tell the clinician about medicines you already take, including any prescribed aspirin or blood thinner, and ask how to manage them rather than independently changing an ongoing prescription. Symptoms that worsen or prevent normal drinking need reassessment. Treating discomfort does not remove the need to consider other causes of a travel-related fever. [16]
Read the active ingredients on every medicine package. Acetaminophen appears in many cold, flu, and prescription products, so combining them can accidentally produce an overdose. Use only the amount and interval recommended for the particular product and patient; this guide does not provide a personal dose. Ask before use if you have liver disease, and discuss all medicines during pregnancy. Children need the correct formulation and measuring device, not an adult product or a kitchen spoon. If too much may have been taken, get urgent medical or poison-service advice immediately rather than waiting for symptoms. More medicine is not a faster way to recover, and taking products with different brand names does not guarantee that their ingredients are different. [17]
Pay attention to hydration, especially when fever, heat, vomiting, or poor appetite reduces fluid intake. Small, frequent sips may be easier to tolerate when you feel sick. A pharmacist can advise about an oral rehydration solution if vomiting or diarrhea is causing substantial fluid loss. Less urine than usual, dark urine, ongoing dizziness on standing, or unusual drowsiness can signal dehydration and need prompt advice. Babies, young children, and older adults are more vulnerable; fewer wet diapers can be an important warning in a baby. Confusion, difficulty breathing, cold or blotchy skin, or being hard to wake are emergency signs. Someone who cannot drink enough or is becoming less alert should not simply be encouraged to sleep it off. [18]
Care for a suspected case also protects other people. During the early days of illness, preventing mosquito bites reduces the chance that local mosquitoes will pick up the virus and spread it. Continue precautions even when you are resting indoors. Clinicians may evaluate for dengue or chikungunya alongside Zika because the diseases overlap geographically and clinically. If pregnancy is involved, the plan may include obstetric monitoring and a coordinated newborn assessment. Supportive care is active care: it includes checking that the diagnosis still makes sense, watching for deterioration, and deciding whether additional assessment is needed. There is no approved Zika antiviral or preventive drug to substitute for these measures. [19]
Travel risk: check the destination and the date
A place’s Zika classification is not a precise prediction of what will happen on a particular trip. Surveillance and testing vary between countries, and outbreaks can be detected late. CDC therefore treats countries with current or past local transmission as having potential risk, even when the present level is uncertain. A place with mosquitoes capable of spreading Zika but no reported cases is a different category, but absence of reported cases is not proof that infection is impossible. Check the current country information and any active travel notice before booking and again before departure. A list copied from an older article can miss changes. Avoid relying on broad labels such as an entire continent being safe or unsafe. [20]
CDC advises pregnant travelers to avoid destinations with an active Zika Travel Health Notice. If travel is unavoidable, strict mosquito and sexual-transmission precautions are important. For destinations with current or past transmission but no active notice, CDC recommends discussing the trip, reasons for travel, mosquito protection, and possible risks with a healthcare professional. People planning pregnancy and their partners should also discuss whether to delay conception. After travel to an active-notice area, CDC advises delaying pregnancy using the sexual-transmission timeframes; for current-or-past-transmission areas, the decision is individualized. Living in an area with ongoing exposure is different from returning from a short trip: there may not be a simple final exposure date. Local counseling should account for that continuing risk and the person’s priorities. [21]
Date-sensitive example: on October 12, 2026, CDC’s active notice for Zika in Indonesia, last reviewed August 7, 2026, reported infections among travelers returning from Bali. The notice advised pregnant people to avoid travel to Bali and all travelers to prevent mosquito bites and sexual transmission during and after travel. People planning pregnancy were advised to delay pregnancy after travel using the recommended intervals. This example is included because current notices matter; it is not a permanent destination list. Recheck the linked notice and destination guidance before making a new decision. Symptoms during or after travel should prompt immediate medical advice because an apparently mild Zika-like illness may instead be another, more serious infection. [22]
Use the pretravel conversation to make a workable plan. Explain whether the trip is optional, how long you will stay, where you will sleep, and how consistently you can prevent bites. Include a partner’s travel even if you are staying home. Ask how pregnancy plans affect the recommendation and what protection should continue afterward. If you live abroad, discuss risk in the context of the local situation rather than treating every day as a separate travel event. Good counseling acknowledges that access to screened accommodation, repellent, and healthcare differs between people. It should help you weigh realistic options and understand the recommendation, rather than simply hand you a country name or an instruction without explanation. [23]
Other travel protections may be relevant, but they are disease-specific. Yellow fever vaccination protects against yellow fever; it is not a Zika vaccine. Its suitability depends on the destination and the traveler, and pregnancy is a precaution that requires an individual risk–benefit discussion. If your itinerary raises that separate issue, see our guide to yellow fever prevention and travel planning and discuss it with a travel-health professional. Keep the names of infections and vaccines distinct when checking records or asking questions. A vaccination certificate for one disease does not answer the Zika questions covered in this guide. [31]
Make mosquito prevention practical
Choose an effective skin repellent
CDC recommends an EPA-registered insect repellent. Examples of active ingredients include DEET, picaridin, IR3535, oil of lemon eucalyptus, PMD, and 2-undecanone. When used according to the label, registered products are considered safe and effective, including during pregnancy and breastfeeding. Check the exact product label rather than assuming all products with similar names are interchangeable. Apply sunscreen first and repellent second when both are needed. Wear loose-fitting long sleeves and trousers, and protect babies’ strollers or carriers with mosquito netting. CDC advises against OLE or PMD products for children under three; age directions on specific products also matter, so ask a pharmacist or pediatric clinician when choosing for a young child. Permethrin products for clothing and gear must not be applied directly to skin. Products marketed as natural still need evidence of effectiveness. [24]
Use repellent on exposed skin or clothing as directed, not underneath clothes, over wounds, or close to the eyes and mouth. For the face, spray onto your hands first rather than directly toward the face. An adult should apply a child’s repellent and keep it off the child’s hands. Reapply at the label’s interval, taking activity, sweating, and water exposure into account. More product is not automatically better. Wash treated skin when protection is no longer needed and keep containers away from children. EPA’s product-specific age labeling can differ, including for some oil-of-lemon-eucalyptus formulations; read the bottle you actually have. If you cannot tell whether the product suits a young child, seek advice instead of improvising a dilution or a homemade blend. [25]
Use clothing and your surroundings
Permethrin-treated clothing provides another layer of protection. Follow the treatment or factory-treated garment label, including washing instructions and restrictions on the items that may be treated. Protection applies to the covered area, so exposed skin may still need a repellent labeled for skin. EPA’s assessment of factory-treated clothing includes use by pregnant and nursing people. Keep the roles of different products clear: a pesticide intended for gear or clothing is not interchangeable with skin repellent. Plan ahead so you understand how the garment should be used and cared for before the trip begins. [26]
At home or in longer-term accommodation, check for water in buckets, plant saucers, toys, discarded containers, and similar places. Once a week, empty and scrub, turn over, cover, or discard water-holding items as appropriate. Tightly cover stored water and inspect indoor containers as well as the yard. Repair window and door screens, keep doors closed, and use air conditioning when available. These measures work best as a routine shared by the household and neighborhood. If additional insecticides are needed, use only suitable products according to their labels or seek professional help. Spraying alone will not keep a home mosquito-free while breeding sites and entry points remain. Do not put pesticides into drinking water or use an outdoor product inside unless its label allows that use. [27]
Pack protection where you can reach it on arrival, not only in a suitcase that may be delayed. Choose accommodation with effective screens or air conditioning when possible; a suitable mosquito net is useful when screened sleeping spaces are unavailable. Include enough repellent and covering clothes for the planned activities. CDC advises preventing mosquito bites for three weeks after returning from a risk-area trip, even when you feel well, to reduce onward spread to mosquitoes. That mosquito precaution period is separate from the longer sexual-transmission intervals. If fever, rash, headache, or muscle and joint pain develops after travel, tell a healthcare professional promptly and give the itinerary. The end of a holiday is not necessarily the end of the prevention plan. [28]
After birth: follow-up and family support
Tell the baby’s clinician about possible Zika exposure during pregnancy and share any maternal test or ultrasound reports. Assessment is guided by the baby’s findings and evidence of maternal infection; every travel history does not automatically lead to the same testing. When congenital infection is suspected, early infant testing and appropriate eye, hearing, neurological, and developmental assessment may be needed. Follow-up also includes routine well-child care and monitoring growth and development. Some children benefit from early-intervention services or feeding support. CDC’s infant guidance emphasizes coordination between obstetric and pediatric teams, so ask who is responsible for handing over records and arranging the next appointment. Do not wait for a child to miss several milestones before raising a new concern with their clinician. [29]
Breastfeeding is still encouraged by CDC after maternal Zika infection or possible exposure. The virus has been detected in breast milk, but transmission through breastfeeding has not been confirmed, and the known benefits are considered to outweigh the potential risk. If feeding is difficult or you have another medical concern, discuss it with the baby’s clinician or a lactation professional rather than assuming that Zika exposure means breastfeeding must stop. [7]
Families affected by congenital conditions may need practical and emotional support as well as medical appointments. Ask the child’s care team about local services, therapy referrals, and support groups. Other families can share useful experience, while clinical decisions should remain grounded in the child’s needs and professional advice. It can help to keep one accessible list of clinicians, appointments, questions, and contact details, especially when several specialties are involved. Discuss travel, costs, childcare, language needs, or difficulty attending appointments openly so the team can help identify resources. A child’s diagnosis does not describe the whole child, and families deserve information that is clear, respectful, and free of blame. No family should be expected to navigate complicated care using internet advice alone. [30]
What to bring to your appointment
Prepare a short timeline with the places visited, departure and return dates, first symptom date, and any test dates. List medicines and supplements, and bring the original results if you have them. Write down the decision you most need help with: symptom care, whether testing is appropriate, a pregnancy plan, or precautions with a partner. Useful questions include: What other diagnoses are being considered? What could this test miss? Which precautions apply to us, and what are the start and end dates? Who will contact me with results? When should I seek urgent care rather than wait? Before leaving, ask for the plan in writing if it is difficult to remember. Clear next steps are more useful than trying to interpret a result or calculate a timeline alone.





